Related Experiment Video
Updated: Sep 14, 2026

Hyperglycemic Clamp and Hypoglycemic Clamp in Conscious Mice
Published on: January 26, 2024
Hepatic clamping and postoperative hyperglycaemia: A retrospective cohort study in liver surgery
Gabriel Thierry1, Florian Beck1, Olivier Jacquemin1
1From the Department of Anesthesia and Intensive Care Medicine, Liège University Hospital, Liège, Belgium (GT, FB, OJ, PYH, AK, VB), Groupe francophone de Réhabilitation Améliorée après Chirurgie (GRACE; Francophone Group for Enhanced Recovery after Surgery), Beaumont, France (GT, PYH), Anesthesia and Perioperative Neuroscience Laboratory, GIGA-Consciousness, GIGA-Neuroscience (FB, VB), Department of Abdominal Surgery and Transplantation, Liège University Hospital, Liège, Belgium (MV, OD).

Background:
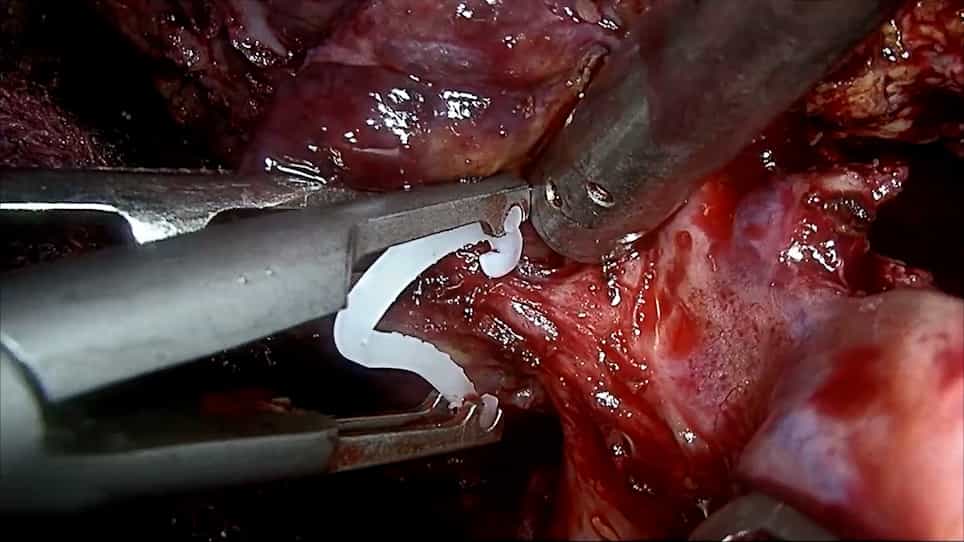
The Pringle manoeuvre, which involves intermittent clamping of the hepatic pedicle, is a common surgical strategy employed to reduce blood loss during liver resection. Although its impact on intra-operative glucose levels has been documented, its contribution to postoperative hyperglycaemia remained an untested hypothesis.
Objectives:
The primary aim of this study was to determine whether hepatic vascular clamping was associated with increased postoperative hyperglycaemia within 24 h after liver surgery. Secondary aims included examining the association between postoperative hyperglycaemia and infectious complications and length of hospital stay.
Design:
A retrospective observational cohort study.
Setting:
Single tertiary university hospital. The study period extended from January 2020 to June 2022.
Patients:
The study sample comprised 163 adult patients who underwent elective liver resection. Patients were grouped according to the intra-operative use of the Pringle manoeuvre: 107 patients underwent clamping (Pringle group), while 56 patients did not undergo clamping (No-Pringle group). No patients were excluded, and data were complete for all individuals included.
Main Outcome Measures:
The primary outcome was the occurrence of postoperative hyperglycaemia, defined as blood glucose at least 10.0 mmol l-1 (180 mg dl-1) within 24 h after surgery. Secondary outcomes included postoperative infectious complications and length of hospital stay.
Results:
Postoperative hyperglycaemia occurred in 55.1% of patients in the Pringle group compared to 23.2% in the No-Pringle group (P < 0.001). Hepatic clamping was independently associated with postoperative hyperglycaemia (adjusted odds ratio 2.91, 95% confidence interval 1.06 to 8.92). As secondary findings, a higher incidence of postoperative infections was observed in the Pringle group (23.4 vs. 5.4%, P = 0.007), and the median hospital length of stay was longer (4 [2 to 8] vs. 2 [1 to 6] days, P = 0.003).
Conclusions:
The Pringle manoeuvre was associated with increased postoperative hyperglycaemia within 24 h after liver surgery. These findings underscore the necessity for proactive intra-operative and postoperative glucose control strategies as an integral component of peri-operative management in hepatic surgery.