Related Experiment Videos
Clinical Physiology of SGLT2 Inhibitors in Non-diabetic and Diabetic Individuals
1C.N.R. (National Research Council) Institute of Clinical Physiology, Pisa, Italy. giulia.ferrannini@ki.se.

Abstract:
Sodium-glucose cotransporter 2 (SGLT2) inhibitors were developed as glucose-lowering agents but have emerged as cardiorenal therapies in people with and without diabetes. Their primary pharmacological action is restricted to the proximal renal tubule, where inhibition of SGLT2 reduces glucose and sodium reabsorption and induces sustained glycosuria. This chapter examines the physiological cascade linking this renal effect to systemic metabolic, hemodynamic, and cardiorenal consequences. In both diabetic and non-diabetic individuals, SGLT2 inhibition lowers the renal threshold for glucose excretion, increases distal sodium delivery, and transiently promotes osmotic diuresis and natriuresis. Downstream SGLT1 partially compensates for reduced proximal glucose reabsorption, limiting urinary glucose losses despite SGLT2 blockade.The resulting fall in plasma glucose and insulin shifts substrate utilization from carbohydrate toward fatty acids and ketone bodies, while uricosuria lowers serum uric acid. Over longer periods, changes include modest reductions in plasma volume and blood pressure, mobilization of tissue sodium, increased hematocrit and hemoglobin, altered renal oxygenation, and an initial decline followed by slower long-term loss of glomerular filtration rate. These effects interact across renal, metabolic, and hemodynamic pathways. Glycosuria also creates a chronic negative energy balance, although compensatory hyperphagia limits the degree of weight loss. Secondary consequences include modulation of intrarenal hemodynamics, endogenous glucose production, circulating substrates, vascular function, oxygen delivery, and established cardiorenal risk factors. Evidence from physiological studies and large clinical trials supports glycosuria as the initiating event from which multiple downstream effects arise. No single mechanism fully explains the long-term cardiovascular and renal benefits of SGLT2 inhibition. Rather, repeated, substantial glycosuria appears to induce a coordinated transition to a distinct physiological state in which several individually modest renal, metabolic, and hemodynamic adaptations converge to produce cardiorenal protection. This integrated model may better explain why clinical benefits extend beyond glucose lowering and are observed across populations, including individuals without diabetes.
Related Concept Videos
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:55
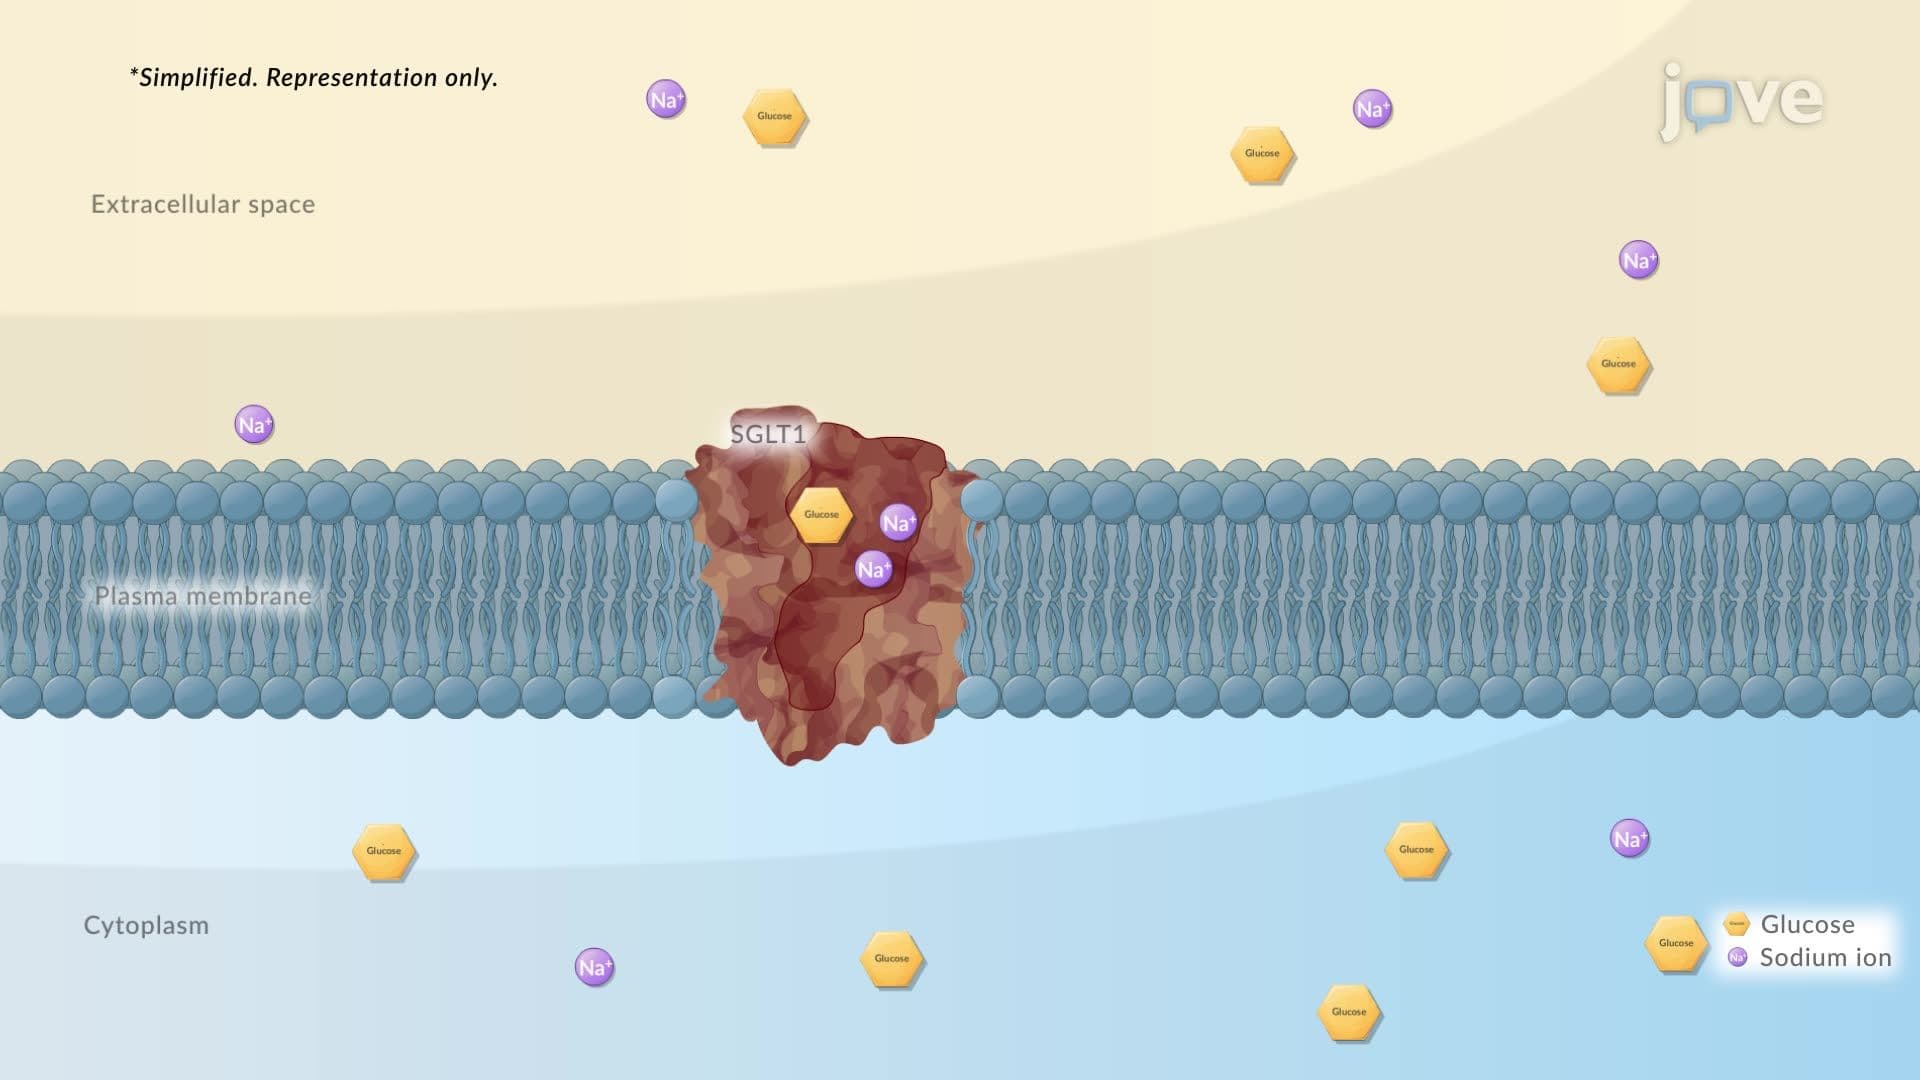
Secondary Active Transport
 01:32
Secondary Active Transport
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:26
Glucose Absorption Into the Small Intestine
 01:19
Oral Hypoglycemic Agents: α-Glucosidase Inhibitors
Acarbose and miglitol are typically...