Related Experiment Video
Updated: Sep 14, 2026


External Cephalic Version: Is it an Effective and Safe Procedure?
Published on: June 6, 2020
Effect of Intravenous Fluid Restriction on Nulliparous, Term, Singleton, Vertex Cesarean Delivery Rates
Amin Tavakoli1, Catriona Lewis1, Naomi Greene1
1Division of Maternal Fetal Medicine, Department of Obstetrics and Gynecology, Cedars-Sinai, Los Angeles, CA.

Background:
During the 2024 nationwide intravenous (IV) fluid shortage, our hospital implemented a restricted protocol for laboring patients. Previously, patients received 125 mL/hr of maintenance IV fluids; during the shortage, this was reduced to 10 mL/hr to keep the line open while encouraging oral hydration.
Objective:
Given limited and mixed data on IV fluid administration during labor, our objective was to evaluate whether IV fluid restriction in labor affected cesarean delivery (CD) rates and other labor or obstetric outcomes among nulliparous, term, singleton, vertex (NTSV) pregnancies.
Study Design:
This was a retrospective cohort study of all NTSV patients at a large quaternary care academic hospital in the United States. Patients laboring during the IV fluid shortage (minimal fluid group; 10/2024-2/2025) were compared to those laboring during the same months in the two preceding years (standard fluid group; 10/2022-2/2023 and 10/2023-2/2024). Data on demographics, labor characteristics, and delivery outcomes were abstracted from medical records. Our primary outcome was NTSV CD rate, and our secondary outcomes included total IV fluid intake in labor, total labor time, indications for cesarean delivery, and terbutaline administration. T-test, chi-square, multivariable regression, and Wilcoxon rank-sum were used as appropriate.
Results:
Of 2,506 NTSV patients, 832 were in the minimal IV fluid group and 1,674 were in the standard IV fluid group. The minimal IV fluid group had higher birth weights and was more likely to have public insurance. The minimal IV fluid group received less total IV fluids during labor (median [IQR] 873 mL [1124] vs. 2365 mL [1997], P< 0.01). There was no statistically significant difference in NTSV CD rates (28.4% vs 30.7%, P=0.23), indication for cesarean delivery, or in total labor time (median [IQR] 16.7 hours [13.7] vs. 16.4 hours [14.0], P=0.23) between the groups. However, terbutaline was administered more in the minimal fluid group (12.4% vs. 8.7%, P< 0.01).
Conclusion:
Cesarean delivery rates in NTSV patients were not negatively impacted by a minimal IV fluid protocol, suggesting that minimal IV fluid may be sufficient in resource-limited settings. However, increased need for terbutaline in this group does raise concern for potentially higher rates of tachysystole.
More Related Videos
 05:21
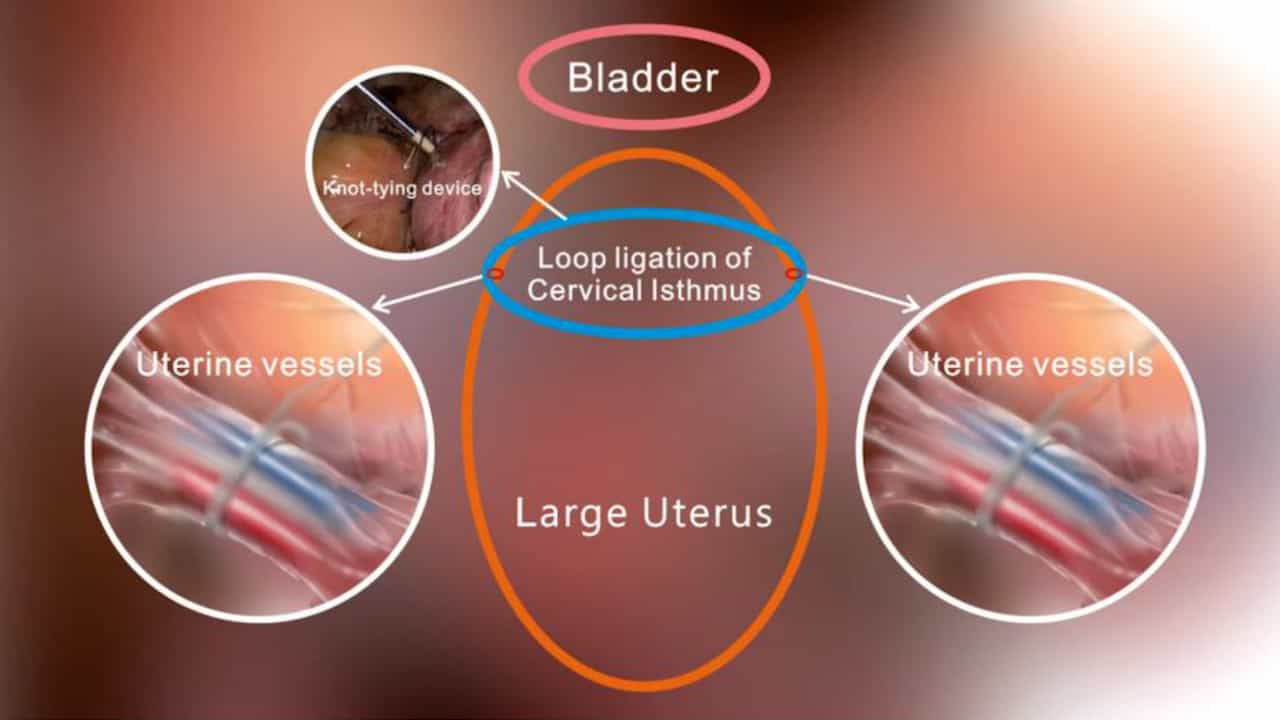
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
 05:46
Introduction of Intracapsular Rotary-cut Procedures (IRCP): A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019