Related Experiment Video
Updated: Sep 14, 2026
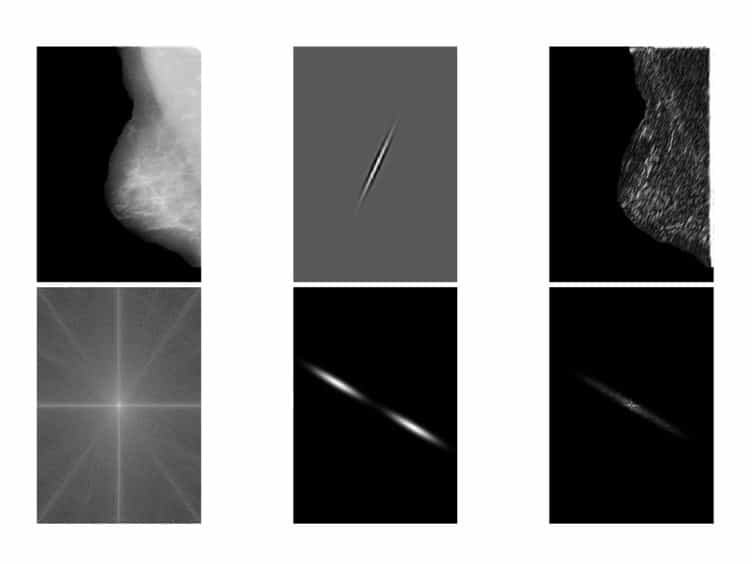

Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
Effect of Lossy JPEG Compression on AI Diagnostic Output Stability in Panoramic Radiograph Analysis
Aleš Fidler1, Veronika Krenker2, Mohmed Isaqali Karobari3
1Department of Endodontics and Operative Dentistry, Faculty of Medicine, University of Ljubljana, Ljubljana, Slovenia; Department of Restorative Dentistry and Endodontics, University Medical Centre Ljubljana, Ljubljana, Slovenia.

Objectives:
To evaluate the effect of lossy JPEG compression on the output stability of a commercial AI system applied to panoramic radiographs.
Methods:
One hundred panoramic radiographs were saved as uncompressed TIFF (reference standard) and at five JPEG compression levels (CL) - 90, 70, 50, 30, and 10 (J90-J10). All 600 images were processed by a commercial dental AI system (X-ray Insights, dentalXrai GmbH) which assigned binary labels for nine diagnostic categories across 32 tooth positions per image. Agreement between each compressed image and the system's own uncompressed output was quantified by Cohen's kappa (κ), with κ = 0.90 predefined as the agreement threshold.
Results:
Compression predominantly caused loss of findings rather than false positives, with rare hallucination of absent tooth positions. All labels showed near-perfect agreement at J90 and J70 (κ ≥ 0.920). Four prosthetic and restorative labels (implant, bridge, crown, root canal filling) were unaffected at all CLs, although implant and bridge prevalence was low (≤1.3%). Five labels fell below the agreement threshold: periapical radiolucency and filling at J30, mandibular canal at J50, and caries and present/intact at J10. Positive percent agreement for periapical radiolucency fell to 0.614 and per-tooth exact agreement to 89.1% at J10.
Conclusion:
CL ≥ 50 preserved AI output across all clinically important labels, whereas CL ≤ 30 caused meaningful degradation, particularly for periapical radiolucency and caries. A minimum CL of 50 is recommended, and the compression applied should be reported. These findings reflect output stability rather than absolute diagnostic accuracy and should not be generalized to other AI systems without validation.
Clinical Significance:
Most file-size reduction is achieved at CL 90 (≈90% reduction) with negligible loss of output agreement. Diagnostic tasks are not equally affected - low-contrast findings degrade whereas high-contrast ones remain robust. Degradation occurs predominantly through missed findings rather than false positives. A CL below 50 should therefore be avoided.

