Related Experiment Video
Updated: Sep 16, 2026
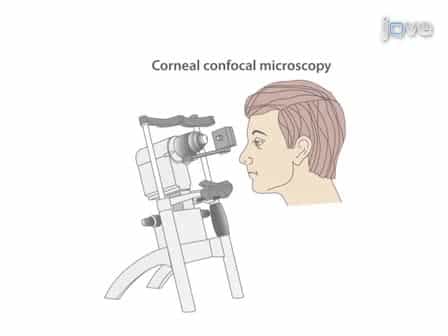

Corneal Confocal Microscopy: A Novel Non-invasive Technique to Quantify Small Fibre Pathology in Peripheral Neuropathies
Published on: January 3, 2011
Corneal Confocal Microscopy in Hereditary Demyelinating Neuropathies: Small Fiber Involvement in Charcot-Marie-Tooth
Ezgi Keskiner-Ozturk1, Semra Akkaya-Turhan2, Kayihan Uluc1
1Department of Neurology, Marmara University School of Medicine, Istanbul, Turkey.

Introduction/Aims:
Small fiber involvement in Charcot-Marie-Tooth disease (CMT) is incompletely characterized. We evaluated corneal small fiber parameters and immune cell density in common CMT subtypes, which are predominantly demyelinating neuropathies, using in vivo corneal confocal microscopy (IVCCM).
Methods:
Sixteen patients with genetically confirmed hereditary demyelinating neuropathies (PMP22-related CMT1A/HNPP and CMTX1) and 32 healthy controls underwent IVCCM. Corneal nerve fiber density (CNFD), length (CNFL), branch density (CNBD), tortuosity (CNFT), and Langerhans cell density were quantified. Clinical severity was assessed with the Charcot-Marie-Tooth Neuropathy Score (CMTNS). Neuropathic pain was defined as painDETECT ≥ 19 or ongoing treatment.
Results:
Patients showed reduced CNFD compared with controls (20.8 ± 10.7 vs. 26.1 ± 5.3 fibers/mm2; p = 0.024). Subgroup analysis demonstrated significant reductions in CNFD (p = 0.001), CNFL (p = 0.006), and CNBD (p = 0.040) in PMP22-related neuropathies, whereas CMTX1 patients did not differ from controls. CNFD, CNFL, and CNBD correlated inversely with CMTNS. Patients with neuropathic pain exhibited lower CNFD (10.5 ± 8.8 vs. 25.4 ± 7.9 fibers/mm2, p = 0.009), CNFL (9.8 ± 3.9 vs. 16.2 ± 2.8 mm/mm2, p = 0.002), and CNBD (9.9 ± 11.8 vs. 32.7 ± 19.2 branches/mm2, p = 0.030) than painless patients. Langerhans cell density did not differ between groups.
Discussion:
PMP22-related neuropathies demonstrate significant corneal small fiber loss without increased Langerhans cell density, suggesting a predominantly structural phenotype without evidence of increased corneal immune activation. IVCCM may serve as a noninvasive biomarker of small fiber involvement and disease severity.