Related Experiment Video
Updated: Sep 16, 2026
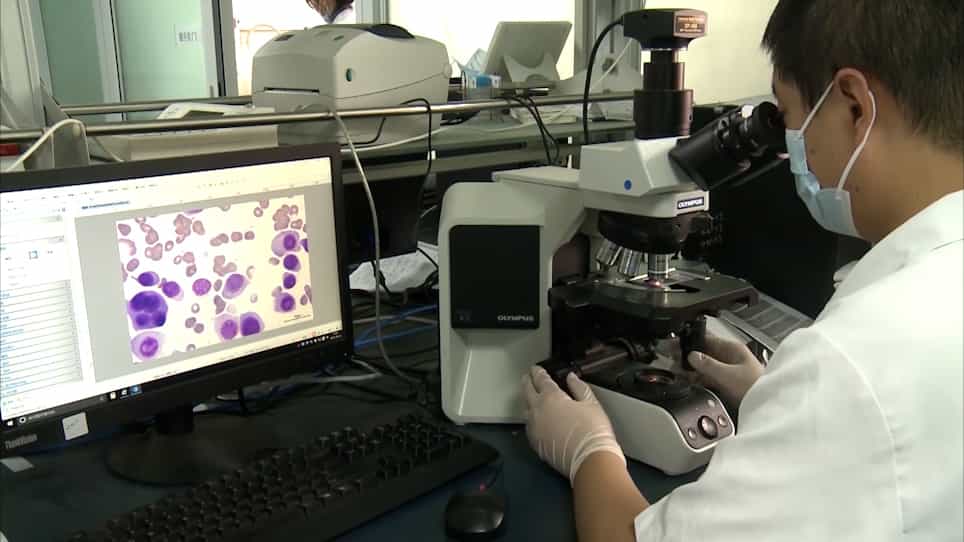

Interphase Fluorescence in situ Hybridization of Bone Marrow Smears of Multiple Myeloma
Published on: April 15, 2022
Using WB-LDCT to differentiate between benign and malignant medullary lesions in the appendicular skeleton of
Kemin Zhang1,2, Shanyan Wang3, Bing Shi4
1Department of Radiology, State Key Laboratory of Experimental Hematology, National Clinical Research Center for Blood Diseases, Haihe Laboratory of Cell Ecosystem, Institute of Hematology & Blood Diseases Hospital, Chinese Academy of Medical Sciences & Peking Union Medical College, Tianjin, China.

Abstract:
The current study aimed to differentiate between benign and malignant medullary lesions in the appendicular skeleton of patients with plasma cell diseases using whole-body low-dose computed tomography (CT) and various clinical indicators. The clinical and radiological data of 234 patients with multiple myeloma (mean age, 59.5 ± 8.4; males: 128) who met the inclusion criteria and visited our hospital between December 2020 and February 2023 were retrospectively evaluated. A total of 234 lesions (1 lesion per patient) were categorized into plasma cell tumor (PCT; n = 154) and red bone marrow (n = 80) groups. Intergroup comparisons were carried out using the independent-samples t test, Mann-Whitney U test, or chi-square test. Variables exhibiting statistically significant differences (P < .05) were included in the receiver operating characteristic curve analysis to evaluate diagnostic accuracy. The sensitivity and specificity of a CT value ≥41.5 hounsfield unit (HU) as a diagnostic criterion for PCT were 94.2% and 91.8%, respectively, indicating a diagnostic accuracy of 93.5%. A well-defined boundary as a diagnostic parameter exhibited sensitivity, specificity, and diagnostic accuracy of 88.9%, 93.6%, and 88.7%, respectively. The sensitivity and specificity of the omitted variable (CT value ≥41.5 HU + well-defined boundaries) were 86.4% and 96.5%, respectively, indicating a diagnostic accuracy of 91.6%. CT value ≥41.5 HU and well-defined boundaries are excellent diagnostic variables for diagnosing PCTs.
