Related Experiment Video
Updated: Sep 16, 2026
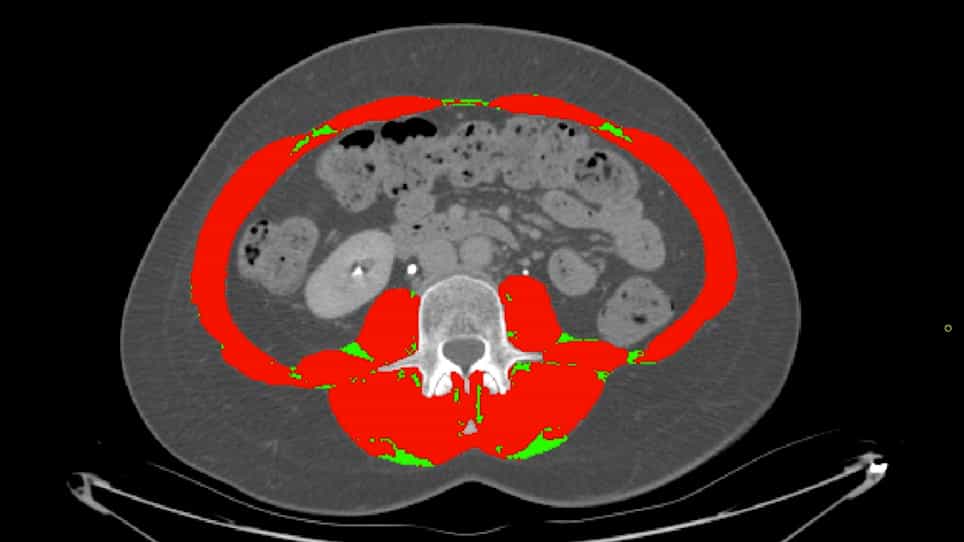

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Computed Tomography-Derived Sarcopenia and Two- Versus Three-Dimensional Body Composition for Prognostication in
Da Wang1,2, Jiaping Sui1, Jiaqi Chen3
1Department of Colorectal Surgery and Oncology, Key Laboratory of Cancer Prevention and Intervention, Ministry of Education, The Second Affiliated Hospital of Zhejiang University School of Medicine, Hangzhou 310001, China.

Abstract:
Background: Skeletal muscle depletion predicts poor outcomes in gastrointestinal cancers, but whether volumetric three-dimensional (3D) body composition adds anything over the standard two-dimensional (2D) single-slice approach in colorectal cancer (CRC) patients receiving chemoradiotherapy is unclear. We quantified CT-derived sarcopenia and directly compared 2D and 3D body composition metrics from a fully automated deep learning pipeline. Methods: We retrospectively analyzed 368 patients with CRC. Body composition was quantified automatically from CT using SMAT-BC, a pipeline combining TotalSegmentator-based vertebral localization with an nnU-Net Residual Encoder XL network incorporating a Transformer bottleneck for four-class tissue segmentation. Single-slice L3 (2D) and L1-L5 volumetric (3D) indices were derived. The primary endpoint was overall survival (OS); recurrence-free survival (RFS) was secondary. Cox proportional hazards models with bootstrap optimism correction were used. Measurement reproducibility was assessed in 25 external TCGA-COAD cases. Results: Sarcopenia was strongly associated with both overall and recurrence-free survival (unadjusted OS HR 2.16, 95% CI 1.55-3.00; unadjusted RFS HR 1.83, 95% CI 1.36-2.47; both raw p < 0.001; adjusted OS HR 1.89, 95% CI 1.57-2.28; adjusted RFS HR 1.44, 95% CI 1.22-1.70; FDR-adjusted p < 0.0001 for both). L3 single-slice indices were strongly correlated with volumetric indices (r = 0.91 for muscle index) and added discriminant value over the clinical model for overall survival (optimism-corrected C-index: clinical 0.602 (95% CI 0.578-0.626), clinical + 2D 0.631 (95% CI 0.609-0.654), clinical + 3D 0.599 (95% CI 0.574-0.624); DeLong p = 0.002 for clinical + 2D vs. clinical, FDR-adjusted p = 0.006). The 2D- and 3D-augmented models yielded overlapping bootstrap confidence intervals and were not clinically meaningfully different in this cohort (OS ΔC = +0.032, 95% CI +0.013 to +0.051; FDR-adjusted p = 0.006; RFS ΔC = +0.008, 95% CI -0.011 to +0.027; FDR-adjusted p = 0.612). Conclusions: Automated CT-derived sarcopenia is an independent predictor of survival in CRC patients receiving chemoradiotherapy. In our cohort, single-slice L3 measurement matched or exceeded volumetric discrimination, but the 2D- and 3D-augmented models yielded overlapping bootstrap confidence intervals for both endpoints: for overall survival, the DeLong FDR-adjusted p value for the 2D-versus-3D contrast was 0.006, and 0.612 for recurrence-free survival. Because no non-inferiority margin was pre-specified, the 2D-3D comparison is presented as exploratory, and we make no formal claim of non-inferiority or equivalence for either endpoint. The findings support single-slice L3 measurement as an efficient biomarker for risk stratification but warrant external validation in larger prospectively designed cohorts.
