Related Experiment Video
Updated: Sep 16, 2026
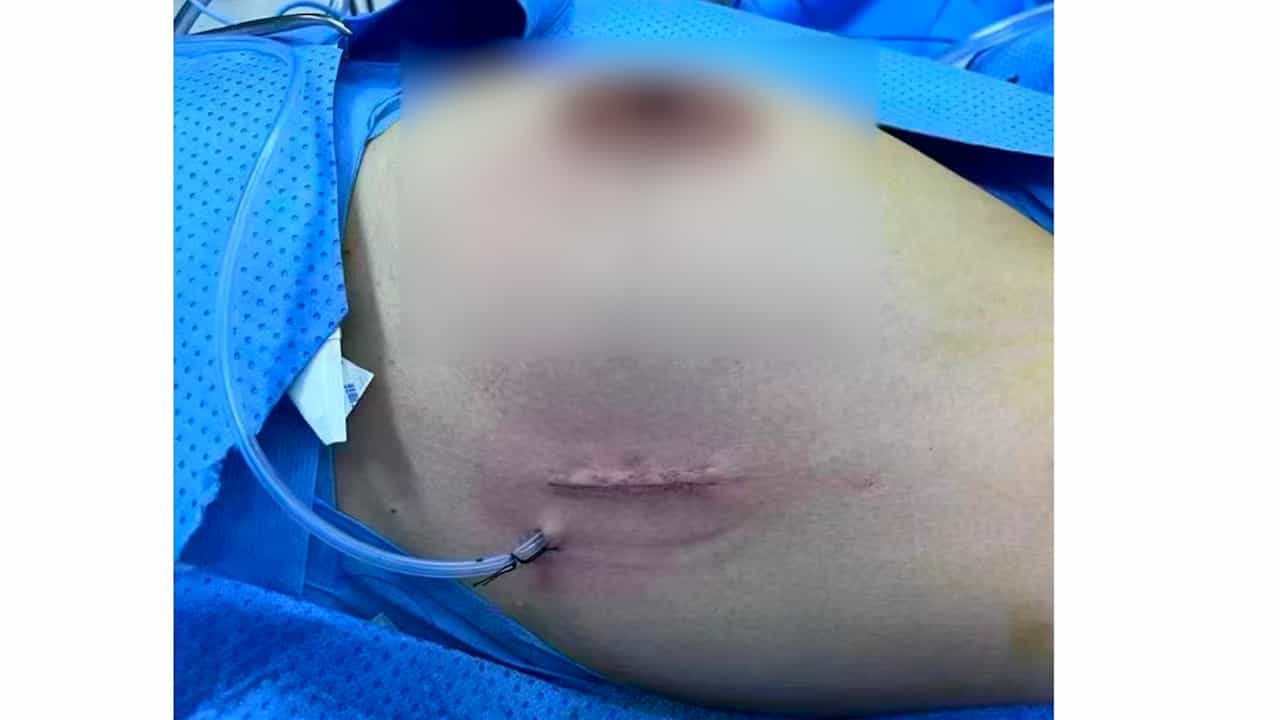

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Radiologic Axillary Response After Neoadjuvant Chemotherapy in cN2 Breast Cancer: Decision Support for Selective
Mehmet Ali Nazlı1, Emel Esmerer1, Sümeyye Yeliz Gümüştaş1
1Department of Radiology, Başakşehir Çam and Sakura City Hospital, 34480 Istanbul, Turkey.

Abstract:
Background/Objectives: Axillary lymph node dissection (ALND) remains common in patients presenting with a high baseline axillary nodal burden despite substantial nodal downstaging after neoadjuvant chemotherapy (NAC). This study evaluated whether post-neoadjuvant radiologic axillary response could support selective axillary de-escalation in patients with clinically staged cN2 breast cancer and pathologically confirmed axillary metastasis. Methods: This retrospective single-center cohort included 166 cases treated between October 2020 and August 2024. All had pathologically confirmed axillary metastasis, completed neoadjuvant systemic therapy, underwent post-treatment axillary ultrasound, and received definitive surgery. Radiologic node-negative status (radN0) was defined by restoration of benign nodal morphology. Surgical management and pathological nodal outcomes were evaluated according to radiologic response. Results: Radiologic nodal clearance occurred in 61/166 cases (36.7%), while axillary pathological complete response [ypN0(i-)] was achieved in 59/166 (35.5%). ypN0(i-) was observed in 53/61 radN0 cases (86.9%) versus 6/105 radN+ cases (5.7%; p < 0.001). Among radN0 cases, 47/61 (77.0%) underwent limited sentinel lymph node biopsy/targeted axillary dissection (SLNB/TAD) without ALND, of whom 43/47 (91.5%) achieved ypN0(i-). Axillary pCR rates varied by molecular subtype, ranging from 20.5% in HR+/HER2- disease to 72.2% in triple-negative disease (p < 0.001). No ipsilateral axillary recurrence occurred in the limited SLNB/TAD group during a median follow-up of 36 months. Conclusions: Post-neoadjuvant radiologic nodal clearance was strongly associated with pathologically node-negative findings and may support consideration of carefully selected responders with cN2 breast cancer for SLNB/TAD-based staging. Radiologic response should complement, rather than replace, surgical staging and multidisciplinary decision-making.
