Related Experiment Video
Updated: Sep 16, 2026
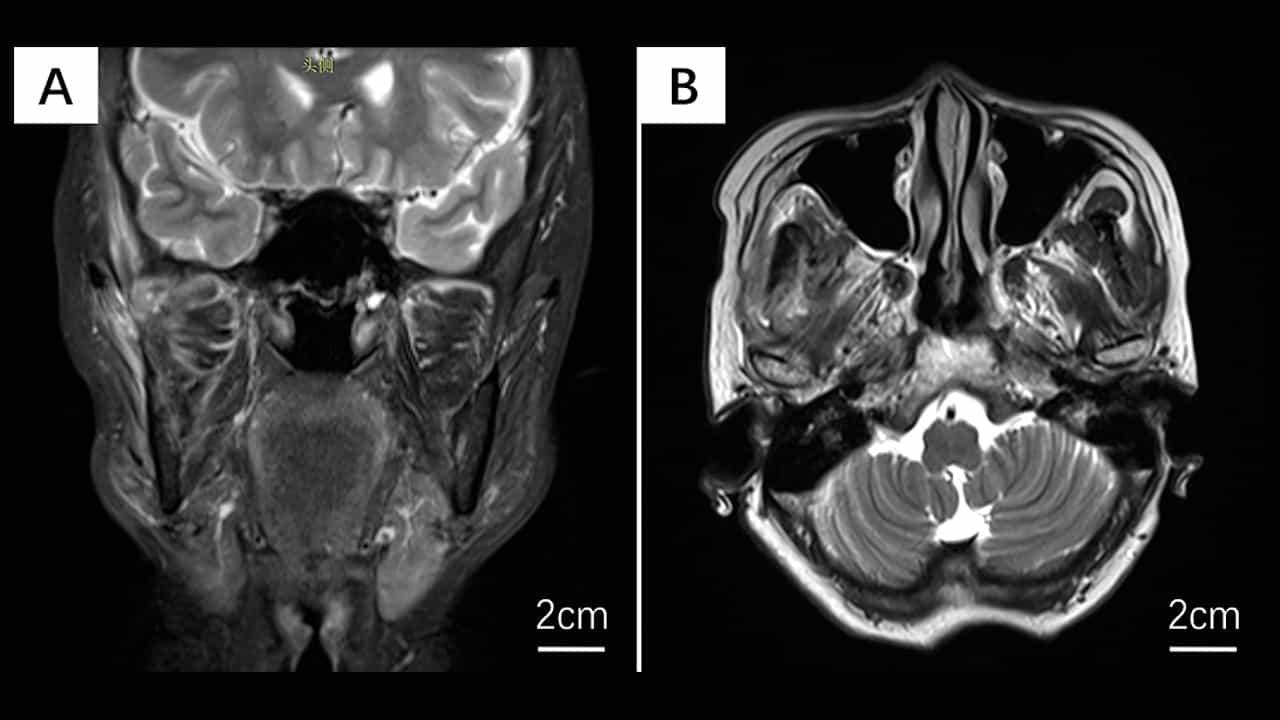
Surgical Treatment of an Endolymphatic Sac Tumor
Published on: May 26, 2023
Translabyrinthine Resection of Posterior Petrous Face Meningiomas: Surgical, Functional, and Oncological Outcomes and
Ufuk Erginoglu1, Taha Sukru Korkmaz1, Bekir Can Kendirlioglu1
1Department of Neurological Surgery, University of Wisconsin School of Medicine and Public Health, Madison, WI 53792, USA.

Abstract:
Background/Objectives: Translabyrinthine (TL) surgery is established for vestibular schwannomas, but its role in a homogeneous posterior petrous face meningioma (PPFM) cohort remains undefined. We characterized surgical, functional, and oncological outcomes and associations with extension and tumor burden. Methods: We retrospectively reviewed 14 patients undergoing TL-only resection at a single institution (2006-2024). Petrosal zones (anterior, middle, posterior) were modeled independently. Outcomes included extent of resection, Simpson grade, complications, tumor control, House-Brackmann (HB) facial nerve (FN) grade, modified Rankin Scale (mRS), and Glasgow Outcome Scale (GOS). Results: Preoperatively, 10 (71.4%) had non-serviceable or absent hearing, and the median diameter was 33.5 mm. Gross or near-total resection was achieved in 85.7% (median extent, 96.2%). At 1 year, 13 of 14 (92.9%) had HB I-II, including all 12 with favorable preoperative function; all had favorable outcomes (mRS 0-2; GOS 4-5). Over a median 65.5-month follow-up, one recurrence and three regrowths occurred, with five patients (35.7%) receiving adjuvant radiation. In exploratory analyses, anterior involvement was associated with a lower likelihood of Simpson grade 1-2 resection (p = 0.025), but not with volumetric extent; tumor diameter correlated with complication burden (ρ = 0.585; p = 0.028), and tumor volume correlated with operative duration (ρ = 0.607; p = 0.021) and hospital stay (ρ = 0.753; p = 0.002). Conclusions: In this first TL-only PPFM series, FN and functional outcomes were favorable and tumor control was acceptable under multimodal management. These findings describe outcomes achievable through the TL corridor in appropriately selected patients rather than an advantage over alternative approaches. Exploratory associations between anterior extension, tumor burden, and outcome require confirmation in larger cohorts.