Related Experiment Video
Updated: Sep 16, 2026
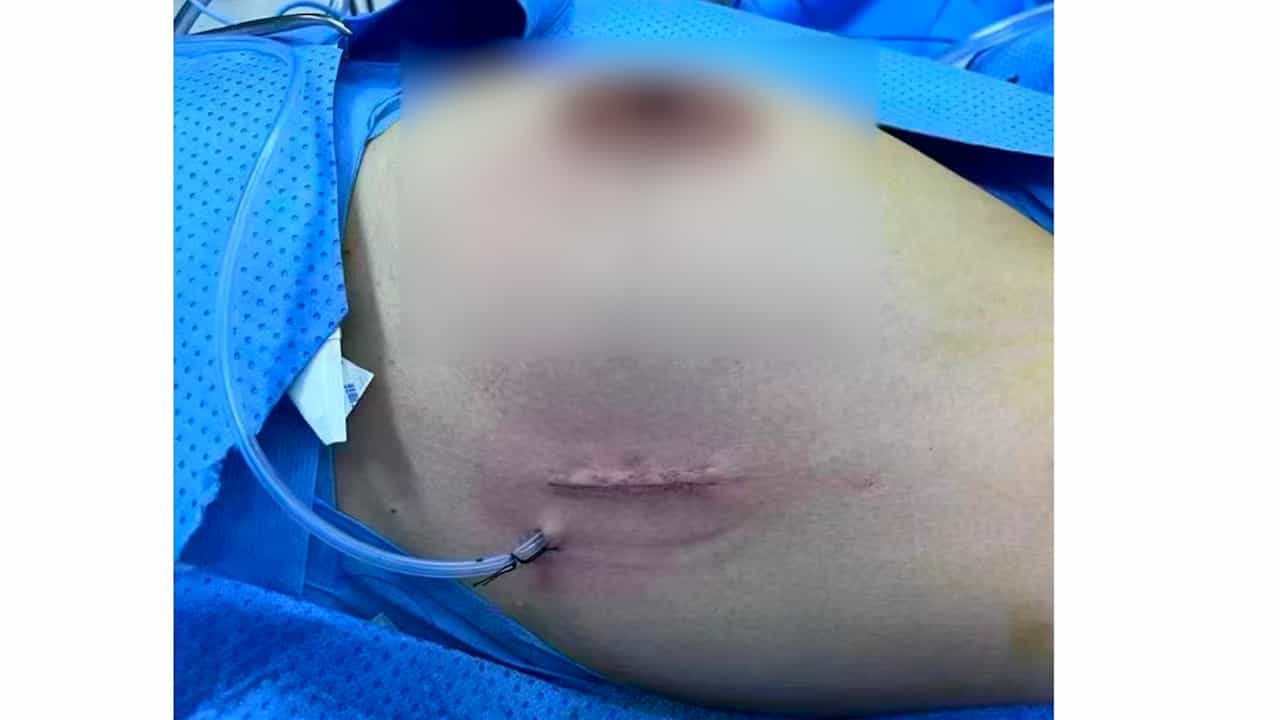

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Pretreatment MRI and Ultrasound Features of the Primary Tumor and Axillary Nodes for Predicting Axillary Pathologic
Shuang Liu1, Yongxin Chen1, Wenjie Tang1
1Department of Radiology, School of Medicine, The Second Affiliated Hospital (Guangzhou First People's Hospital), South China University of Technology, No. 1 Panfu Road, Guangzhou 510180, China.

Abstract:
Background/Objectives: Pretreatment imaging may help estimate axillary response after neoadjuvant chemotherapy (NAC) in clinically node-positive (cN+) breast cancer. This study compared routinely available magnetic resonance imaging (MRI) and ultrasound (US) descriptors from the primary tumor and axillary nodes for predicting axillary nodal response, defined as postneoadjuvant pathologic node-negative status (ypN0). Methods: This retrospective multicenter study included 243 patients from three centers: 146 in the training cohort, 59 in the internal validation cohort, and 38 in the external validation cohort. The index breast tumor and axillary node were identified by a senior radiologist, and two radiologists independently assessed structured descriptors based on BI-RADS 2025. Least absolute shrinkage and selection operator regression and logistic regression were used to develop imaging-only, clinical-only, and clinicoradiologic models. Performance was evaluated using area under the curve (AUC), calibration, decision curve analysis, net reclassification improvement, and integrated discrimination improvement. Results: In the internal and external validation cohorts, the trimodal imaging model achieved AUCs of 0.761 and 0.806, and the clinicoradiologic model achieved the highest AUCs of 0.858 and 0.931, respectively. In pooled validation subgroup analyses, AUCs were 0.928, 0.804, and 0.700 for HR-positive/HER2-negative, HER2-positive, and triple-negative tumors, and 0.898 and 0.880 for cN1 and cN2-3 disease, respectively. Conclusions: MRI tumor descriptors provided the strongest imaging signal for ypN0 prediction, while US descriptors offered modest complementary information. The clinicoradiologic model may support pretreatment risk stratification and multidisciplinary planning for post-NAC axillary reassessment, but should not independently determine sentinel lymph node biopsy, axillary lymph node dissection, or omission of axillary staging.