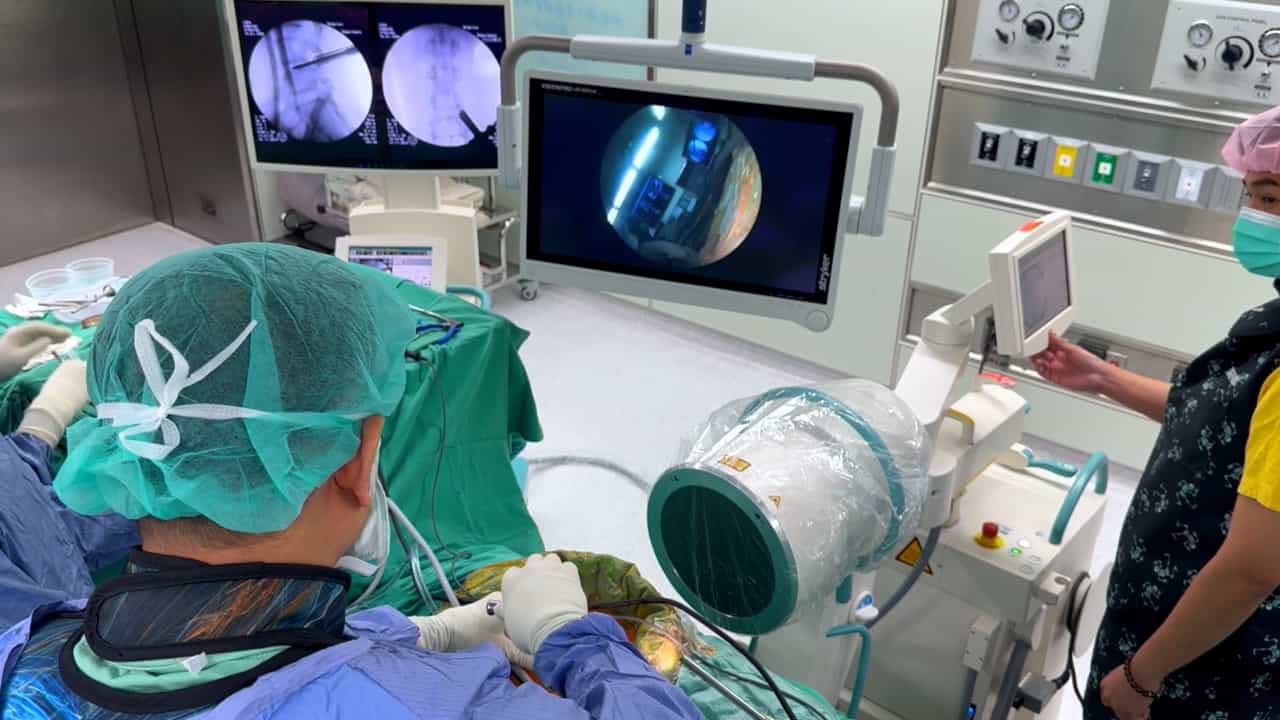
Related Experiment Video
Updated: Sep 16, 2026


C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Management of a Severe L4/5 Andersson Lesion with Three-Column Instability in Ankylosing Spondylitis Using
Chang-Sheng Liao1, Xia Chen1, Zhong-Jie Zhou1
1Department of Orthopaedics, West China Hospital, Sichuan University, Chengdu 610041, China.

Abstract:
Background/Objectives: Andersson lesions are uncommon discovertebral complications of ankylosing spondylitis and may be overlooked when a new mechanical pain pattern is attributed to chronic inflammatory disease. This report describes the diagnostic reasoning, operative decision-making, and short-term outcome of a severe lumbar lesion with three-column instability. Methods: A 38-year-old woman with a 15-year history of ankylosing spondylitis presented with progressive low-back pain, left L5 radiculopathy, and marked functional decline without major trauma. Radiographs, computed tomography, and magnetic resonance imaging were used to characterize the lesion and assess spinal instability and neural compression. A Cawley type E Andersson lesion at L4/5 with severe three-column instability was diagnosed. The patient underwent single-stage posterior-anterior circumferential reconstruction consisting of L4/5 decompression, long-segment L2-S2 fixation, anterior debridement, and tricortical iliac crest grafting. Results: A postoperative gastrocnemius intramuscular venous thrombosis was detected and treated with anticoagulation. At 3 months, the activity-related visual analog scale score improved from 8 to 1, the Oswestry Disability Index improved from 68% to 18%, independent ambulation was restored, and imaging showed stable instrumentation with progressive osseous bridging. At the latest 9-month telephone follow-up, the patient reported maintained pain relief, mobility, and daily function; no new imaging was available. Conclusions: A change from inflammatory to mechanical pain or the development of neurologic findings in ankylosing spondylitis should prompt targeted imaging for an Andersson lesion. In carefully selected patients with severe three-column instability and substantial anterior column deficiency, circumferential reconstruction may provide effective short-term stabilization and functional recovery. Because radiographic follow-up was limited to 3 months, definitive fusion and long-term construct durability cannot be established.