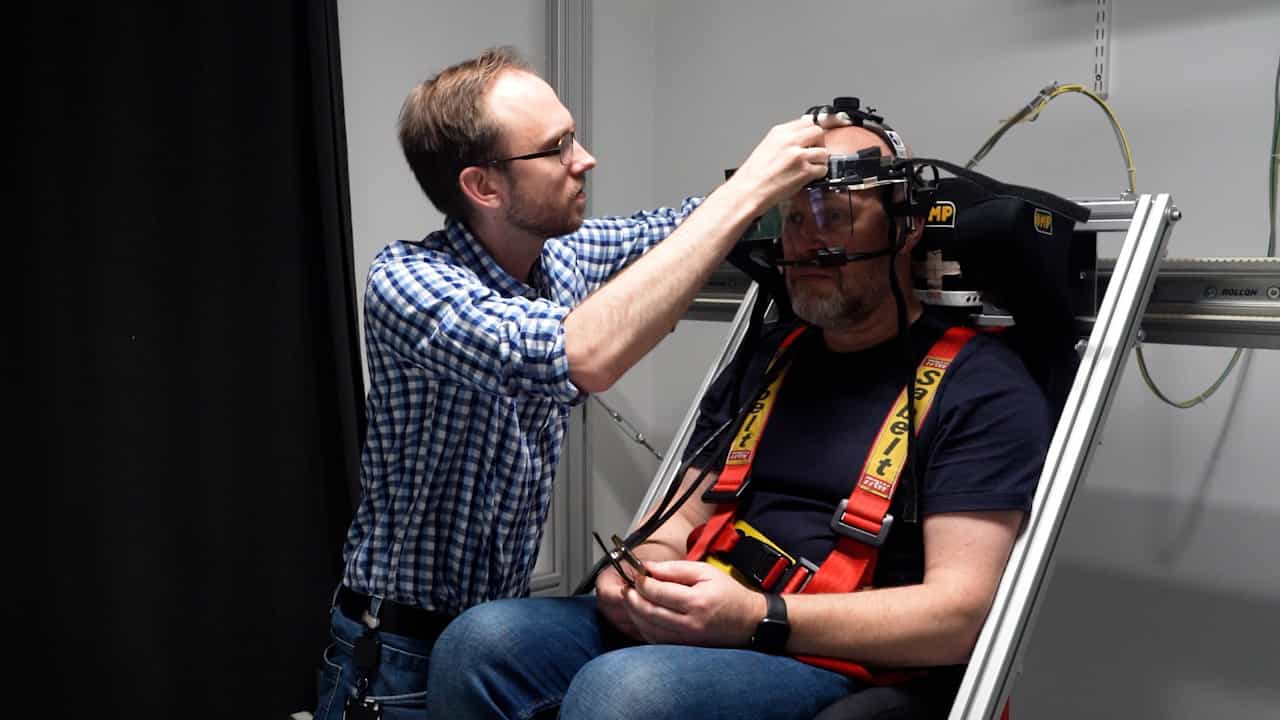
Related Experiment Video
Updated: Sep 16, 2026


Testing of all Six Semicircular Canals with Video Head Impulse Test Systems
Published on: April 18, 2019
Differences in Left-Right Vestibulo-Ocular Reflex Gain in the Video Head Impulse Test
1Department of Otorhinolaryngology-Head & Neck Surgery, Veterans Health Service Medical Center, Gangdong-gu, Seoul 05368, Republic of Korea.

Abstract:
Objectives: The objective of this study was to evaluate left-right symmetry of vestibulo-ocular reflex (VOR) gain on the video head impulse test (vHIT) and its diagnostic implications relative to caloric test results. Methods: Patients presenting with dizziness who underwent a bithermal caloric test and vHIT were retrospectively analyzed. Of 764 patients identified, nine with bilateral vestibular hypofunction were excluded, leaving 755 patients for analysis (451 showing symmetric caloric responses; 304 with unilateral vestibular hypofunction (UVH)). Horizontal VOR gain was compared between directions in subjects with normal caloric responses and according to the affected side in patients with UVH. Subgroup analyses were performed according to caloric weakness severity. Caloric findings were analyzed according to horizontal VOR gain patterns, and the diagnostic performance of isolated unilateral low VOR gain (<0.8) for ipsilateral UVH was evaluated. Results: In subjects with normal caloric results, rightward VOR gain was significantly higher than leftward (1.03 [0.95-1.11] vs. 0.93 [0.87-0.99]; p < 0.001). In patients with UVH, ipsilateral VOR gain was significantly greater in right-sided than in left-sided UVH at comparable levels of caloric weakness. Subgroup analysis showed that this difference was significant in patients with mild-to-moderate caloric weakness. Isolated right low VOR gain was associated with right UVH in 90.5% of cases, whereas isolated left low VOR gain was associated with left UVH in 54.5%; the positive predictive value (PPV) differed significantly between sides (90.5% vs. 54.5%; p = 0.004). Conclusions: Horizontal VOR gain on vHIT showed a left-right asymmetry associated with side-dependent diagnostic performance. When the same VOR gain cutoff was applied to both sides, isolated right low VOR gain had a substantially higher PPV for ipsilateral UVH than isolated left low VOR gain. These findings indicate that the direction of head impulse should be considered when interpreting VOR gain.