Related Experiment Video
Updated: Sep 16, 2026
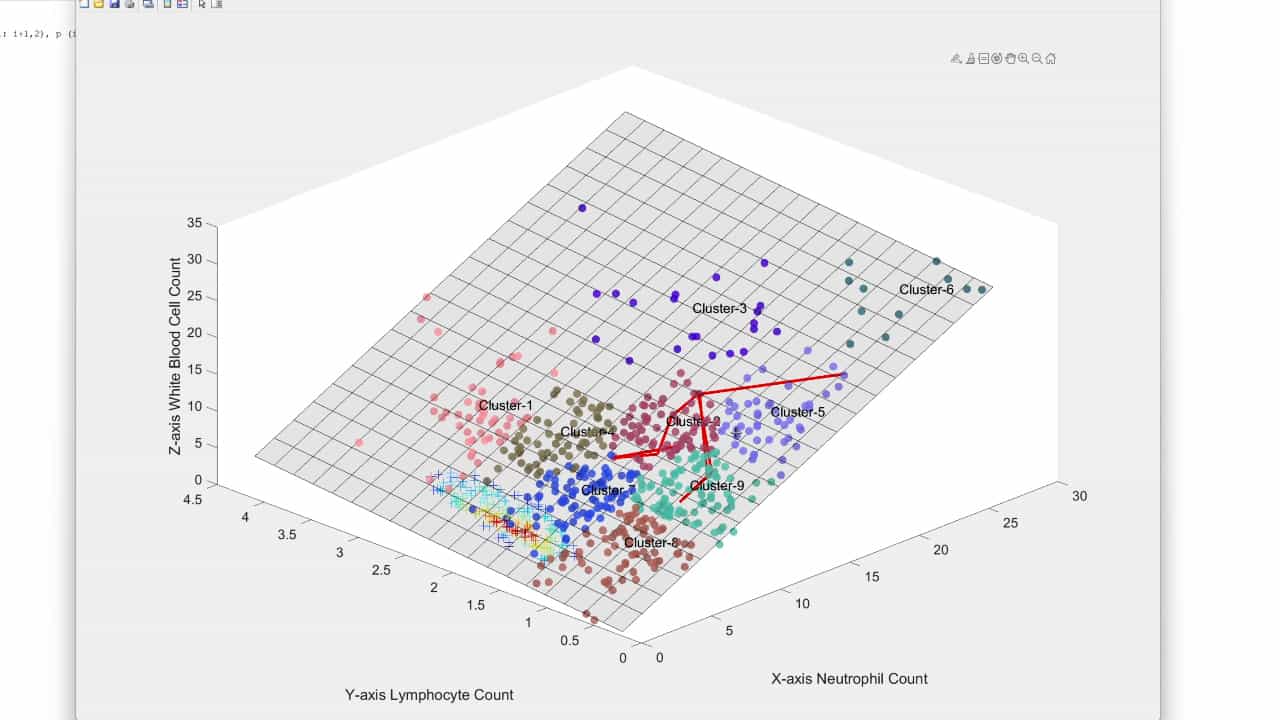

A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Shock index-modified qSOFA improves mortality risk stratification in patients with sepsis beyond conventional qSOFA
Yue Zhou1,2, Yue-Feng He3, Jian Rao2
1Graduate Training Base of Jinzhou Medical University (Chongqing University Fuling Hospital), Chongqing, China.

Background:
The quick Sequential Organ Failure Assessment (qSOFA) score does not incorporate hemodynamic perfusion parameters, which may limit its ability to identify septic patients with early circulatory compromise before the development of overt hypotension. This study aimed to evaluate a modified score incorporating the shock index (SI), termed SI-qSOFA, and to determine whether it could improve identification of high-risk patients classified as low-risk by conventional qSOFA.
Methods:
A retrospective cohort study was conducted, including 2,853 adult patients with sepsis. The primary outcome was in-hospital mortality, while ICU admission was treated as a secondary, exploratory outcome. In addition to evaluating overall predictive performance, a prespecified subgroup analysis was performed in patients with qSOFA < 2 to determine whether SI-qSOFA could identify high-risk patients who would otherwise have been considered low-risk. Discriminative ability was assessed using receiver operating characteristic (ROC) curves. Multivariable logistic regression models were constructed to evaluate independent associations. Calibration was assessed using the bootstrap resampling. Clinical utility was evaluated using decision curve analysis (DCA). Net reclassification improvement (NRI) and integrated discrimination improvement (IDI) were calculated to assess incremental predictive value.
Results:
Among the 2,853 patients, 2,456 (86.1%) had qSOFA < 2. Within this conventionally low-risk subgroup, SI-qSOFA demonstrated good discriminative performance for in-hospital mortality (AUC = 0.79, 95% CI 0.75-0.83) and ICU admission (AUC = 0.83, 95% CI 0.80-0.86), with negative predictive values of 0.98 for both outcomes. In the overall cohort, SI-qSOFA showed slightly higher discrimination than qSOFA for in-hospital mortality (AUC = 0.81 vs. 0.79, DeLong P = 1.78 × 10⁻⁶) and ICU admission (AUC = 0.85 vs. 0.82, DeLong P = 2.48 × 10⁻¹¹). In multivariable analyses, SI-qSOFA remained independently associated with both outcomes. Reclassification analyses demonstrated modest improvement in partially adjusted models; however, incremental value was attenuated in the fully adjusted model for mortality. Calibration was comparable between the two scores. Decision curve analysis indicated a slightly greater net benefit of SI-qSOFA across certain threshold probabilities, particularly for ICU admission.
Conclusion:
SI-qSOFA may improve identification of septic patients with occult circulatory dysfunction who are classified as low-risk by conventional qSOFA. Although the overall improvement in discrimination was modest, SI-qSOFA consistently identified additional high-risk patients within the qSOFA-negative population while maintaining simplicity for bedside application. These findings suggest that SI-qSOFA may serve as a practical adjunctive bedside tool for early sepsis risk stratification and outcome prediction before the development of overt hypotension.
Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Respiratory Failure-III
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care