Related Experiment Video
Updated: Sep 16, 2026
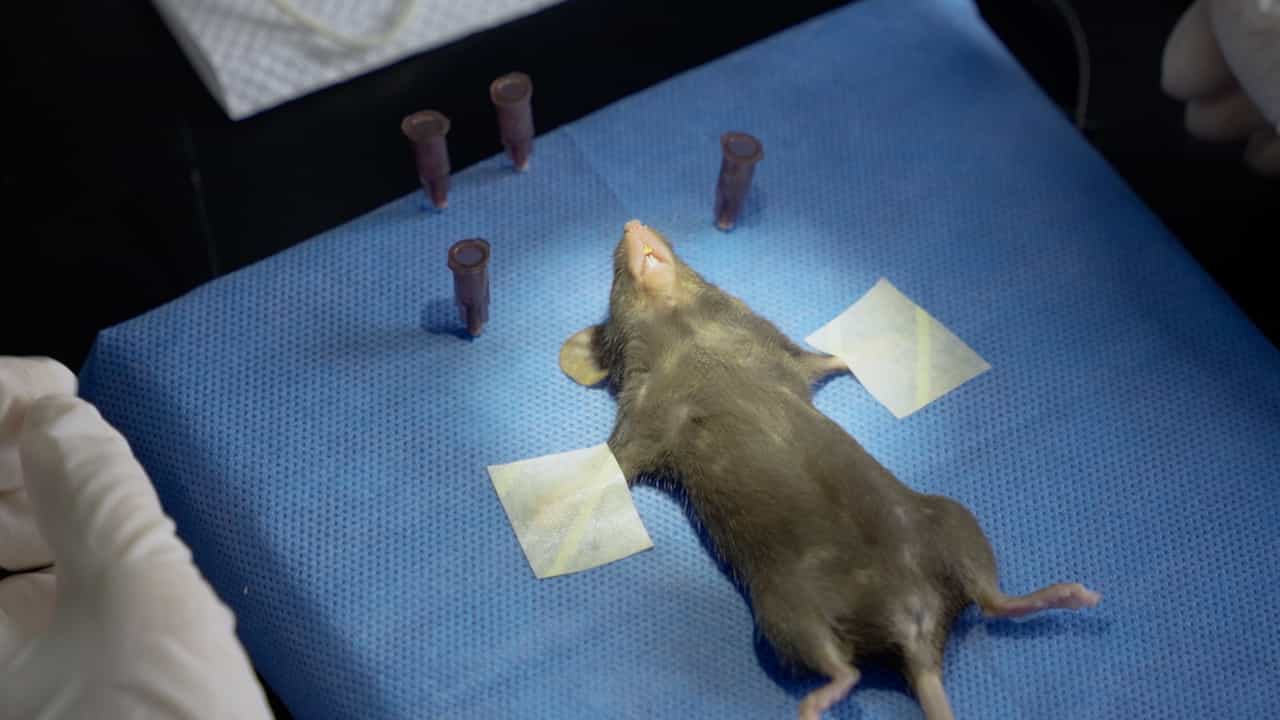

Establishment of an Oronasal Fistula Mice Model
Published on: September 8, 2023
Predictors of Spontaneous Pharyngocutaneous Fistula Closure After Total Laryngectomy
Ernesto Sánchez-LLanos1, Rafael Fernández-Liesa1, Eugenio A Vicente-González2
1Otolaryngology-Head and Neck Surgery, Hospital Universitario Miguel Servet, Zaragoza, ESP.

Objective:
This study aimed to evaluate the rate of spontaneous pharyngocutaneous fistula (PCF) closure after total laryngectomy and to identify clinical, inflammatory, radiotherapy-related, and perioperative factors associated with successful conservative management.
Materials And Methods:
A retrospective observational study was conducted, including patients who underwent total laryngectomy between 2010 and 2025. Clinical, surgical, and oncological variables were collected from medical records. Variables analyzed included demographic characteristics, tumor-related factors, previous treatments, radiotherapy parameters, perioperative laboratory values, surgical details, and postoperative complications. Among patients who developed PCF, fistula characteristics, spontaneous closure, and time to closure were assessed. Univariate and multivariable analyses were performed to identify predictors of spontaneous fistula closure.
Results:
A total of 194 patients were included. PCF developed in 101 patients (52.3%), of whom 66 (65.3%) achieved spontaneous closure with conservative management. Fistula size was the strongest predictor of healing: 84.2% of punctate fistulas closed spontaneously compared with only 8% of large fistulas (p < 0.001; OR 61.3, 95% CI 12.7-295). Hemoglobin levels below 13 g/dL (p = 0.029; OR 2.64, 95% CI 1.09-6.35) and a platelet-to-lymphocyte ratio (PLR) >150 (p = 0.039; OR 2.61, 95% CI 1.03-6.60) were associated with reduced rates of spontaneous closure. Additional factors associated with persistent fistula included radiotherapy within the previous year, hypofractionated radiotherapy, higher acute radiation toxicity, intraoperative use of a Montgomery® salivary bypass tube (MSBT; Boston Medical Products, Westborough, MA, USA), and postoperative complications (infection or bleeding). Kaplan-Meier analysis demonstrated a significantly delayed time to spontaneous closure in patients with a PLR >150 (median 31 vs. 20 days; p = 0.026) and in those with a history of prior radiotherapy (median 25 vs. 17.5 days; p = 0.038). Multivariable analysis identified hemoglobin <13 g/dL, fistula size, intraoperative salivary bypass tube placement, and postoperative complications as independent predictors of failure of spontaneous closure. The predictive model demonstrated good discrimination (area under the receiver operating characteristic curve (AUC) 0.928) and 80% overall accuracy.
Conclusion:
Approximately two-thirds of PCFs after total laryngectomy closed spontaneously under conservative treatment. Fistula size was the most important determinant of healing, while anemia, increased radiation-related toxicity, salivary bypass tube use, and postoperative complications independently predicted persistent fistula. Early identification of these factors may facilitate risk stratification and guide individualized management strategies, helping to optimize the timing of reconstructive intervention.
