Related Experiment Video
Updated: Sep 16, 2026

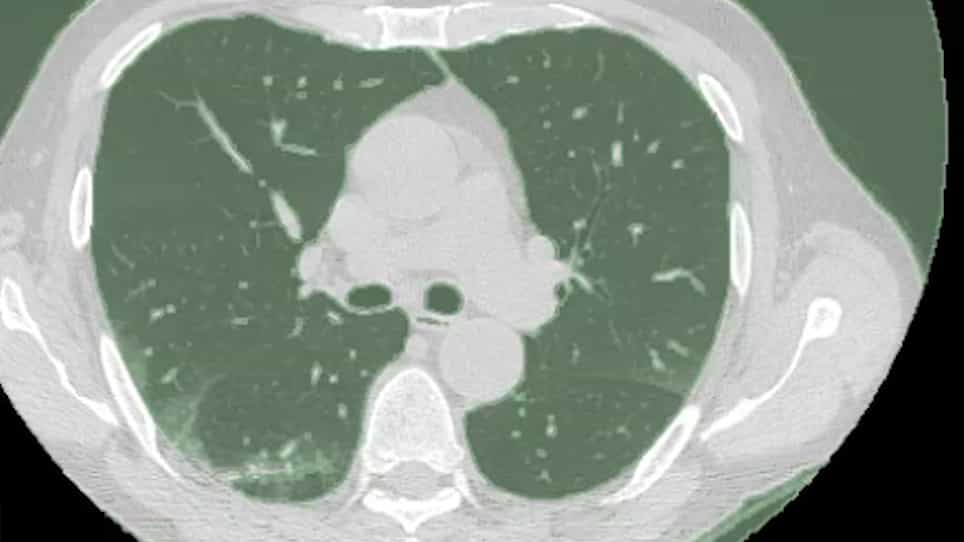
Imaging Features of Systemic Sclerosis-Associated Interstitial Lung Disease
Published on: June 16, 2020
Morphological computed tomography phenotypes in pulmonary sarcoidosis at diagnosis: splitting and lumping based on
Prerana Agarwal1, Louis Jouanjan2, Charlott Terschluse2,3
1Department of Diagnostic and Interventional Radiology, Medical Center University of Freiburg, Faculty of Medicine, University of Freiburg, Freiburg, Germany.

Background:
Sarcoidosis may represent a broad umbrella term for various diseases that induce non-necrotising granulomas in affected organs. A recent multinational consensus proposed distinct computed tomography (CT) phenotypes for pulmonary sarcoidosis; however, the clinical implications remain unclear. What is the prevalence of individual phenotypes in a tertiary referral cohort, and are these phenotypes associated with disease progression?
Materials And Methods:
This retrospective study comprised 232 biopsy-proven pulmonary sarcoidosis patients treated between 2010 and 2020. Baseline CT scans were grouped into 1) non-fibrotic/fibrotic/unclear for fibrosis, and 2) normal/nodular/non-nodular. Disease progression was assessed over 36 months using predefined clinical, functional and therapeutic criteria.
Results:
Most patients had non-fibrotic phenotypes (91.0%, n=211), while fibrotic (5.6%, n=13) and unclear (3.4%, n=8) patterns were less frequent. Inter-reader agreement was moderate for individual phenotypes (κ=0.55) and good for fibrotic versus non-fibrotic classification (κ=0.79). At 36 months, 69% of patients had progressed; all fibrotic cases progressed, compared with 67% of non-fibrotic. Nodular phenotypes progressed in a similar way to normal CT (64% versus 68%) and at a lower rate than non-nodular disease (88%). Fibrotic disease was associated with an increased risk of disease progression after adjustment for age, sex, body mass index and baseline lung function (hazard ratio 2.31, 95% CI 1.21-4.38; p=0.038).
Conclusions:
CT-based phenotype assessment of sarcoidosis seems feasible but may require refinement. Fibrotic patterns predict progression, while nodular phenotypes carry a risk similar to normal CT. Further radiological splitting may not reflect distinct disease behaviour.