Related Experiment Video
Updated: Sep 17, 2026
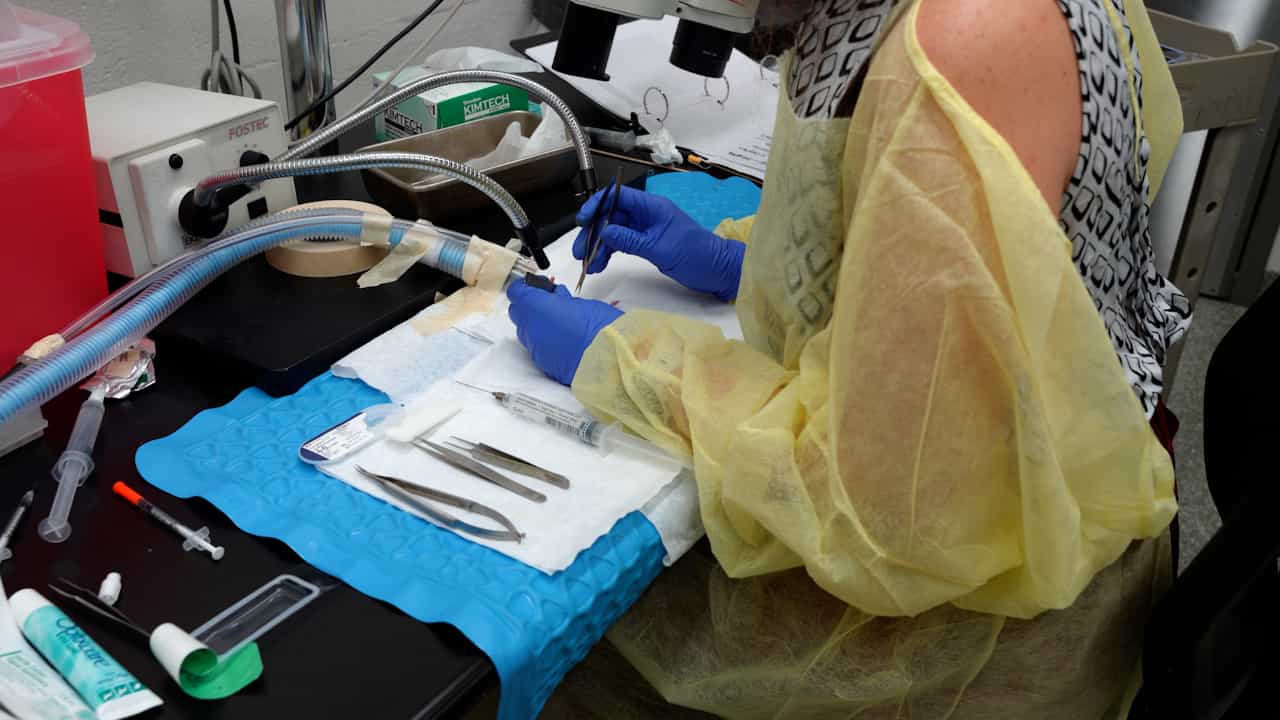

Murine Mesenteric Lymphadenectomy for Selective Disruption of Lymphatic Communication with Region-Specific Gut
Published on: December 30, 2025
Lymphangiography and lymphatic embolization for post-surgical abdominal leaks
Maximilien Lerolle1, Lambros Tselikas2,3, Frédéric Deschamps2
1Therapeutic Imaging Department, Institut Gustave Roussy, Villejuif, France. maximilienlerolle@gmail.com.

Purpose:
Postoperative intra-abdominal lymphatic leaks are uncommon but clinically significant complications after major abdominal tumor surgery. Conservative management is the standard first-line approach, but refractory cases may require lymphangiography with or without lymphatic embolization. This study evaluated the feasibility, safety, and clinical outcomes of lymphangiography-based management in a tertiary oncologic referral center.
Methods:
This retrospective single-center study included adult patients referred between January 2015 and January 2025 for postoperative intra-abdominal lymphatic leakage refractory to conservative management. Presentations included isolated chylous ascites, chylous ascites with lymphocele, and isolated lymphocele. The primary endpoint was clinical resolution without repeat intervention after the index lymphangiography. A stricter definition, excluding patients requiring therapeutic paracentesis or drain placement before resolution, was assessed as a sensitivity analysis. Secondary endpoints included technical success, safety, and exploratory factors associated with outcome.
Results:
Twenty-seven patients underwent 34 lymphangiographic procedures. A lymphatic leak was identified in 23/34 procedures (68%). Embolization was performed in 24/34 procedures (71%) and was technically successful in all cases. Clinical resolution without repeat intervention after the index lymphangiography was achieved in 18/27 patients (67%), while final clinical resolution after one or more lymphangiography-based procedures was achieved in 21/27 (78%). Seven patients required temporary paracentesis or drain placement before recovery, yielding a strict success rate of 14/27 (52%). No procedure-related major complication occurred. High lumbar-aortic leak location was associated with lower clinical resolution in exploratory analysis.
Conclusion:
In this small, heterogeneous retrospective cohort, lymphangiography with or without embolization appeared feasible and safe for refractory postoperative intra-abdominal lymphatic leaks. Clinical outcomes were sensitive to endpoint definition, and the association between high lumbar-aortic leak location and poorer outcome should be considered hypothesis-generating. Larger prospective multicenter studies are needed to validate these findings.