Related Experiment Video
Updated: Sep 17, 2026

Real-World M3-BREATHE: Toward Multimodal Mobile Monitoring of Behaviour, Respiration, and Exposures for Treatment and Health Evaluation
Published on: June 5, 2026
Exposure-response relationship between ambient PM2.5 and SO2 with COPD and SAD prevalence among individuals at high
Jinliang Meng1,2, Geyi Wen2,3,4, Guoyu Ma5
1Yunnan Provincial Key Laboratory of Public Health and Biosafety & School of Public Health, Kunming Medical University, Kunming, Yunnan, China.

Background:
Ambient air pollution is a major risk factor for chronic obstructive pulmonary disease (COPD) and small airway dysfunction (SAD). However, evidence on their nonlinear exposure-response relationships and effect thresholds remain insufficient, and most identified thresholds lack clinical relevance evaluation. This study aimed to examine the nonlinear links of PM2.5 and SO2 exposure with the prevalence of COPD and SAD, identify effect thresholds, and compare clinical characteristics across subgroups stratified by these threshold values.
Methods:
A cross-sectional study was conducted in Yunnan Province from 2021 to 2022, enrolling 11,095 permanent residents aged ≥20 years via multistage random cluster sampling. High-risk individuals were screened using COPD-SQ/COPD-PS questionnaires and received standardized pulmonary function testing. COPD was diagnosed per GOLD guidelines. SAD was defined as at least two of maximal mid-expiratory flow (MMEF), forced expiratory flow at 50% of vital capacity (FEF50%), and forced expiratory flow at 75% of vital capacity (FEF75%) below 65% of predicted values. Restricted cubic spline models were used to assess nonlinear relationships and identify thresholds. Stratification analyses were performed to compare clinical symptoms and lung function between exposure groups, and random forest models were used to evaluate the importance of exposure-related factors.
Results:
Among high-risk participants, COPD and SAD prevalence were 27.2 % and 53.6%, respectively. Significant nonlinear exposure-response relationships were observed for both PM2.5 and SO2 with both outcomes (all P < 0.001). The effect thresholds were identified as 21.33 μg/m3 for PM2.5 and 8.67 μg/m3 for SO2. Among those with PM2.5 > 21.33 μg/m3, the prevalence of COPD and SAD was 33.4% and 58.4%, respectively; among those with SO2 > 8.67 μg/m3, the corresponding prevalence was 30.2% and 57.4% (all P < 0.05). In addition, high exposure groups had significantly higher prevalence of cough and dyspnea, as well as → poorer lung function (FEV1, FVC, and FEV1 /FVC), compared with low exposure groups. Air pollution was the associated factor for both outcomes, exceeding smoking and biomass fuel exposure.
Conclusion:
Nonlinear relationships exist between PM2.5/SO2 exposure and the prevalence of COPD and SAD, with core thresholds of 21.33 μg/m3 (PM2.5) and 8.67 μg/m3 (SO2). In high-risk individuals and COPD patients, exposure above these thresholds correlates with more severe respiratory symptoms and poorer lung function, illustrating the thresholds' clinical relevance.

Related Concept Videos
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
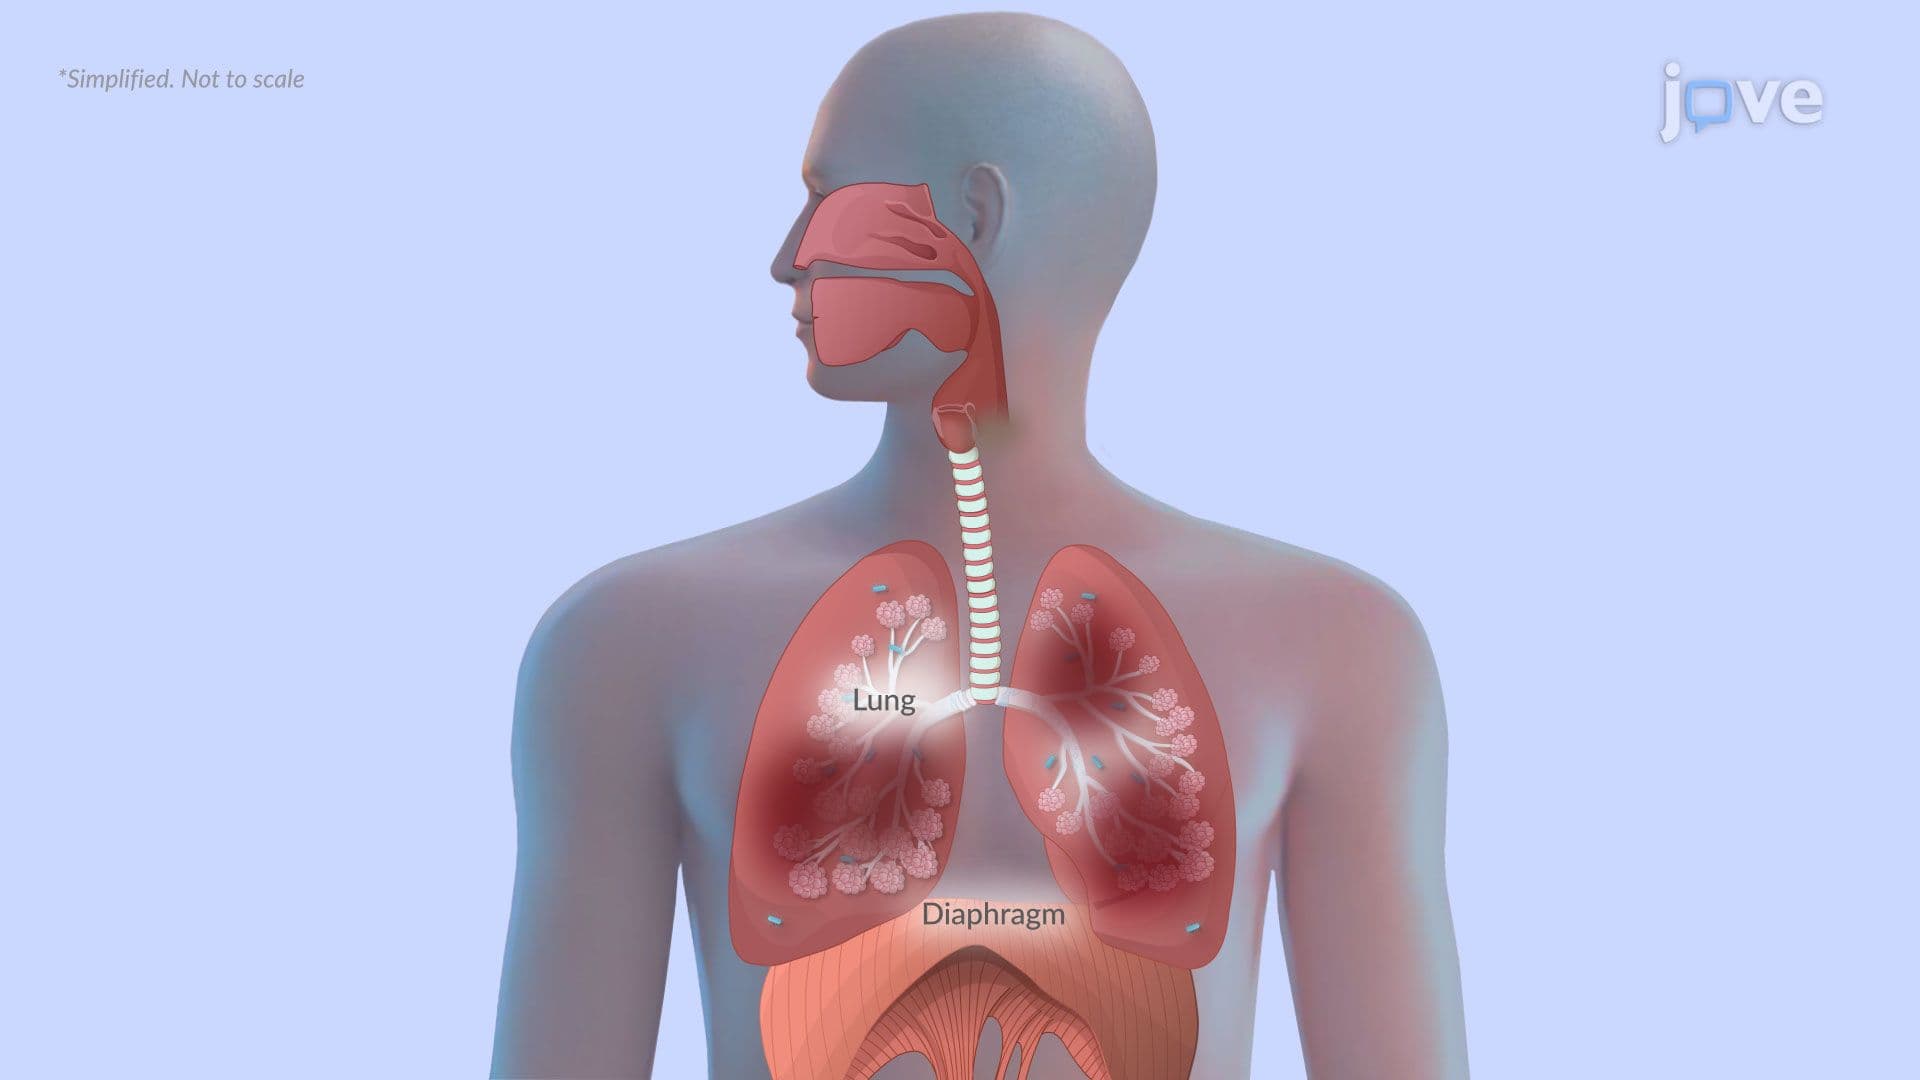
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation