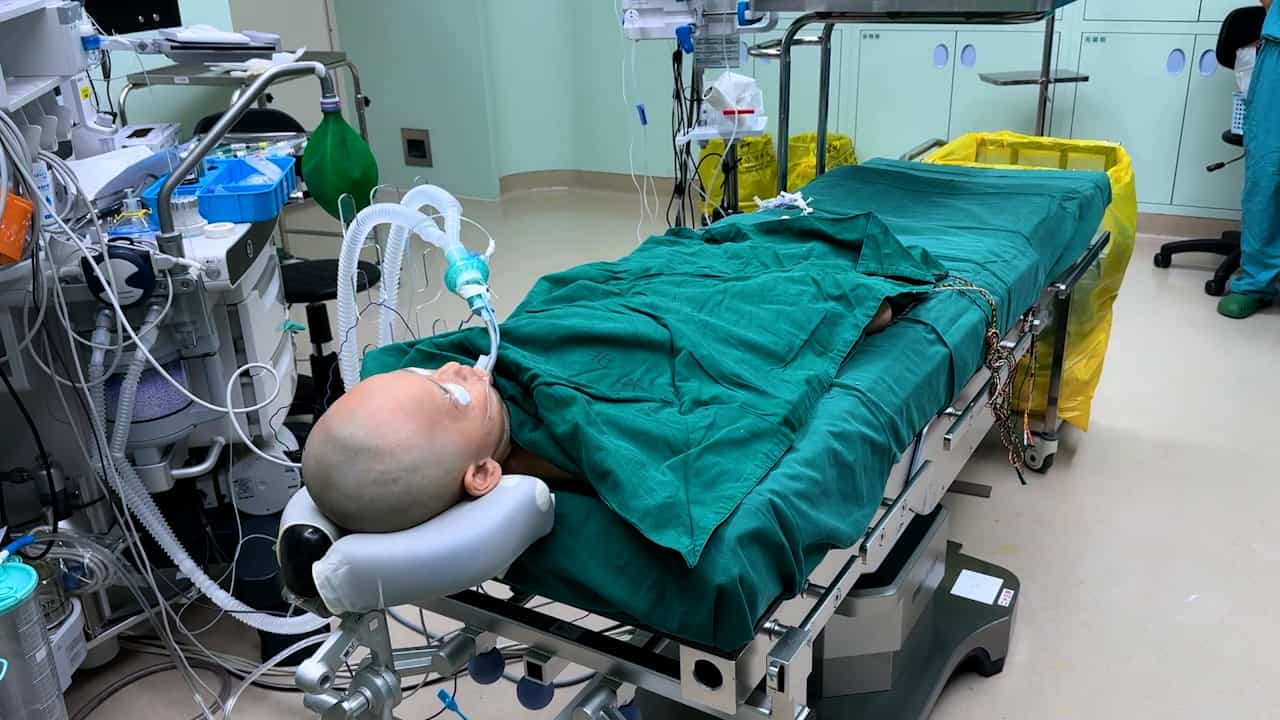

A 21-Year Diagnostic Odyssey in TBC1D24-Associated Developmental and Epileptic Encephalopathy With Favorable Response
Alfredo Pacheco-Abbud1, Alan Alberto Pérez-Arzola1, Adlen S Martínez Torres1
1Neurology, "Dr. José Eleuterio González" University Hospital, Monterrey, MEX.

Abstract:
Developmental and epileptic encephalopathies (DEEs) are one of the most important causes of seizures occurring during the early years of life. Establishing an etiologic diagnosis remains challenging in many affected individuals. Next-generation sequencing (NGS), such as whole-exome sequencing (WES) or targeted gene-panel sequencing, has therefore become a useful tool for identifying these patients. One of the genes implicated in DEEs is TBC1D24. Recessive pathogenic variants in this gene cause a broad phenotypic spectrum that includes familial infantile myoclonic epilepsy, early infantile epileptic encephalopathy 16, and deafness, onychodystrophy, osteodystrophy, mental retardation, and seizures (DOORS) syndrome, among other disorders. No specific treatment is currently available for DEE caused by TBC1D24 variants. We therefore present the case of a Mexican male patient with a homozygous TBC1D24 variant who underwent a 21-year diagnostic odyssey and showed a favorable response to corpus callosotomy. A 22-year-old right-handed man was evaluated for refractory convulsive status epilepticus. His family history was notable for an older brother who died at 32 years of age from an undetermined cause and had epilepsy beginning at two months of age, intellectual disability, apparent hemiclonic seizures, and an unspecified visual disorder. The patient had global developmental delay involving the motor, language, and cognitive domains. Since disease onset, he had experienced recurrent episodes of status epilepticus that did not respond adequately despite stepwise adjustments to antiseizure therapy and the use of sedation during periods of greatest ictal activity. Palliative surgical treatment with anterior corpus callosotomy was therefore performed, resulting in a reduction in overall seizure burden, focal seizure frequency, recurrence of status epilepticus, and the need for rescue medication. Given the history of epileptic encephalopathy, intellectual disability, global developmental delay, drug resistance, recurrent status epilepticus, and a deceased brother with a similar neurological phenotype, genetic sequencing was performed and identified the homozygous TBC1D24 variant c.845C>G (p.Pro282Arg), classified as likely pathogenic. The clinical, neuroimaging, and genetic findings supported a diagnosis of TBC1D24-associated DEE 16 with an autosomal recessive inheritance pattern. A multidisciplinary approach is the cornerstone of follow-up for all patients, particularly those with difficult-to-control clinical manifestations and a family history of similar disorders.
