Who can benefit from percutaneous left atrial appendage closure? Recent advances
Related Experiment Video
Updated: Sep 17, 2026
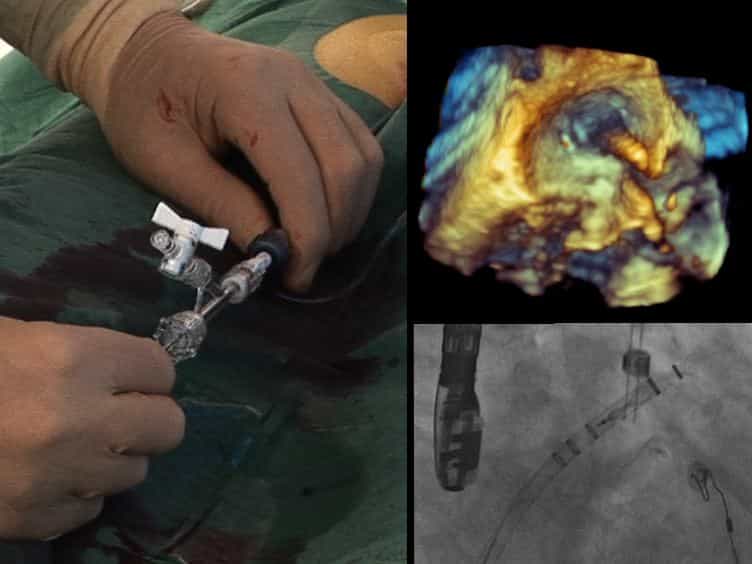
Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Pavel Osmancik1, Marek Hozman1
1Department of Cardiology, University Hospital Kralovske Vinohrady, Charles University, Prague, Czech Republic.

Abstract:
Atrial fibrillation (AF) confers a substantial risk of stroke. Direct oral anticoagulants (DOACs) are highly effective for stroke prevention, and they form the cornerstone of AF management. Nevertheless, many eligible patients do not receive or do not maintain long-term anticoagulation because of bleeding risk, prior hemorrhage, or other contraindications. Percutaneous left atrial appendage closure (LAAC) has emerged as a nonpharmacological alternative to anticoagulation. In 2026, 2 major randomized trials addressing the role of LAAC as an alternative to anticoagulation were published: CHAMPION-AF (WATCHMAN FLX Versus NOAC for Embolic Protection in the Management of Patients With Non-Valvular Atrial Fibrillation) and CLOSURE-AF (Left Atrial Appendage Closure in Patients With Atrial Fibrillation Compared to Medical Therapy). The CHAMPION-AF study randomized 3000 lower-risk AF patients to LAAC (Watchman FLX) or DOAC. LAAC met noninferiority criteria for the composite efficacy end point of cardiovascular death, stroke, and systemic embolism (5.7% vs 4.8% at 3 y; hazard ratio [HR], 1.2; 95% CI, 0.87-1.66) and demonstrated superiority for nonprocedure-related bleeding (10.9% vs 19%; HR, 0.55). Ischemic stroke alone, however, was numerically more frequent following LAAC (HR, 1.61), an unexpected finding not observed in prior LAAC trials. The CLOSURE-AF study enrolled a substantially higher-risk population with a more adverse bleeding profile. LAAC failed to demonstrate noninferiority to best medical therapy for the composite primary end point consisting of cardiovascular death, stroke, systemic embolism, and major bleeding (16.8 vs 13.3 events per 100 patient-years), driven by higher mortality and more bleeding events in the device group. This review critically appraises the design, outcomes, and clinical implications of both trials in the context of previous trials, discusses methodological issues, including noninferiority margin selection and bleeding-end point definitions, and outlines implications for patient selection for LAAC.

Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:27
Peripheral Artery Disease III: Interprofessional Care