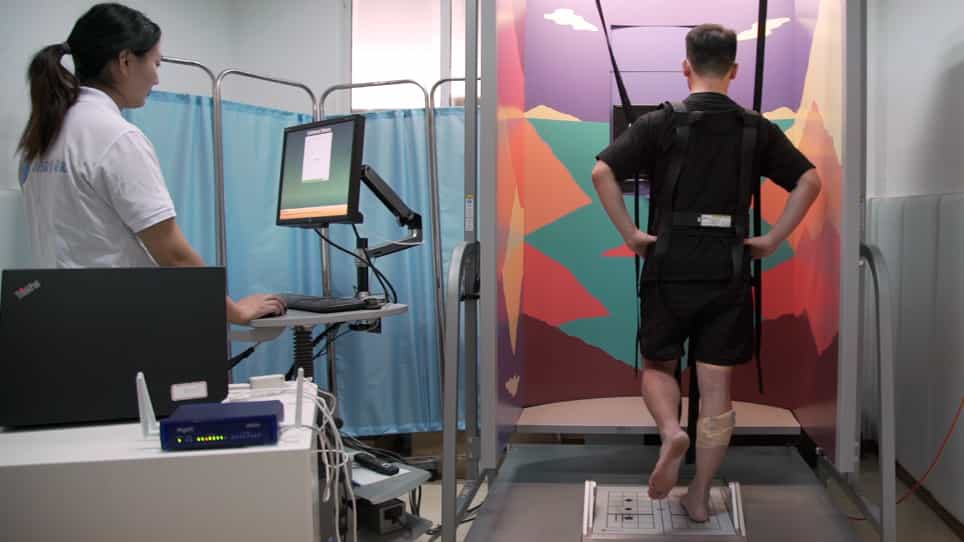
Related Experiment Video
Updated: Sep 18, 2026


Clinical-oriented Three-dimensional Gait Analysis Method for Evaluating Gait Disorder
Published on: March 4, 2018
Compensatory proximal malalignment despite preserved macroscopic gait in pediatric flexible flatfoot: A dual-level
Haojie Wang1, Mengxiang Li1, Xiaomeng Liang1
1The Third Department of Sports Medicine, Wangjing Hospital, China Academy of Chinese Medical Sciences, Beijing, China.

Background & Objective:
Previous biomechanical studies on pediatric flexible flatfoot have treated the subject as a single analytical unit, thus failing to elucidate mechanical transmission within the lower extremity closed kinetic chain. This study investigates the impact of distal arch collapse on macroscopic gait parameters, static joint alignment, and dynamic kinematic deviation by integrating a dual-level analytical strategy at both the subject and individual limb levels.
Methods:
153 children with pediatric flexible flatfoot (25 unilateral, 128 bilateral) were included, and 3D gait data from 306 lower extremities were analyzed. At the subject level, macroscopic spatiotemporal parameters were compared using the Mann-Whitney U test. At the limb level, linear mixed-effects models (LMMs) compared static 3D joint angles and Gait Variable Scores (GVS) between normal feet and flatfeet, treating subject as a random effect and adjusting for age, body mass index (BMI), and unilateral leg length.
Results:
At both the subject and limb levels, no significant between-group differences were observed in any core spatiotemporal parameters (e.g., Mean Velocity, Frequency, and Step Width) (P > 0.05). Regarding static joint alignment at the limb level, the static Hip Rotation angle on the flatfoot side exhibited significantly less external rotation (i.e., relative internal rotation) compared to the normal side (-2.11° ± 0.67° vs. -5.79° ± 1.79°, P = 0.043). During dynamic walking, the Hip Abduction/Adduction GVS on the flatfoot side was significantly elevated (P = 0.032). However, comprehensive gait indices, including the GDI and GPS, showed no significant overall between-group differences.
Conclusion:
Pediatric flexible flatfoot was associated with subtle proximal biomechanical alterations despite preserved macroscopic gait characteristics. Changes in static hip alignment and dynamic frontal-plane hip kinematics may therefore provide complementary information beyond conventional gait measures, supporting a broader kinetic-chain assessment in clinical evaluation and follow-up.