Related Experiment Video
Updated: Sep 18, 2026


Acquisition of Resting-State Functional Magnetic Resonance Imaging Data in the Rat
Published on: August 28, 2021
Management of Patients with Medetomidine Withdrawal During Interfacility Transfer
Justin K Kenney1, Michael J Lynch1, Anthony F Pizon1
1Department of Emergency Medicine, University of Pittsburgh School of Medicine, Pittsburgh, Pennsylvania.

Objectives:
Alpha-2 agonists including medetomidine are becoming increasingly prevalent as adulterants in the United States opioid supply. Complicated withdrawal following use of these agents is characterized by severe symptoms including agitation and nausea, often requiring treatment with high-dose dexmedetomidine infusion and transfer between community emergency departments and tertiary critical care units. We aimed to describe interventions and outcomes of patients undergoing interfacility transport while receiving a dexmedetomidine infusion for medetomidine withdrawal to inform safe transfer practices for this patient population.
Methods:
We performed a retrospective observational cohort study of consecutive non-intubated patients receiving dexmedetomidine infusion for management of suspected medetomidine withdrawal transported by a regional critical care transport agency between March 2024 and February 2026. We identified clinical characteristics, characterized withdrawal symptoms, and identified the incidence of and indications for supplemental medical therapy provided during transport. We also identified the prevalence of hemodynamic instability, hypoxia, or need for advanced airway interventions.
Results:
Among the 100 patients receiving dexmedetomidine infusion for suspected medetomidine withdrawal, most experienced agitation (53%), nausea/vomiting (58%), tachycardia/bradycardia (62%), or hypertension (71%) upon or prior to crew arrival. During transport, 10% of patients received dexmedetomidine titration, 12% received additional antiemetics, 9% received sedatives, and 1% received vasoactive infusion for hypotension. No patients received additional sedative infusions. Many patients exhibited hypertension (systolic blood pressure [SBP] > 140 mmHg; 78%) or profound hypertension (SBP >180 mmHg or diastolic BP >110 mmHg; 39%). Patients also experienced tachycardia (heart rate [HR] > 120; 35%), bradycardia (HR <50; 6%), or hypotension (SBP <90 mmHg; 6%). Only 3% of patients experienced hypoxia (SpO2 < 90%), or were treated with supplemental oxygen, and no patients required advanced airway management.
Conclusions:
Patients undergoing transport while receiving dexmedetomidine infusion for suspected medetomidine withdrawal were commonly hypertensive and rarely hypoxic. While some patients required additional antiemetic or sedative medications, no patients required alternate sedative infusions, most remained stable on the dexmedetomidine infusion, and need for vasopressors was very rare. Early symptom recognition and pharmacologic alpha-2 agonism are likely key in prehospital management of this toxidrome, which can safely be continued during interfacility transport.

Related Concept Videos
 01:17
Sedatives and Hypnotics Drugs: Miscellaneous Agents
Melatonin congeners like ramelteon (Rozerem) and tasimelteon (Hetlioz) selectively bind to melatonin receptors (MT1 and MT2) and thus mimic the actions of melatonin, a hormone that regulates sleep-wake cycles. Tasimelteon is primarily used for non-24-hour sleep-wake disorder, common in blind patients. They are also used to treat conditions like insomnia...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:14
CNS Depressants: Barbiturates and Benzodiazepines
 01:24
Parenteral Anesthetics: Overview
 01:22
Stages of General Anesthesia
 01:28
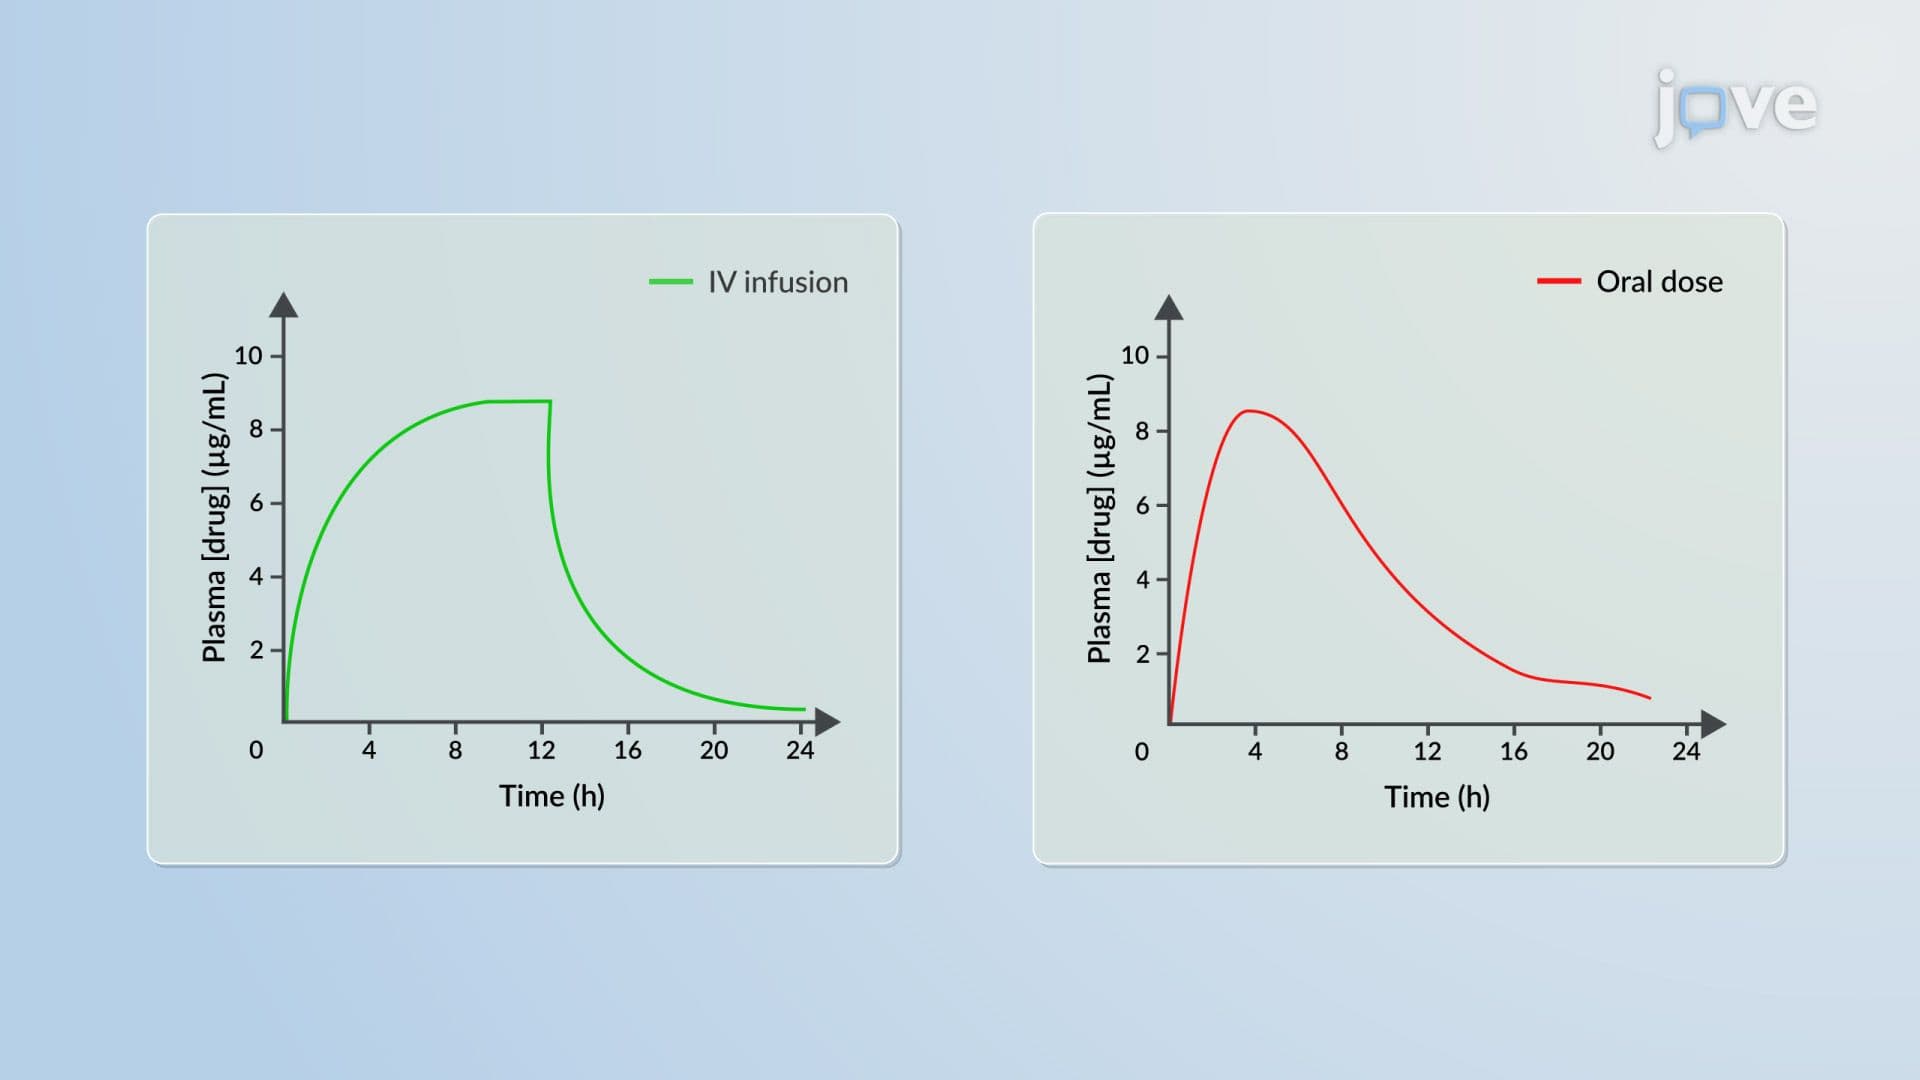
IV Infusion to Oral Dosing: Conversion Methods