Related Experiment Video
Updated: Sep 18, 2026
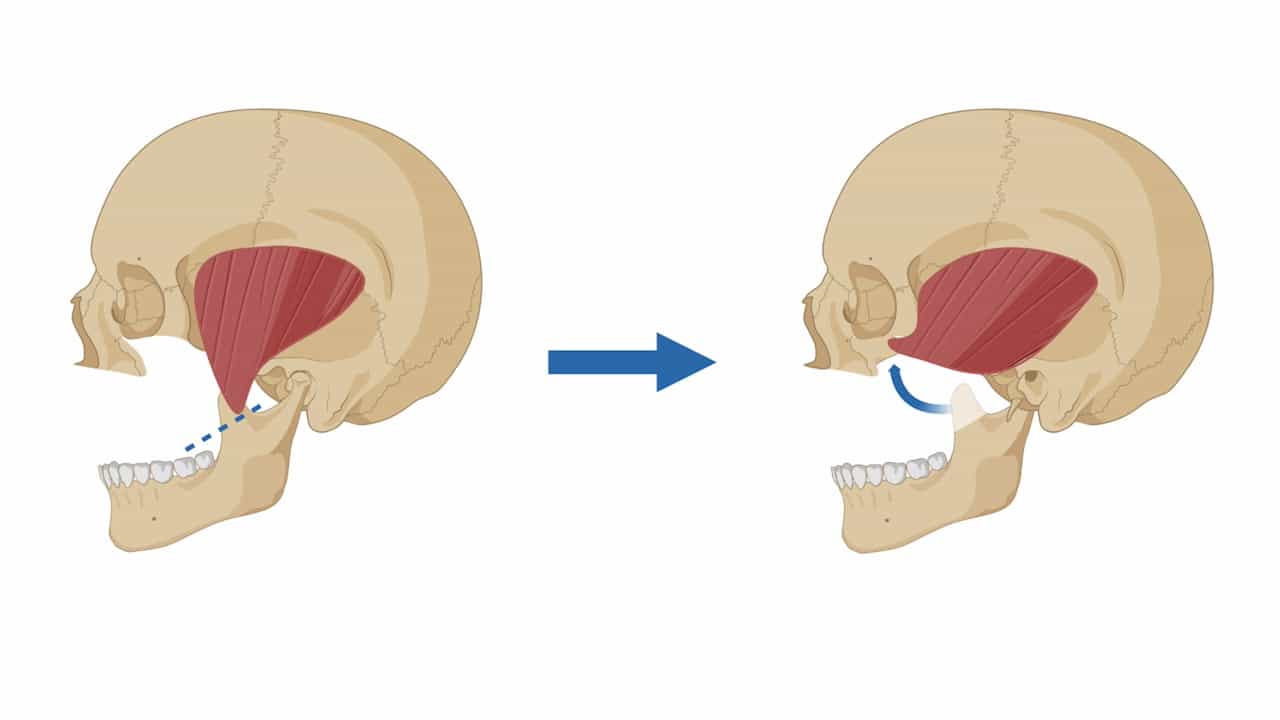

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Multilayer free-graft reconstruction with platelet-rich plasma augmentation for nasoseptal flap-sparing in endoscopic
Çağlar Günebakan1, Usame Rakip2, Selçuk Kuzu1
1Afyonkarahisar Health Sciences University Medical Faculty, Otorhinolaryngology, Head-Neck Surgery Department, Afyonkarahisar, Türkiye.

Objective:
To prospectively evaluate the feasibility and safety of nasoseptal flap avoidance using a standardized multilayer free-graft reconstruction augmented with autologous platelet-rich plasma (PRP) in anatomically favorable transsphenoidal surgeries.
Methods:
This prospective single-center feasibility study included 42 consecutive patients undergoing endoscopic transsphenoidal surgery for Hardy grade A-C, Knosp grade 0-2 pituitary adenomas and comparable sellar lesions between January 2020 and March 2024. Skull base reconstruction employed a standardized multilayer technique consisting of intrasellar fat obliteration, inlay fascia lata graft, a PRP-augmented biological layer, onlay fascia lata graft, and absorbable gelatin sponge buttress. The primary outcome was the 30-day postoperative cerebrospinal fluid (CSF) leak rate. An exploratory analysis examined the association between suprasellar extension and postoperative CSF leak.
Results:
Mean age was 51.1 ± 13.7 years. Pathologies included pituitary adenoma (n = 35, 83.3%), Rathke cleft cyst (n = 3), and other sellar lesions (n = 4). Intraoperative CSF communication was encountered in 23 cases (54.8%). Postoperative CSF leak occurred in 3 patients (7.1%; 95% CI: 1.5-19.5%). All observed postoperative CSF leaks were confined to patients with suprasellar extension ≥12 mm (3/13, 23.1%), whereas no leaks were observed in lesions with <12 mm extension (0/29, 0%; p = 0.025, Fisher's exact test). All leaks resolved with conservative management. No nasal complications such as septal perforation or major epistaxis were observed. Mean hospital stay was 4.3 ± 2.5 days, and no surgical reintervention was required during a mean follow-up of 19.2 ± 11.4 months. Detailed intraoperative findings and postoperative outcomes are summarized in Table 2.
Conclusions:
In this prospective feasibility study, multilayer free-graft reconstruction augmented with autologous PRP was feasible for nasoseptal flap avoidance in selected low-risk transsphenoidal cases, with a postoperative CSF leak rate comparable to published series. An exploratory association between suprasellar extension ≥12 mm and increased leak risk was observed, warranting further validation. This flap-sparing approach can be considered in carefully selected patients where nasal preservation is prioritized, though comparative studies are needed to define its role relative to vascularized flap reconstruction.