Related Experiment Video
Updated: Sep 18, 2026
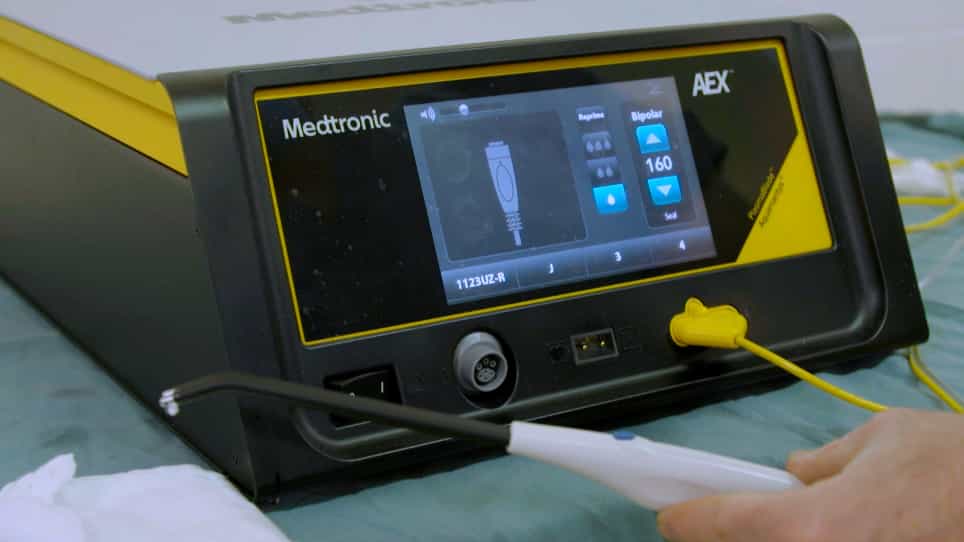

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Hemorrhage control in hemodynamically unstable pelvic fractures using external fixation, angioembolization, or
Stijn De Bondt1, Anmol Kaur2, Mattias Gilleir2
1Department of Radiology, UZ Leuven, Herestraat 49 3000, Leuven, Belgium; Department of Traumatology, UZ Leuven, Herestraat 49 3000, Leuven, Belgium.

Introduction:
Multiple hemorrhage control methods for hemodynamically unstable pelvic fractures are used in clinical practice; however, the optimal treatment algorithm remains unclear. The aim of this study was to evaluate outcomes of our level 1 trauma center protocol and to compare characteristics and outcomes between patients treated with pelvic external fixation (EF), transcatheter arterial embolization (TAE), or a combination of both (EF+TAE).
Materials And Methods:
A retrospective observational study including patients with hemodynamically unstable pelvic fractures presenting at our institution between January 2011 and December 2024 was conducted. Demographics, trauma characteristics, treatment characteristics, and clinical outcomes were evaluated for the total study population and compared across the treatment groups (EF, TAE, and EF+TAE) using a univariate analysis. Statistical significance was defined as p < 0.05.
Results:
Out of 2921 patients presenting with pelvic fractures at our institution, seventy-nine patients were included in the final analysis. The mean age was 53.6 ± 20.7, fifty patients were male (63%) and mean Injury Severity Score (ISS) was 30.9 ± 11.7. Fifty patients (63%) were initially managed with external fixation, twelve patients (15%) received TAE without external fixation and seventeen patients (22%) received both. Patients undergoing TAE were significantly older than those treated with external fixation alone or combined external fixation and TAE (p < 0.01) and received more units of packed red blood cells (median 10.0 for TAE, 8.0 for EF+TAE and 2.0 for EF (p < 0.001)). Acetabular fracture involvement was present in 5 of 12 patients treated with TAE, representing a significantly higher proportion than in the other treatment groups (p = 0.01). The median time-to-embolization in the TAE group was 197.5 min, compared to 206.0 min in the EF + TAE group (p = 0.64). Overall, 1-year mortality rate was 22%. No significant differences in mortality rates were found across the treatment groups.
Conclusion:
Overall, 1-year mortality rate of patients presenting with hemodynamically unstable pelvic fractures was 22%, mainly caused by traumatic brain injury. Patients treated with angioembolization were older and presented more frequently with acetabular fractures. External fixation before TAE did not prolong time-to-embolization.

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:29
Venous Thrombosis III: Interprofessional Care