Related Experiment Video
Updated: Sep 18, 2026

Structured Motor Rehabilitation After Selective Nerve Transfers
Published on: August 15, 2019
[Clinical characteristics and classification of deep branch of ulnar nerve injury]
Yong Yang1, Antong Jin1, Ran Liu1
1Department of Hand Surgery, Beijing Jishuitan Hospital, Capital Medical University, Beijing, 100035, P. R. China.

Objective:
To investigate the clinical characteristics of deep branch of the ulnar nerve injuries at the wrist and hand and to summarize the classification criteria.
Methods:
A retrospective analysis was conducted on 12 patients with deep branch of the ulnar nerve injuries at the wrist and hand admitted between November 2016 and September 2025, including 7 males and 5 females with an average age of 42.2 years (range, 17-69 years). The duration of injury ranged from 0.3 to 4.0 months (mean, 1.85 months). Two point discrimination (2-PD) of the little finger was 12 (4, 15) mm. The muscle strength of little finger abduction was rated as grade 3 in 1 case, grade 4 - in 6 cases, and grade 5 in 5 cases. Pinch strength between the thumb and index finger was (2.88±0.49) kg. Wartenberg sign was positive in 10 cases and negative in 2 cases. The index-middle finger crossing test was positive and claw-hand deformity was present in all patients. Ten patients underwent surgical treatment, whereas 2 patients received conservative treatment.
Results:
Based on the anatomical characteristics of the deep branch of the ulnar nerve, clinical manifestations, and intraoperative exploration findings, injuries to the deep branch of the ulnar nerve at the wrist and hand were classified into three types. Type Ⅰ injuries were located proximal to the pisohamate hiatus; type Ⅱ injuries were located between the pisohamate hiatus and a point 17 mm distal to the hook of the hamate; and type Ⅲ injuries were located distal to a point 17 mm distal to the hook of the hamate. Among the 12 patients, 7 were rated as type Ⅰ injuries, 3 as type Ⅱ injuries, and 2 as type Ⅲ injuries. All patients were followed up 6-108 months after treatment (median, 15.5 months). At last follow-up, 2-PD of the little finger improved to 6 (4, 6) mm; the muscle strength of little finger abduction improved to grade 5 - in 3 patients and grade 5 in 9 patients; and pinch strength between the thumb and index finger increased to (6.53±1.12) kg. All differences between pre- and post-treatment were significant ( P<0.05). Wartenberg sign, the index-middle finger crossing test, and claw-hand deformity were all negative. The all outcome indicators in the 7 patients with type Ⅰ injuries significantly improved when compared with those before treatment ( P<0.05).
Conclusion:
Based on the clinical characteristics and injury location, injuries to the deep branch of the ulnar nerve at the wrist and hand can be classified into three types. The pisohamate hiatus and the point 17 mm distal to the hook of the hamate on the palmar aspect are key anatomical landmarks for this classification. This classification system may facilitate accurate localization of deep ulnar nerve branch injuries and provide guidance for surgical planning.
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:12
Arteries of the Upper Limbs
 01:15
Bones of the Upper Limb: Ulna
 01:17
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
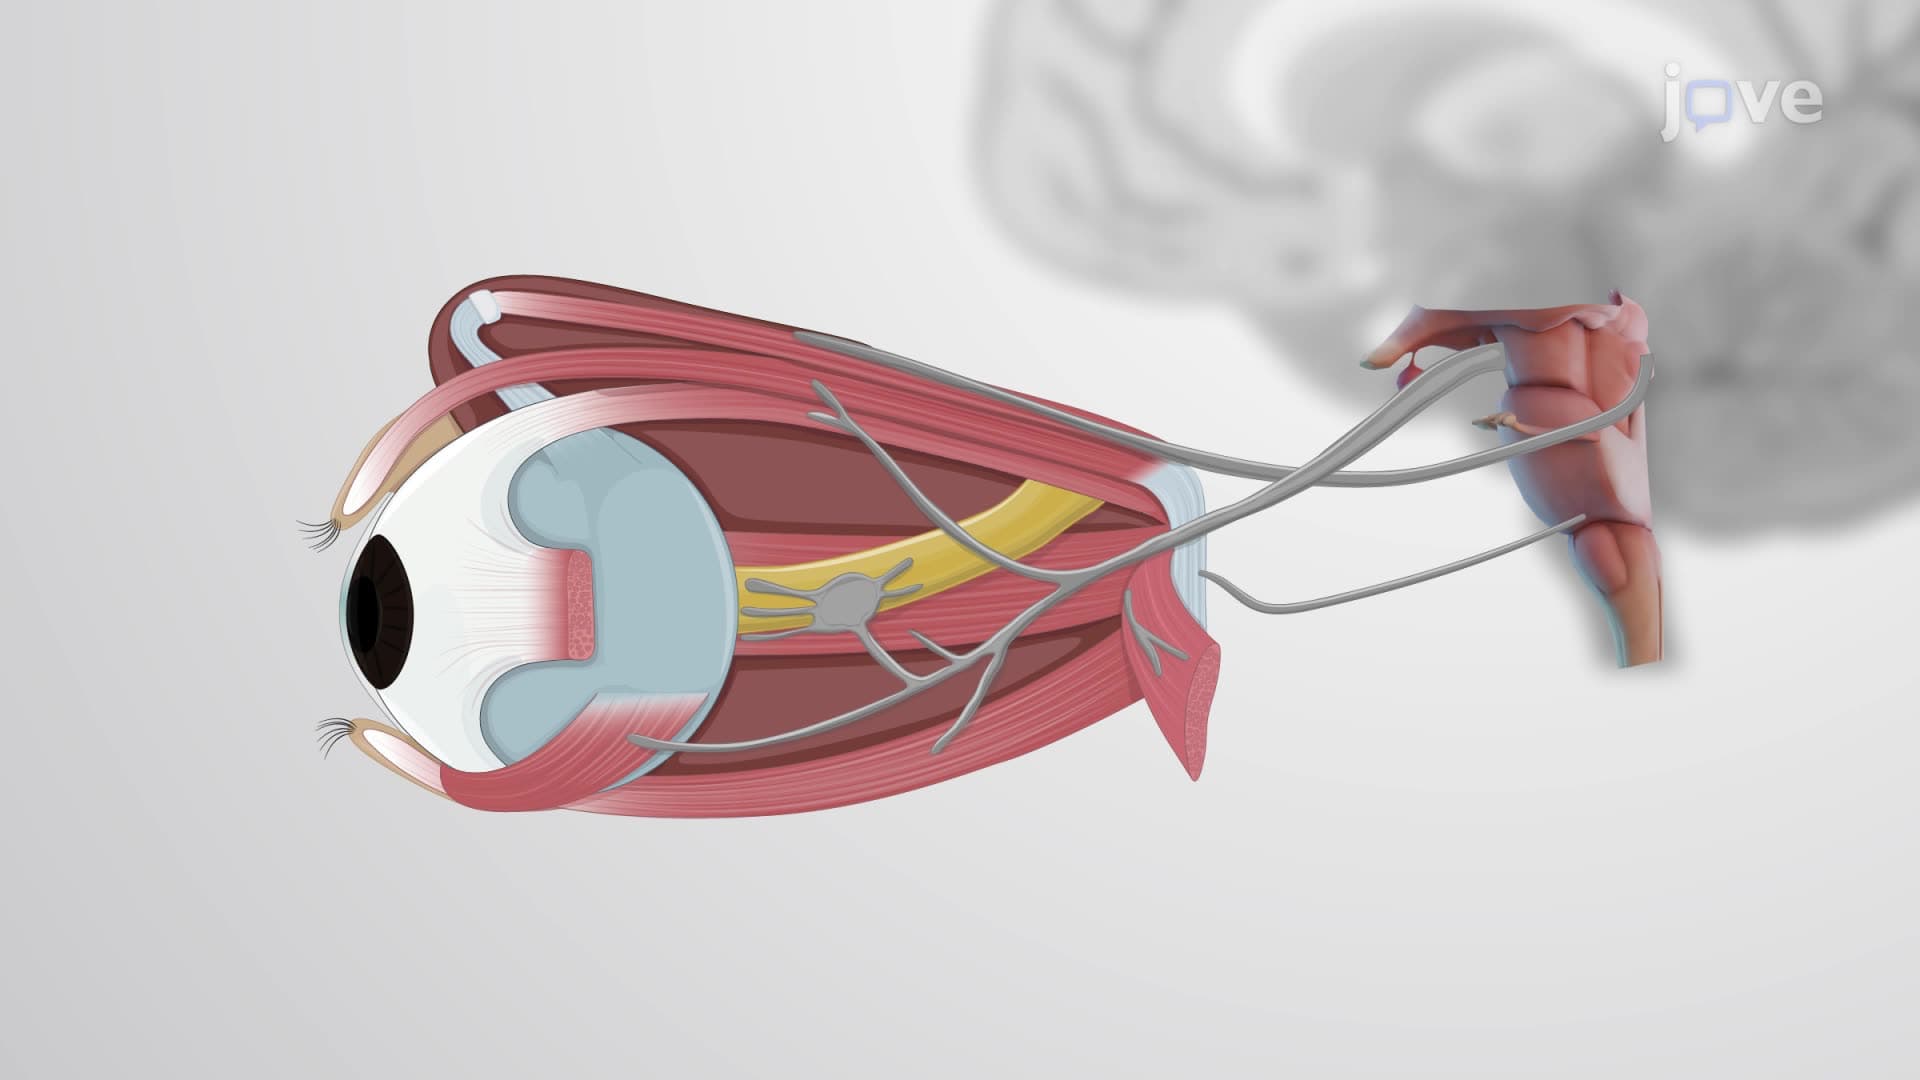 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...