Related Experiment Videos
Neutrophil-Dominant Inflammatory Responses and Inflammation-Coagulation Burden After Extremity Acute Compartment
Zihang Zhao1,2, Ruoyu Wang1,2, Liujie Zheng1,2
1Department of Orthopaedic Surgery, The Third Hospital of Hebei Medical University, Shijiazhuang, Hebei, People's Republic of China.

Background:
Extremity acute compartment syndrome (ACS) is a pressure-related surgical emergency accompanied by ischemic muscle injury. Whether routinely available inflammatory and coagulation markers characterize outcome-relevant host-response patterns remains unclear.
Methods:
We retrospectively analyzed 852 ACS-related patients, hospitalizations, or critical-care stays across three cohorts. The primary analysis included 227 patients with traumatic extremity ACS and examined early baseline inflammatory and coagulation profiles in relation to limb-specific adverse outcomes. Local inflammatory phenotype and post-baseline trajectory analyses were exploratory. Medical Information Mart for Intensive Care IV (MIMIC-IV; n=415) and eICU Collaborative Research Database (eICU; n=210) served as supportive critical-care cohorts for systemic outcomes and were not used for external validation of local limb-specific findings.
Results:
In the local cohort, muscle necrosis occurred in 85 patients (37.4%), amputation or muscle necrosis in 87 (38.3%), infection in 35 (15.4%), thrombosis in 29 (12.8%), and any adverse outcome in 109 (48.0%). Higher neutrophil and white blood cell counts were associated with any adverse outcome, muscle necrosis, and amputation or muscle necrosis. These associations remained directionally consistent after additional consideration of American Society of Anesthesiologists physical status, injury-to-hospital time, and, among decompressed patients, injury-to-decompression time. A principal-component-derived inflammation-coagulation axis was associated with adverse limb and thrombotic outcomes. Exploratory analyses identified a neutrophil-dominant inflammatory phenotype and heterogeneous post-baseline trajectories. Supportive MIMIC-IV and eICU analyses showed associations between systemic inflammatory burden and selected systemic outcomes.
Conclusion:
In the primary local cohort, extremity ACS was accompanied by measurable inflammatory host-response patterns associated with adverse outcomes. Phenotype and trajectory findings were exploratory. Public critical-care cohorts provided supportive systemic-outcome context but did not externally validate the local limb-specific findings. Prospective studies with standardized sampling and clinical covariate ascertainment are needed before these markers can be considered for clinical risk assessment or decision-making.
Related Concept Videos
 01:25
Acute Inflammation III: Local and Systemic Effects
 01:38
Inflammation
 01:12
Chronic Inflammation: Introduction
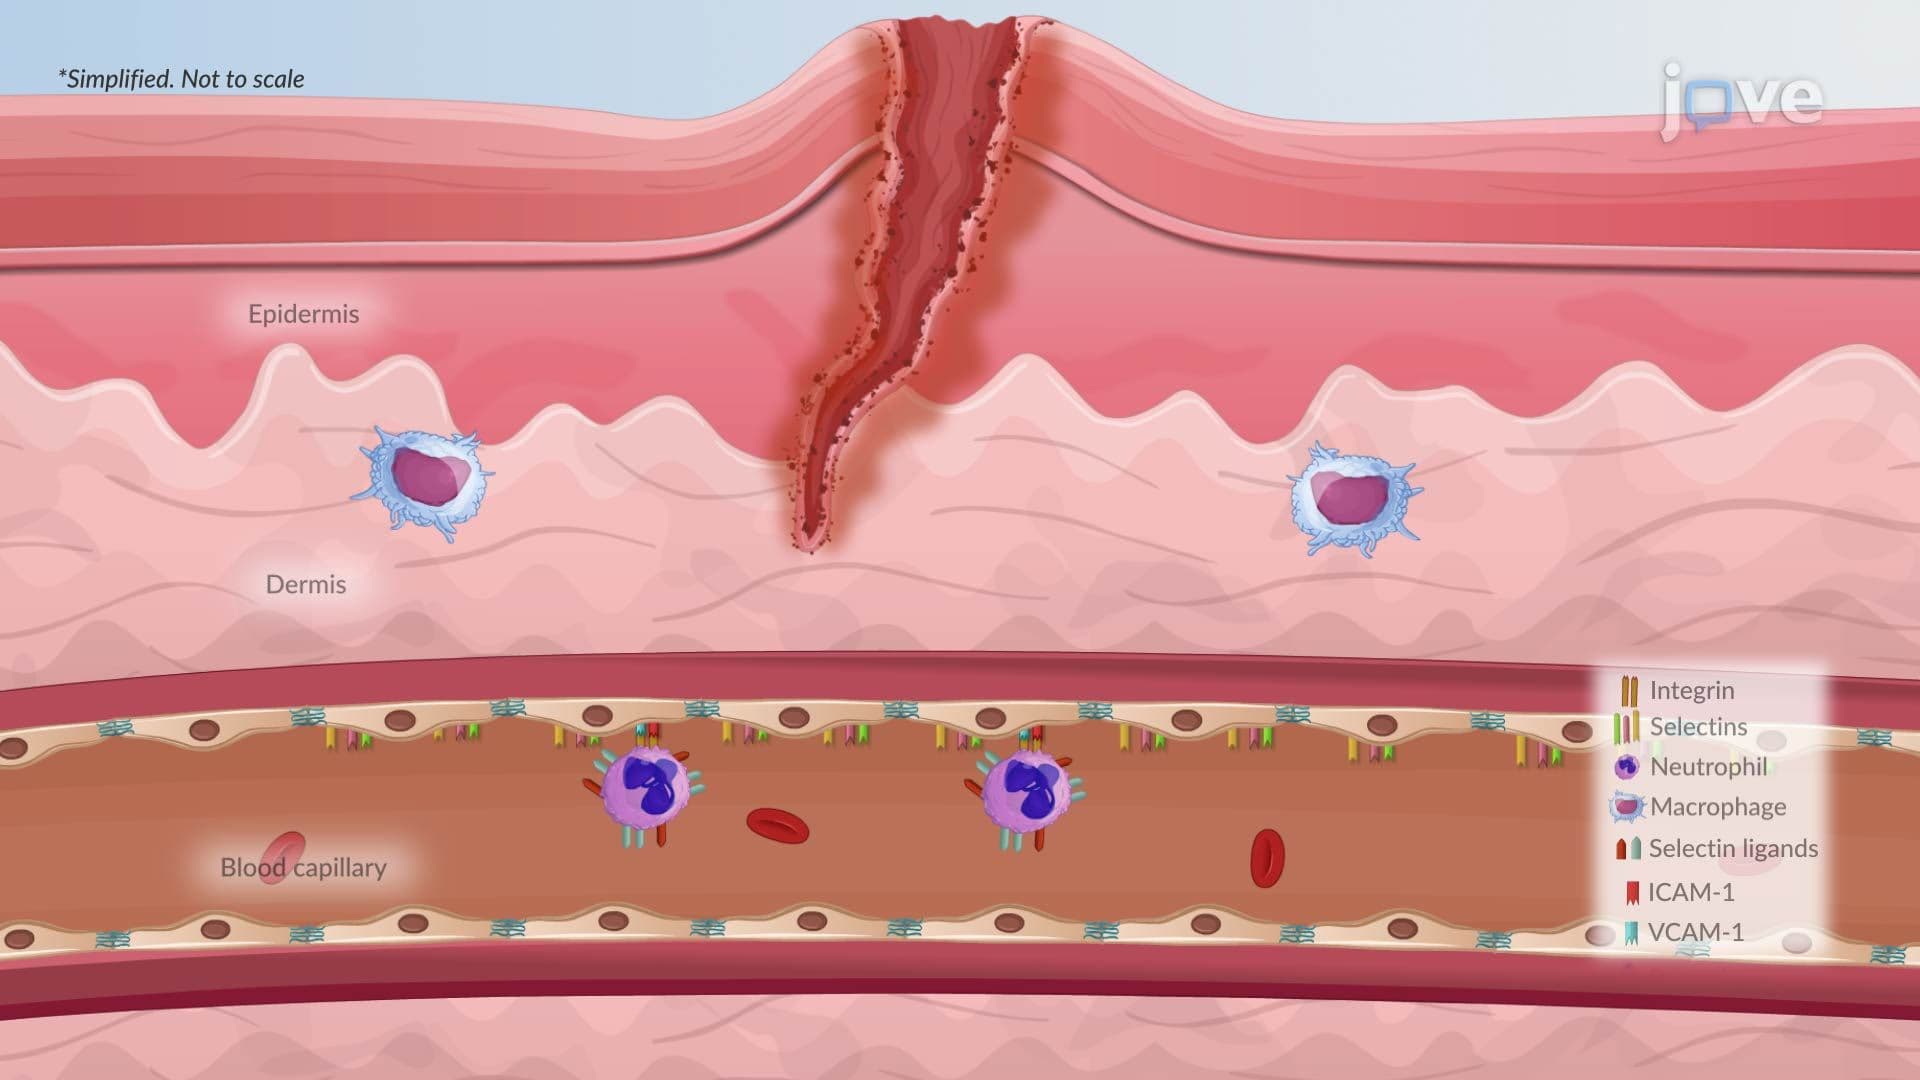 01:26
Acute Inflammation II: Cellular Phase
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...