Related Experiment Video
Updated: Sep 19, 2026
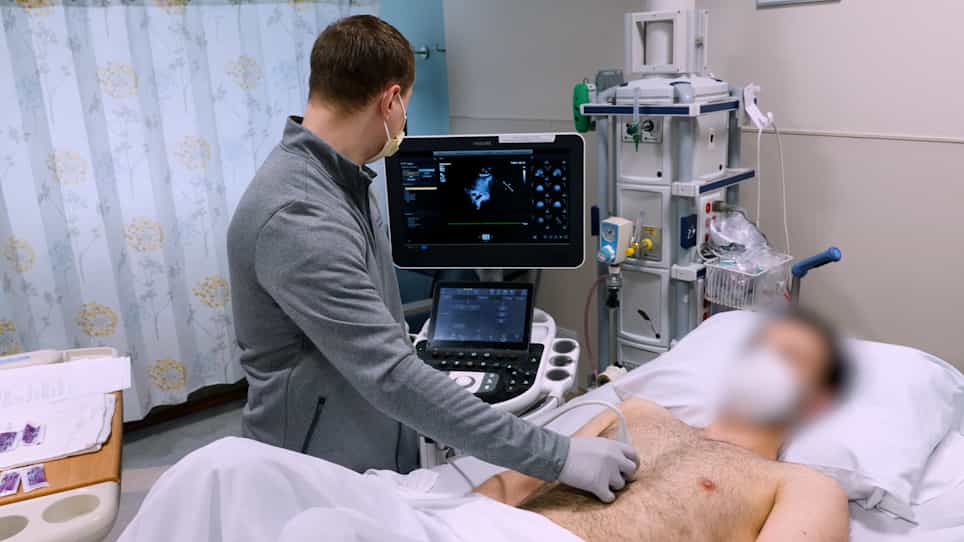

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Modern Management of Inferior Vena Caval Injuries: What You Need to Know

Abstract:
Traumatic inferior vena cava (IVC) injuries are uncommon but remain among the most lethal injuries in abdominal vascular trauma, with mortality driven by shock, injury location, associated injuries, and loss of retroperitoneal tamponade. This review summarizes a physiology-first, segment-specific approach to adult traumatic IVC injuries. Initial management should prioritize the patient's hemodynamic status over radiologic diagnosis alone. Patients with persistent or recurrent hypotension, continued transfusion requirements, acidosis, or signs of ongoing intra-abdominal hemorrhage require immediate hemorrhage control with damage-control resuscitation. In stable or stabilized patients, contrast-enhanced computed tomography should determine whether bleeding is active or contained, whether hemorrhage is intraperitoneal or retroperitoneal, which IVC segment is involved, and whether associated injuries mandate laparotomy. Operative management relies on exposure, temporary control, definition of the venous defect, and the simplest durable repair compatible with physiology. Primary venorrhaphy is preferred when feasible, whereas ligation, patch repair, intraluminal balloon control, venovenous bypass, or staged damage-control strategies may be required in selected scenarios. Retrohepatic and suprahepatic injuries require early recognition, packing, and inflow control when right upper quadrant bleeding is present, and rapid mobilization of multidisciplinary resources if necessary. More recently, endovascular, hybrid, and nonoperative strategies have gained expanded roles but should be reserved for carefully selected stable or stabilized patients with suitable anatomy, contained bleeding, and in locations with immediate capability to convert to an open approach if physiology deteriorates. Postoperative care requires vigilance for recurrent bleeding, caval thrombosis, venous thromboembolism, renal or hepatic dysfunction, and complications related to ligation or reconstruction. Contemporary management of IVC injury is dynamic: physiology determines urgency, imaging defines anatomy in stable patients, and institutional capability determines the safest definitive strategy.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:22
Aneurysm IV: Nursing Management
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:26
Cardiac Catheterization IV: Nursing Management