Related Experiment Video
Updated: Sep 19, 2026
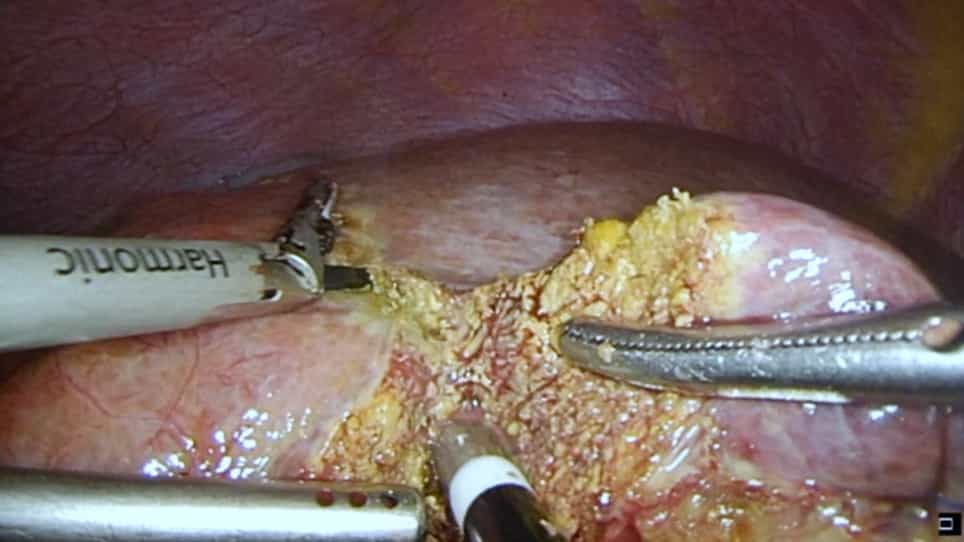

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Gastrointestinal bleeding in hepatocellular carcinoma under systemic therapy: Real-world incidence and clinical
Leonardo G Da Fonseca1, Lucas Takeshi Ikeoka1, Eduardo Kim Sampaio1
1Department of Oncology, Instituto do Câncer do Estado de São Paulo (ICESP), Faculdade de Medicina da Universidade de São Paulo (FMUSP), São Paulo, SP, Brazil.

Objective:
Gastrointestinal (GI) bleeding is a major complication in patients with advanced Hepatocellular Carcinoma (HCC), particularly among those with underlying portal hypertension. Although systemic therapy has improved survival outcomes, real-world data regarding the incidence, predictors, and clinical impact of GI bleeding remain limited. This study aimed to evaluate the incidence, risk factors, and prognostic implications of GI bleeding in patients with advanced HCC receiving sorafenib.
Methods:
This retrospective cohort study included 439 patients with advanced HCC between 2009 and 2025. Time-to-event analyses were performed from treatment initiation. The cumulative incidence of GI bleeding and bleeding-related mortality was estimated using competing-risk methods. Incidence rates were calculated per 100 Person-Years (PY), and adjusted incidence rate ratios were estimated using multivariable Poisson regression. Predictors of GI bleeding were further evaluated using multivariable logistic regression.
Results:
Baseline endoscopy was performed in 56% of patients, of whom 58% had evidence of portal hypertension. The incidence rate of GI bleeding was 5.6 per 100 PY (95% Confidence Interval [95% CI 4.6-6.8]), with cumulative incidence rates of 10.57% (95% CI 7.85-14.16) at 6-months and 23.06% (95% CI 18.60-28.38) at 12-months. Esophagogastric varices, splenomegaly, vascular invasion, and prior GI bleeding were independently associated with increased bleeding risk. Based on these predictors, a simple additive risk score ranging from 0 to 4 was developed and demonstrated progressive increases in predicted bleeding probability across risk categories, supporting its potential utility for clinical risk stratification. GI bleeding was associated with poor outcomes, with a median survival time of 11-days after the event and a bleeding-related mortality rate of 75.5%.
Conclusion:
GI bleeding is a frequent and highly lethal complication in patients with advanced HCC. These findings highlight the importance of risk assessment, endoscopic evaluation, and preventive strategies in this population.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...