Related Experiment Video
Updated: Sep 19, 2026
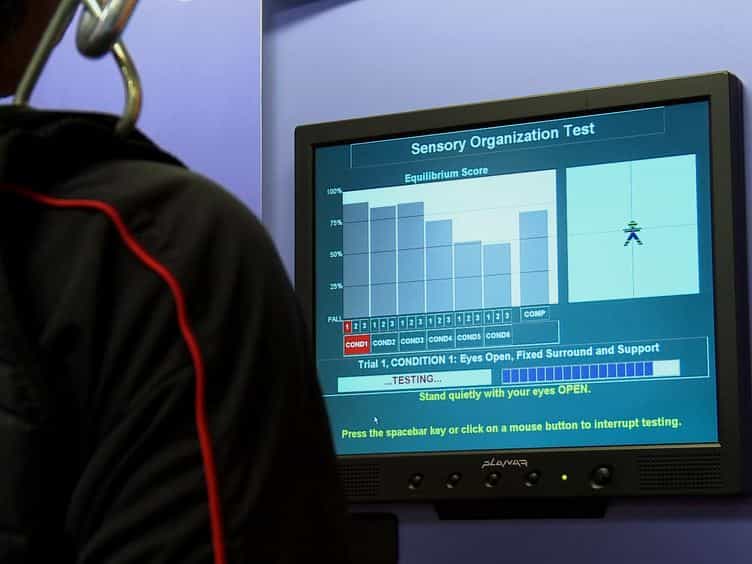

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Cost Effectiveness of Supervised Exercise Programmes for Intermittent Claudication: An Economic Evaluation Based on
Carlos Chivardi1, Alfredo Palacios1, Chao Huang2
1Centre for Health Economics, University of York, York, UK.

Objective:
Intermittent claudication significantly impairs walking ability and quality of life. Although clinical guidelines recommend supervised exercise programmes (SEPs) as first line treatment, a lack of consensus on the optimal frequency, intensity, time, and type of exercise has delayed implementation. This model based, cost effectiveness analysis study aimed to evaluate the cost effectiveness of alternative SEPs to determine their value for money, based on the MAXIMISE study.
Methods:
A de novo model compared SEP configurations varying in their components against unsupervised exercise and each other. The model linked effects of exercise on maximum walking distance to quality adjusted life years (QALYs) and costs (2023 price year in GBP, £), from the healthcare payer perspective. The cost effective intervention was identified based on the incremental cost effectiveness ratio (ICER) of each exercise intervention (supervised or unsupervised) compared with the next potentially cost effective intervention. Results robustness was explored in scenario analyses.
Results:
SEPs seemed cost effective compared with unsupervised exercise for most prescriptions. A prescription of 30 - 44 minutes per session (with rest and progression) of high intensity interval cycling thrice weekly for 12 weeks appeared to be cost effective (49% probability at £20 000/QALY; ICER: £5 672/QALY [€6 628/QALY; exchange rate of €1 = £0.85585]). Restricting the analysis to SEPs judged to be of higher quality and/or more clinically relevant suggested that the cost effective SEP would consist of sessions of less than 30 minutes (with rest and without progression) of intermittent walking until mild to moderate pain, thrice weekly for 12 weeks (21% probability at £20 000/QALY; ICER: £2 183/QALY [€2 551/QALY]). Results were only sensitive to how exercise effects were synthesised.
Conclusion:
Most SEPs emerged as cost effective compared with unsupervised exercise. Cost effectiveness differences between the clinically identified optimal exercise prescription and the prescription offering the most value for money in the National Health Service seemed to be driven by costs of delivering a prescription that is less resource intensive.
