Related Experiment Video
Updated: Sep 19, 2026


Development of a Neonatal Piglet Acute Lung Injury Model Recreating the Early Environment of Preterm Infant Lungs
Published on: October 31, 2025
Temporal changes in bronchopulmonary dysplasia severity distribution associated with evolving respiratory practices
Kamal Ali1,2,3, Talal Aljarbou2,3, Saleh Algarni2,4
1College of Medicine, King Saud bin Abdulaziz University for Health Sciences, Riyadh, Saudi Arabia alika@mngha.med.sa.

Objective:
To evaluate temporal changes in respiratory management practices and bronchopulmonary dysplasia (BPD) severity in infants born before 32 weeks of gestation over a 9-year period.
Design:
Retrospective cohort study.
Setting:
Tertiary neonatal intensive care unit.
Patients:
Infants born before 32 weeks of gestation and admitted between January 2017 and December 2025.
Exposure:
Birth during one of three predefined clinical eras: pre-COVID (2017-2019), COVID (2020-2022) and post-COVID following relocation to an expanded neonatal intensive care unit (2023-2025).
Main Outcome Measures:
BPD severity at 36 weeks of postmenstrual age (PMA), mortality before hospital discharge, and the composite outcome of death before hospital discharge or BPD at 36 weeks of PMA. Associations between study era and respiratory outcomes were evaluated using multivariate logistic regression.
Results:
A total of 1259 infants were included. Respiratory management practices changed across study eras. High-flow nasal cannula exposure increased from 43.7% in era 1 to 70.6% in era 3 (p<0.001), while duration of non-invasive respiratory support increased from 4 to 11 days (p<0.001). Less invasive surfactant administration was introduced predominantly during era 3, and postnatal corticosteroid exposure increased from 16.5% to 36.4% (p<0.001). BPD incidence increased across eras (25.2%, 30.9% and 37.7%; p<0.001), primarily driven by grade 2 disease, whereas grade 3 BPD and mortality remained stable. Compared with era 1, infants in era 3 had higher adjusted odds of moderate-to-severe BPD (adjusted OR 3.29, 95% CI 2.15 to 5.05; p<0.001) and the composite outcome of death before hospital discharge or BPD at 36 weeks of PMA (adjusted OR 2.08, 95% CI 1.47 to 2.94; p<0.001).
Conclusions:
Respiratory management practices evolved over time and were accompanied by increased moderate BPD without corresponding increases in severe BPD or mortality. These findings suggest that evolving respiratory support practices and contemporary BPD definitions may influence the observed distribution of BPD severity.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:17
Pulmonary Cycle: Exhalation
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
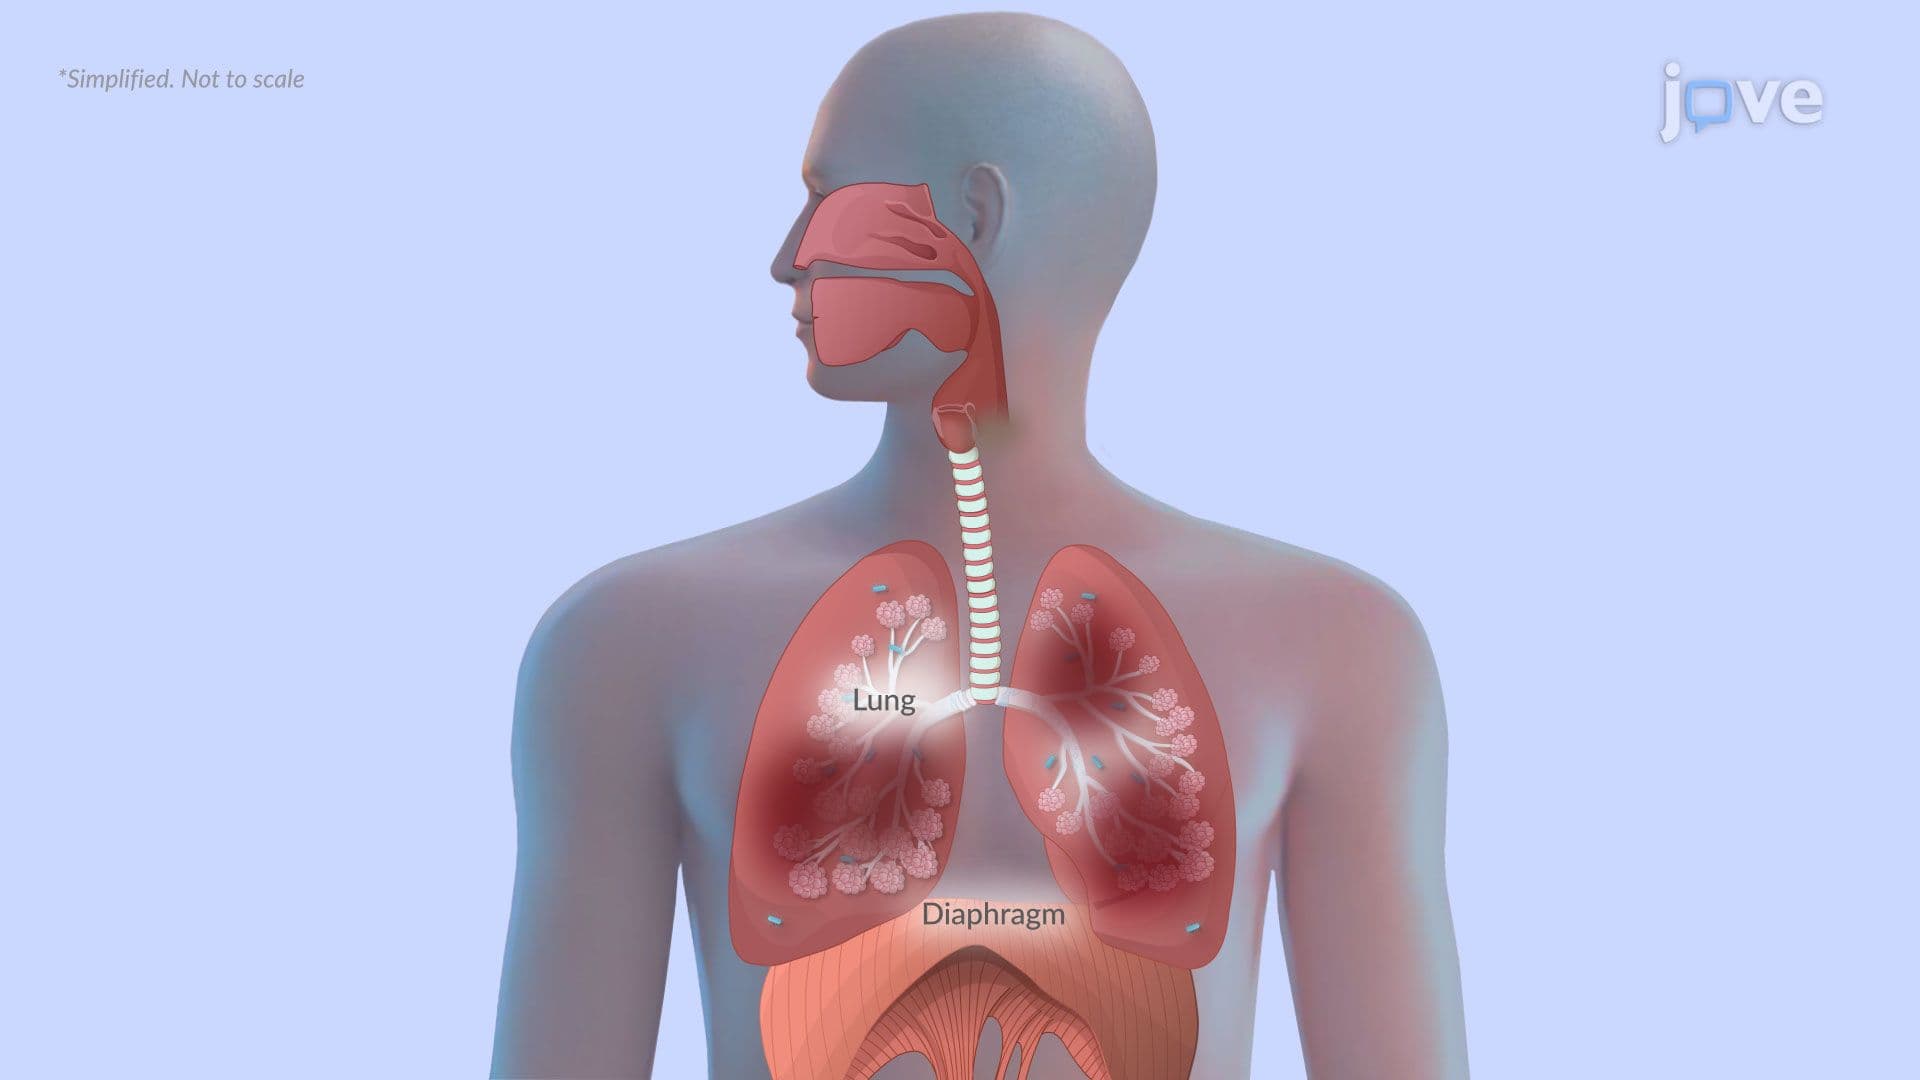 01:23
Chronic Obstructive Pulmonary Disease I: Introduction