Related Experiment Video
Updated: Sep 19, 2026


Microsurgical Skills of Establishing Permanent Jugular Vein Cannulation in Rats for Serial Blood Sampling of Orally Administered Drug
Published on: December 14, 2021
Clinical Pharmacokinetics and Disposition of Imrecoxib
Shengnan Zhao1,2, Charlie Li1, Marlon C Mallillin1,3
1Faculty of Pharmacy and Pharmaceutical Sciences, University of Alberta, Edmonton, AB, T6G 2H7, Canada.

Abstract:
Imrecoxib is a cyclooxygenase-2-preferential nonsteroidal anti-inflammatory drug approved in China for the symptomatic treatment of osteoarthritis and is currently marketed only in China. This narrative review evaluates its clinical pharmacokinetics, including disposition, special populations, drug-drug interactions, and evidence for dose adjustment. After oral administration, imrecoxib reaches peak plasma concentrations within 2-3 h, and food increases systemic exposure. It is highly protein bound and extensively metabolised sequentially from imrecoxib (M0) to 4'-hydroxymethylimrecoxib (M1), then to the aldehyde intermediate 4'-formylimrecoxib (M-CHO), and finally to 4'-carboxyimrecoxib (M2). Cytochrome P450 3A4 (CYP3A4) and cytochrome P450 2D6 (CYP2D6) mediate M1 formation, while M2 formation also involves aldehyde oxidase. Both M1 and M2 are pharmacologically active, and M2 is the predominant circulating metabolite. Unchanged urinary excretion is negligible, whereas M1, M2, and their conjugates contribute to renal elimination. Severe renal impairment markedly increases M2 exposure (area under the plasma concentration-time curve from time zero to the last measurable concentration [AUC0-t] approximately 3.7-fold that in subjects with normal renal function) and reduces its apparent clearance to approximately 37% of that in subjects with normal renal function, although the clinical exposure-response consequences and the proposed reduced-dose regimens remain unvalidated. Moderate hepatic impairment markedly increases imrecoxib and M1 exposure (area under the plasma concentration-time curve from time zero to infinity [AUC0-∞] approximately 10.8-fold and 3.2-fold that in matched healthy subjects, respectively), while M2 AUC0-∞ increases by approximately 35%. In a small single-dose study, exposure to imrecoxib, M1, and M2 was numerically higher in older subjects, but the differences were not statistically significant and pharmacokinetic equivalence was not demonstrated. Currently, no definitive dose-adjustment recommendations have been established, although dose reduction may be considered in severe renal impairment; routine age-based adjustment is not supported, and the optimal regimen in hepatic impairment remains undefined. Multiple-dose imrecoxib did not meaningfully alter warfarin pharmacokinetics or anticoagulant response, whereas fluconazole increased imrecoxib maximum plasma concentration (Cₘₐₓ) and AUC0-t by approximately 88% and 72%, respectively, without comparable increases in M1 or M2 exposure. Current evidence is limited by small, mainly single-dose studies, predominantly Chinese populations, and the absence of validated exposure-response relationships integrating imrecoxib, M1, and M2. More robust studies are needed to define dose adjustment in organ impairment.
Related Concept Videos
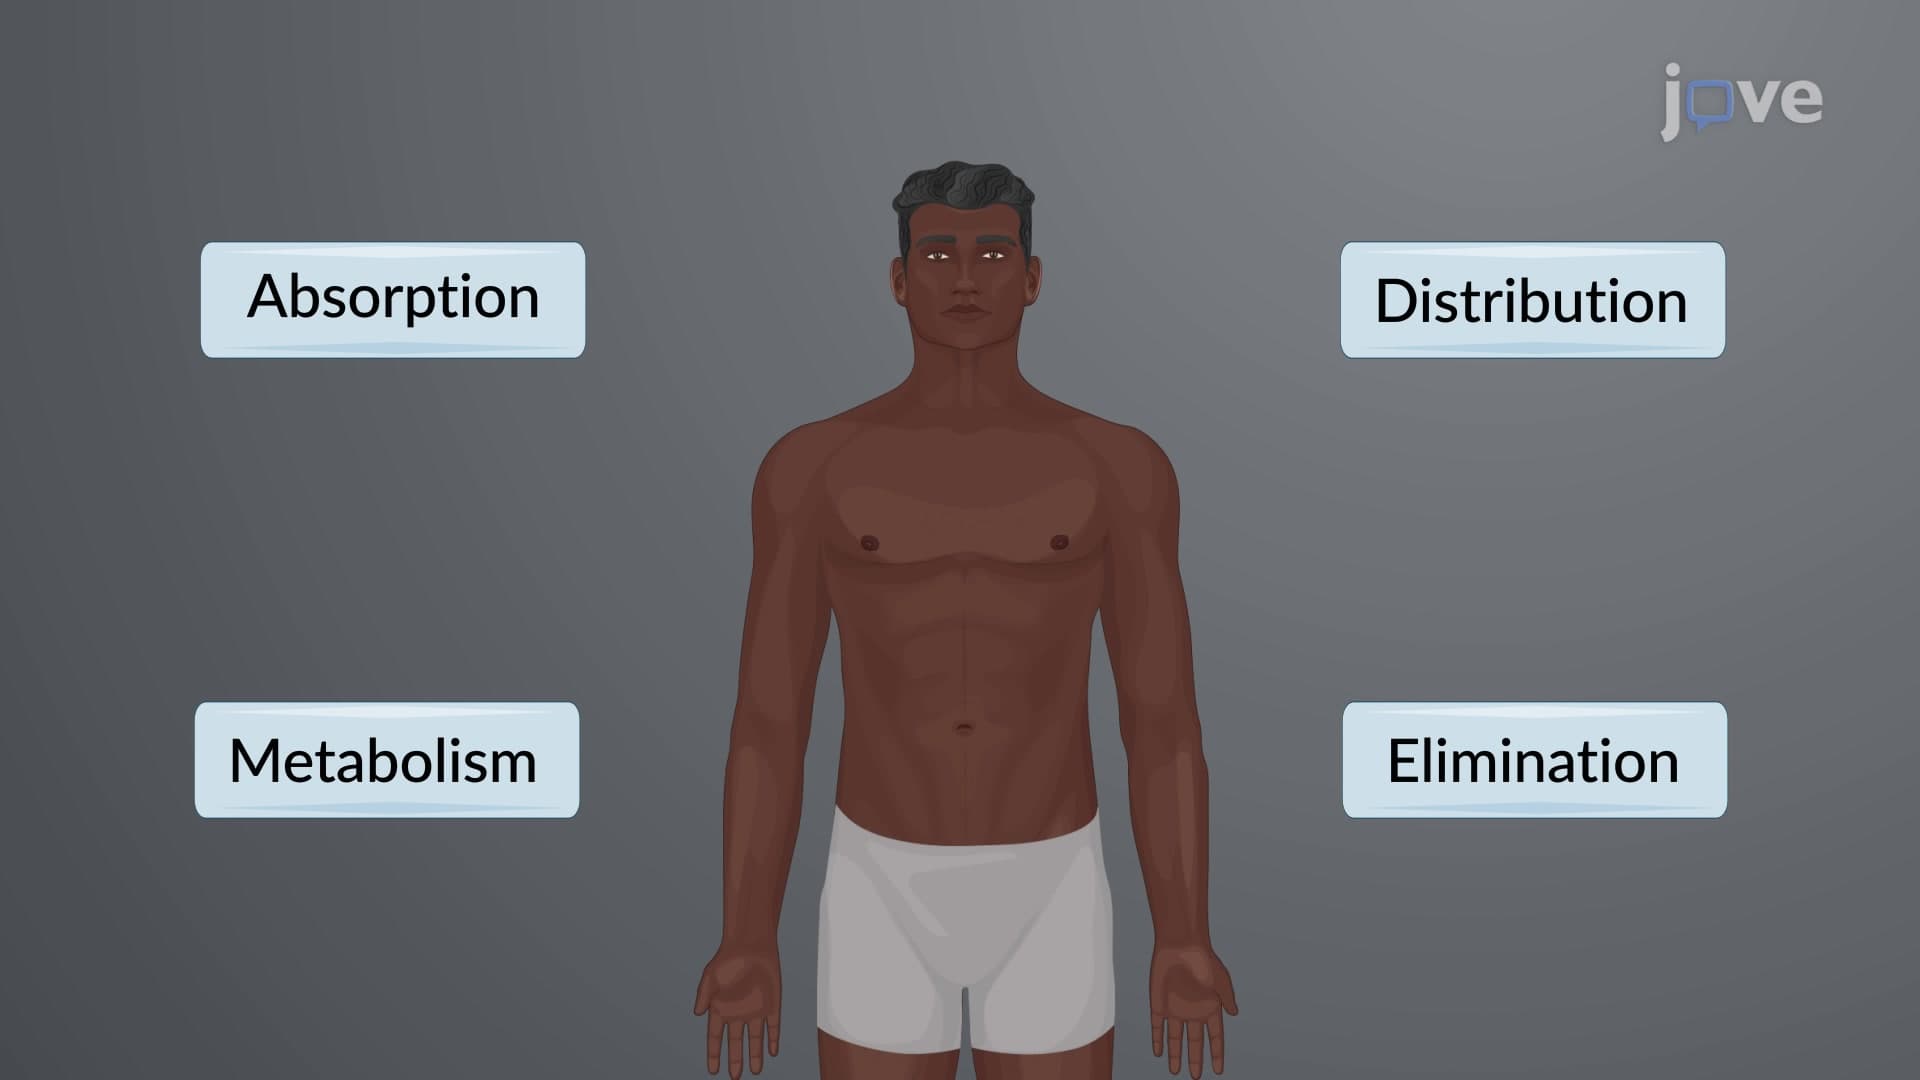 01:10
Pharmacokinetics: Overview
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
 01:20
Factors Affecting Dissolution: Drug Permeability, Stability and Stereochemistry
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:30
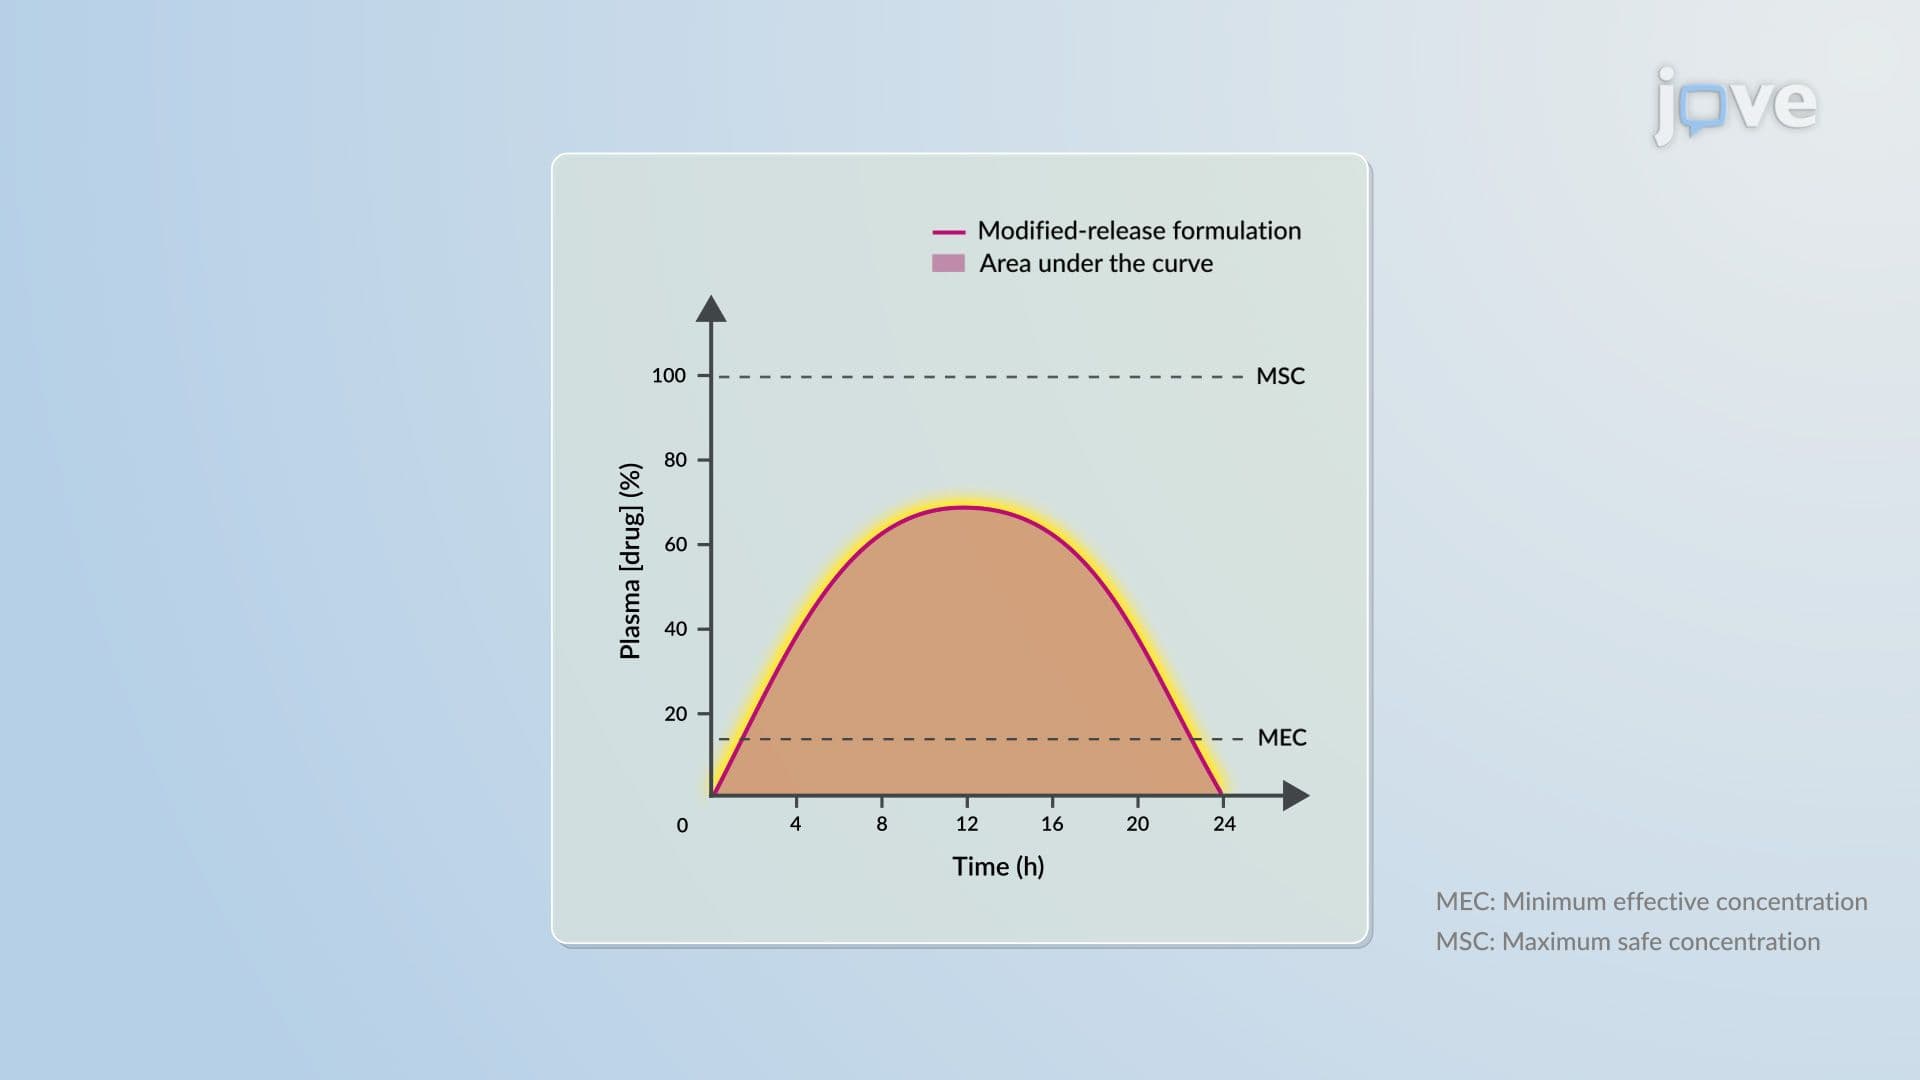
Modified-Release Drug Delivery Systems: Bioavailability
 01:27
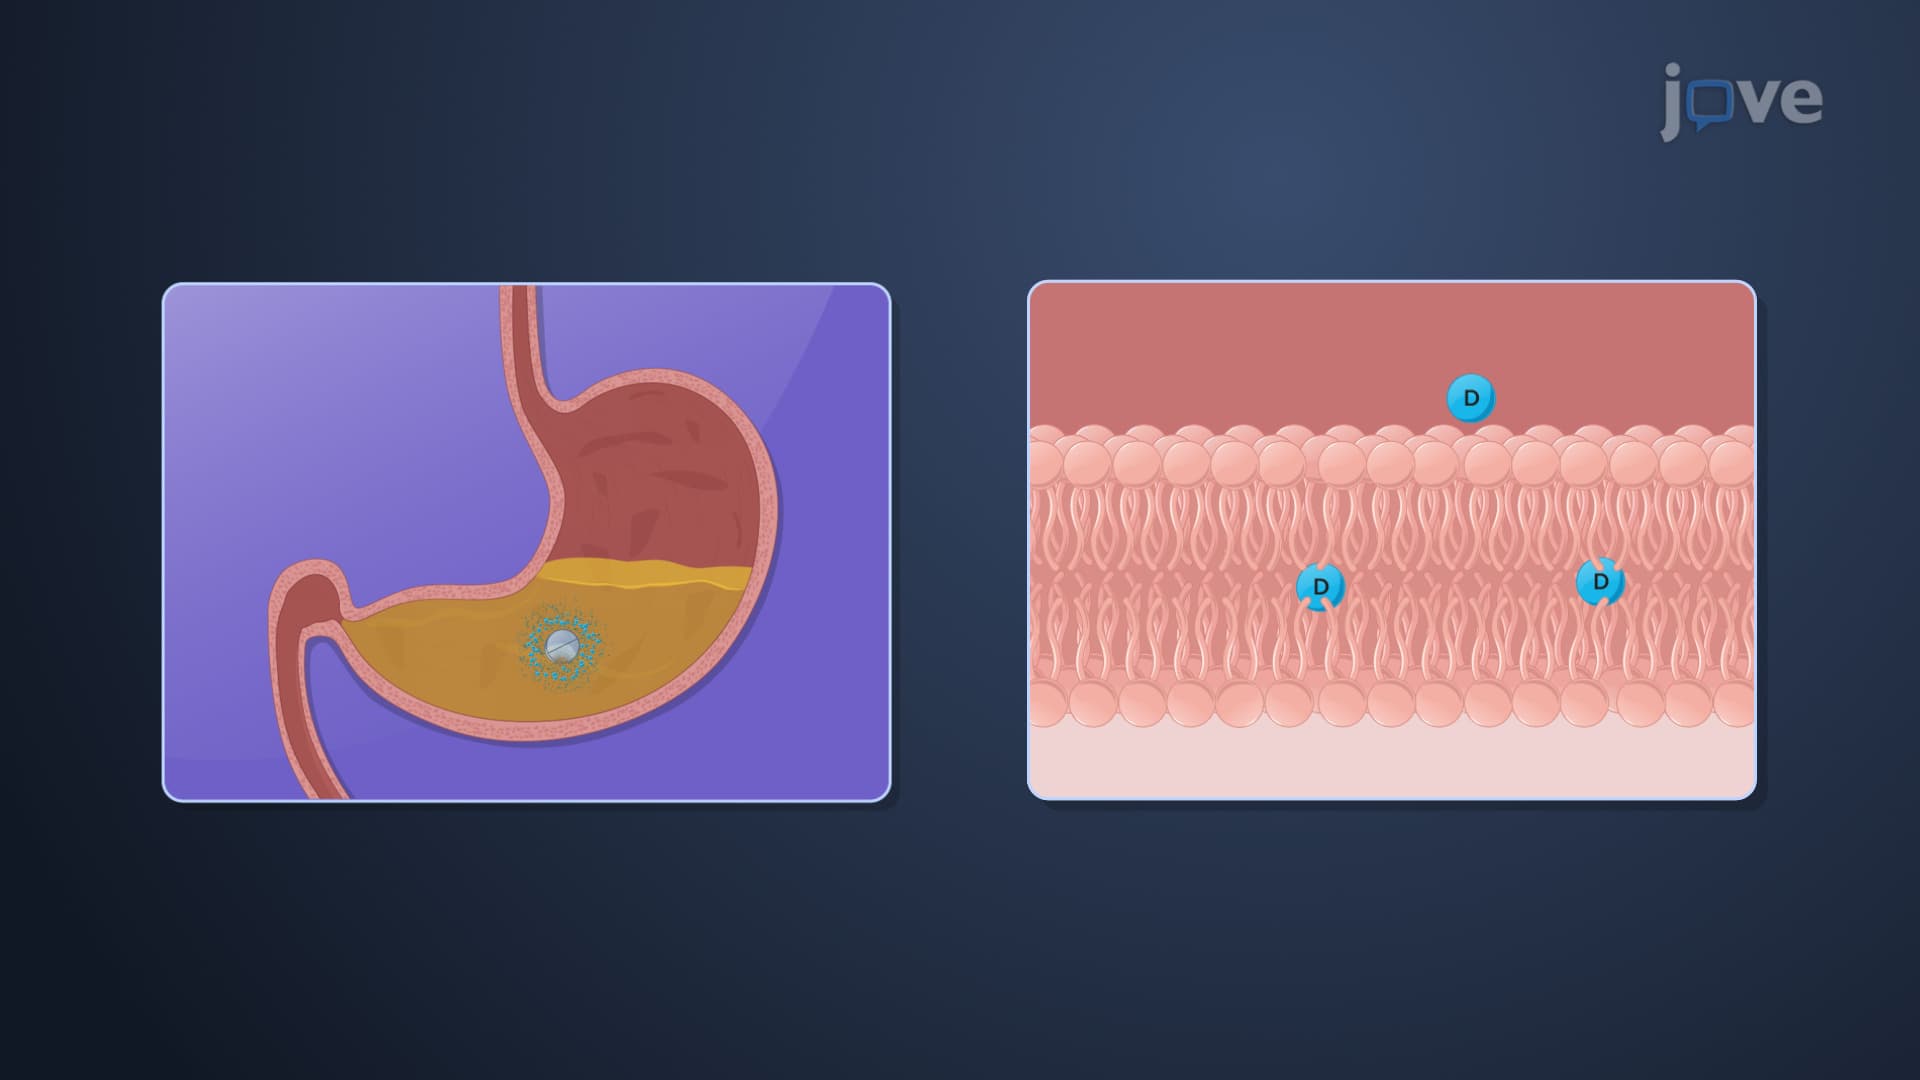
Factors Influencing Drug Absorption: Drug Dissolution