Related Experiment Video
Updated: Sep 19, 2026


Production and Measurement of Organic Particulate Matter in a Flow Tube Reactor
Published on: December 15, 2018
From particle count to residence time: a kinetic framework for atherogenic risk
1Diplomatura en Medicina del Estilo de Vida, Physician, Chos Malal, Universidad Nacional del Comahue, Neuquén, Argentina.

Abstract:
Two sequential advances have narrowed the gap between lipid measurement and atherogenic mechanism. Mendelian randomization established that coronary risk tracks apolipoprotein B (ApoB) particle count, not cholesterol content: when natural discordance exists between low-density lipoprotein cholesterol (LDL-C) and ApoB, risk follows ApoB reduction independently of LDL-C. The 2026 ACC/AHA dyslipidemia guideline formalized this advance, placing ApoB above LDL-C as a risk measure in discordance contexts. That particle-count model fails systematically before a set of clinical paradoxes sharing a common feature: identical ApoB concentrations generating radically different cardiovascular risk depending on metabolic and endothelial context. Hemodialysis patients carry ten- to twenty-fold excess cardiovascular risk with normal ApoB, and statins do not reduce events in dialysis despite reducing LDL-C. PCSK9 loss-of-function (LOF) variants produce an 88% coronary risk reduction at LDL-C of 100 mg/dL, a magnitude approximately three times what the logarithmic dose-response predicts. Patients with systemic lupus erythematosus and rheumatoid arthritis develop accelerated atherosclerosis with normal lipids. Male endurance athletes with favorable lipid profiles show coronary artery calcium scores equivalent to sedentary controls with traditional risk factors. I propose that atherogenic risk is a function of the plasma residence time (RT) of ApoB-containing particles, determined by two separable kinetic components: FCR_est (structural, genotype-dependent fractional catabolic rate, d-1) and FCR_cin (functional, kmod-dependent clearance efficiency, dimensionless 0-1), modulated by an endothelial permeability function proxied by the urinary albumin-to-creatinine ratio (UACR). The framework is expressed as: Atherogenic Load = . The model generates a four-group functional classification with qualitatively distinct therapeutic implications: the rate-limiting step is the LDLR receptor in Group 1a [familial hypercholesterolemia, PCSK9 gain-of-function (GOF) variants], the ApoB-100 ligand in Group 2 (metabolic syndrome, uremia, autoimmunity), and the endothelial gate in Group 3. Treating all groups with the same LDL-C reduction strategy is a category error with quantifiable consequences. The five core predictions of the framework are falsifiable with currently available stable-isotope kinetic and anion-exchange chromatography technology.
Related Concept Videos
 01:05
Noncompartmental Analysis: Mean Residence Time
After the administration of a drug through intravenous bolus injection, the drug molecules are distributed throughout the body and remain there for varying periods. The MRT represents the average time these drug molecules stay in the...
 01:30
Atherosclerosis I: Introduction
 01:22
Mean free path and Mean free time
 01:20
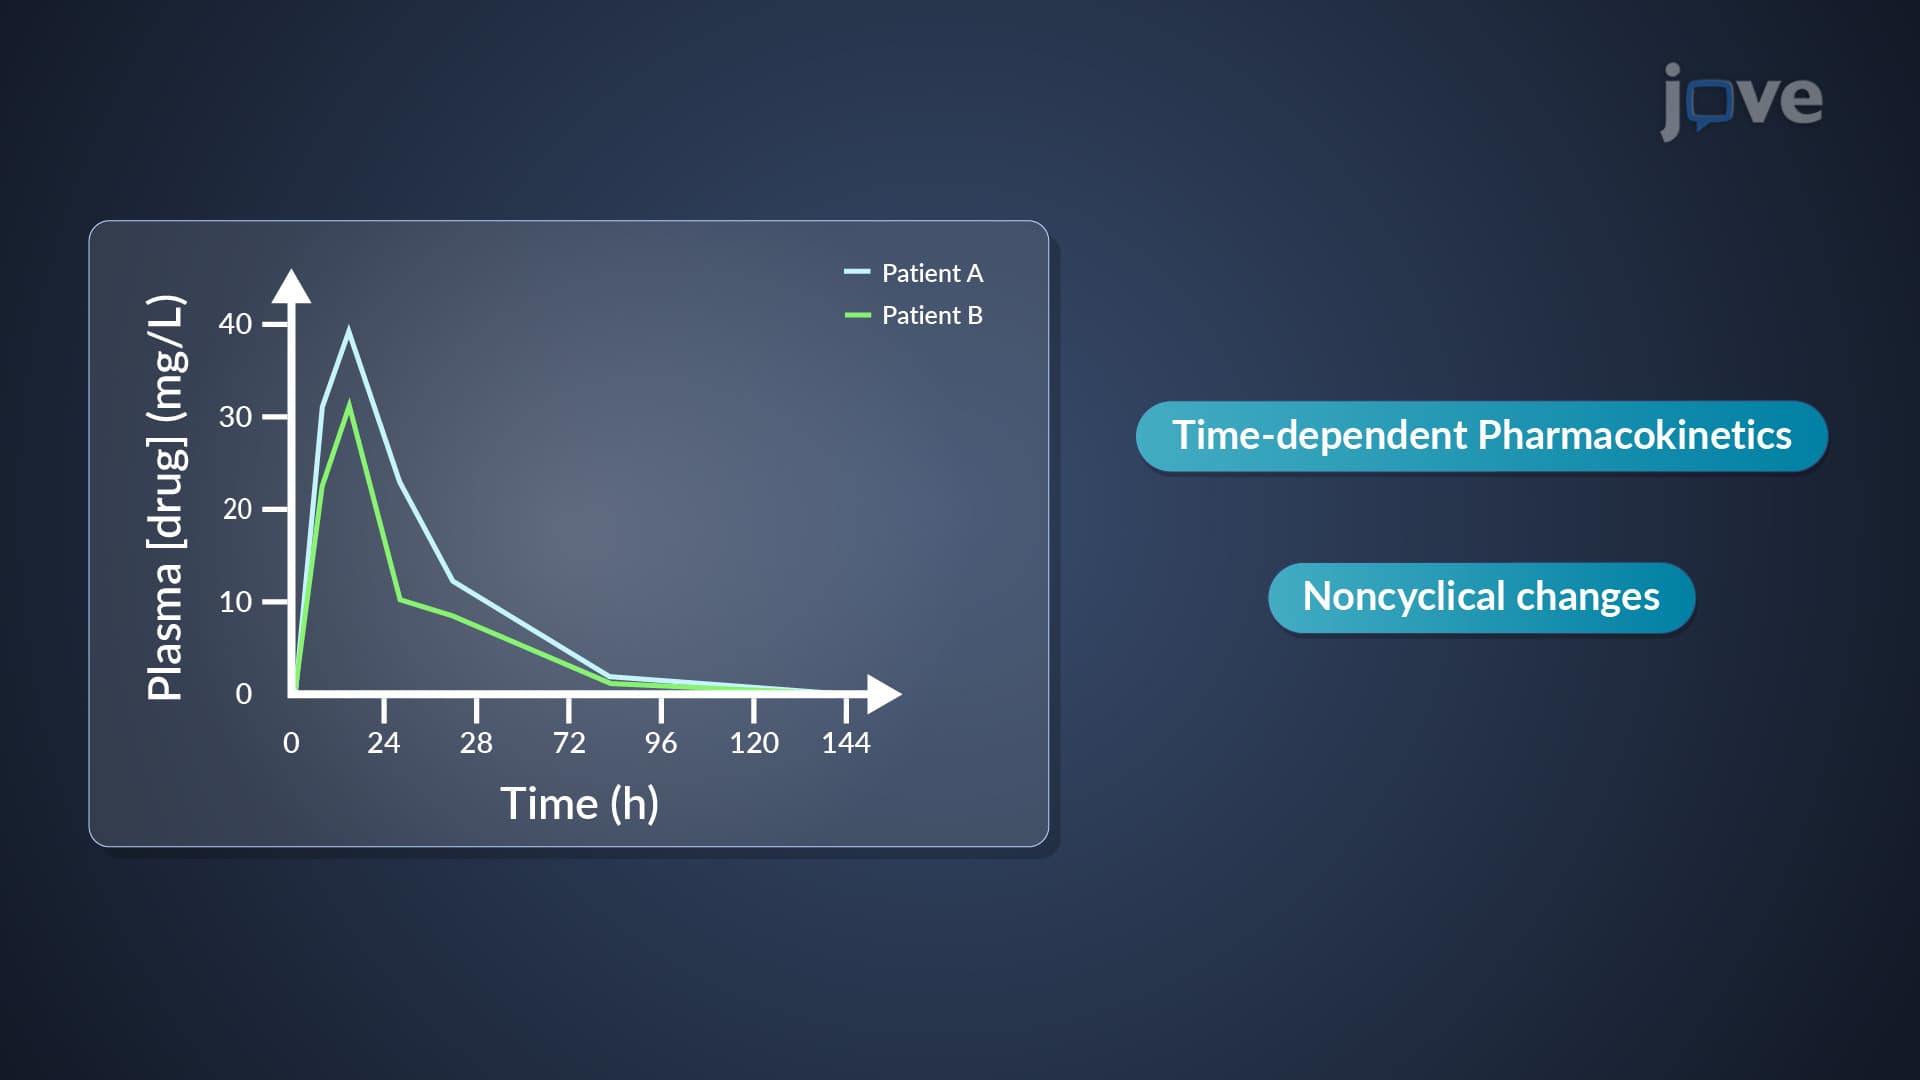
Chronopharmacokinetics: Time-Dependent Pharmacokinetics
Time-dependent pharmacokinetics refers to non-cyclical changes in drug rate processes over a period of time. It can lead to nonlinear pharmacokinetics, where the relationship between drug concentration and time is not proportional. Non-cyclical...
 01:20
Pharmacokinetic Models: Overview
There are three primary types of models: empirical, compartment, and physiological. Empirical models, with minimal assumptions,...
 00:56
Noncompartmental Analysis: Statistical Moment Theory