Related Experiment Video
Updated: Sep 19, 2026


Galleria mellonella as an Antimicrobial Screening Model
Published on: October 11, 2024
Weight-based polymyxin B dosing for mortality and nephrotoxicity: an exploratory dose-response study
Sung-Ching Pan1, Ming-Tao Tsai2, Jann-Tay Wang1
1Department of Internal Medicine, National Taiwan University Hospital, Taipei, Taiwan.

Objectives:
The optimal weight-based maintenance dose of polymyxin B is not established. We evaluated dose-response relationships for 28-day mortality and nephrotoxicity and explored a dose threshold.
Methods:
In this single-centre retrospective cohort, hospitalized adults received a first intravenous polymyxin B course (June 2025 to February 2026); the maintenance dose (mg/kg/day) was the exposure. Main outcomes were 28-day mortality and nephrotoxicity, defined by a creatinine-clearance criterion (≥50% fall, or ≥ 25% with pre-existing dysfunction); renal injury was also graded by the risk, injury, failure, loss and end-stage kidney disease (RIFLE) classification. We used clinically selected dose categories (2.5, 2.75 and 3.0 mg/kg/day), exploratory classification and regression tree (CART) analysis, multivariable logistic regression and a desirability of outcome ranking.
Results:
The mortality cohort comprised 208 patients (28-day mortality 41.3%) and the nephrotoxicity cohort 163 (nephrotoxicity 49.7%). Mortality declined across dose categories in univariable analysis (trend P = 0.05) but was not independently associated with dose after adjustment. Nephrotoxicity increased with dose, reaching 73% at ≥3.0 mg/kg/day; CART identified a threshold at 2.74 mg/kg/day, above which the RIFLE grade was worse (62.3% of comparisons; P = 0.006). Multivariable analysis confirmed this (adjusted odds ratio 2.60, 95% confidence interval 1.25-5.43). The desirability of outcome ranking did not differ across dose groups.
Conclusions:
A higher polymyxin B maintenance dose was associated with increased nephrotoxicity, particularly above approximately 2.75 mg/kg/day. The mortality estimates were imprecise and did not exclude a clinically important effect. This single-centre threshold is hypothesis-generating and requires validation before it could inform a clinical dose ceiling.
Related Concept Videos
 01:21
Drug Dosing: Obese Patients
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
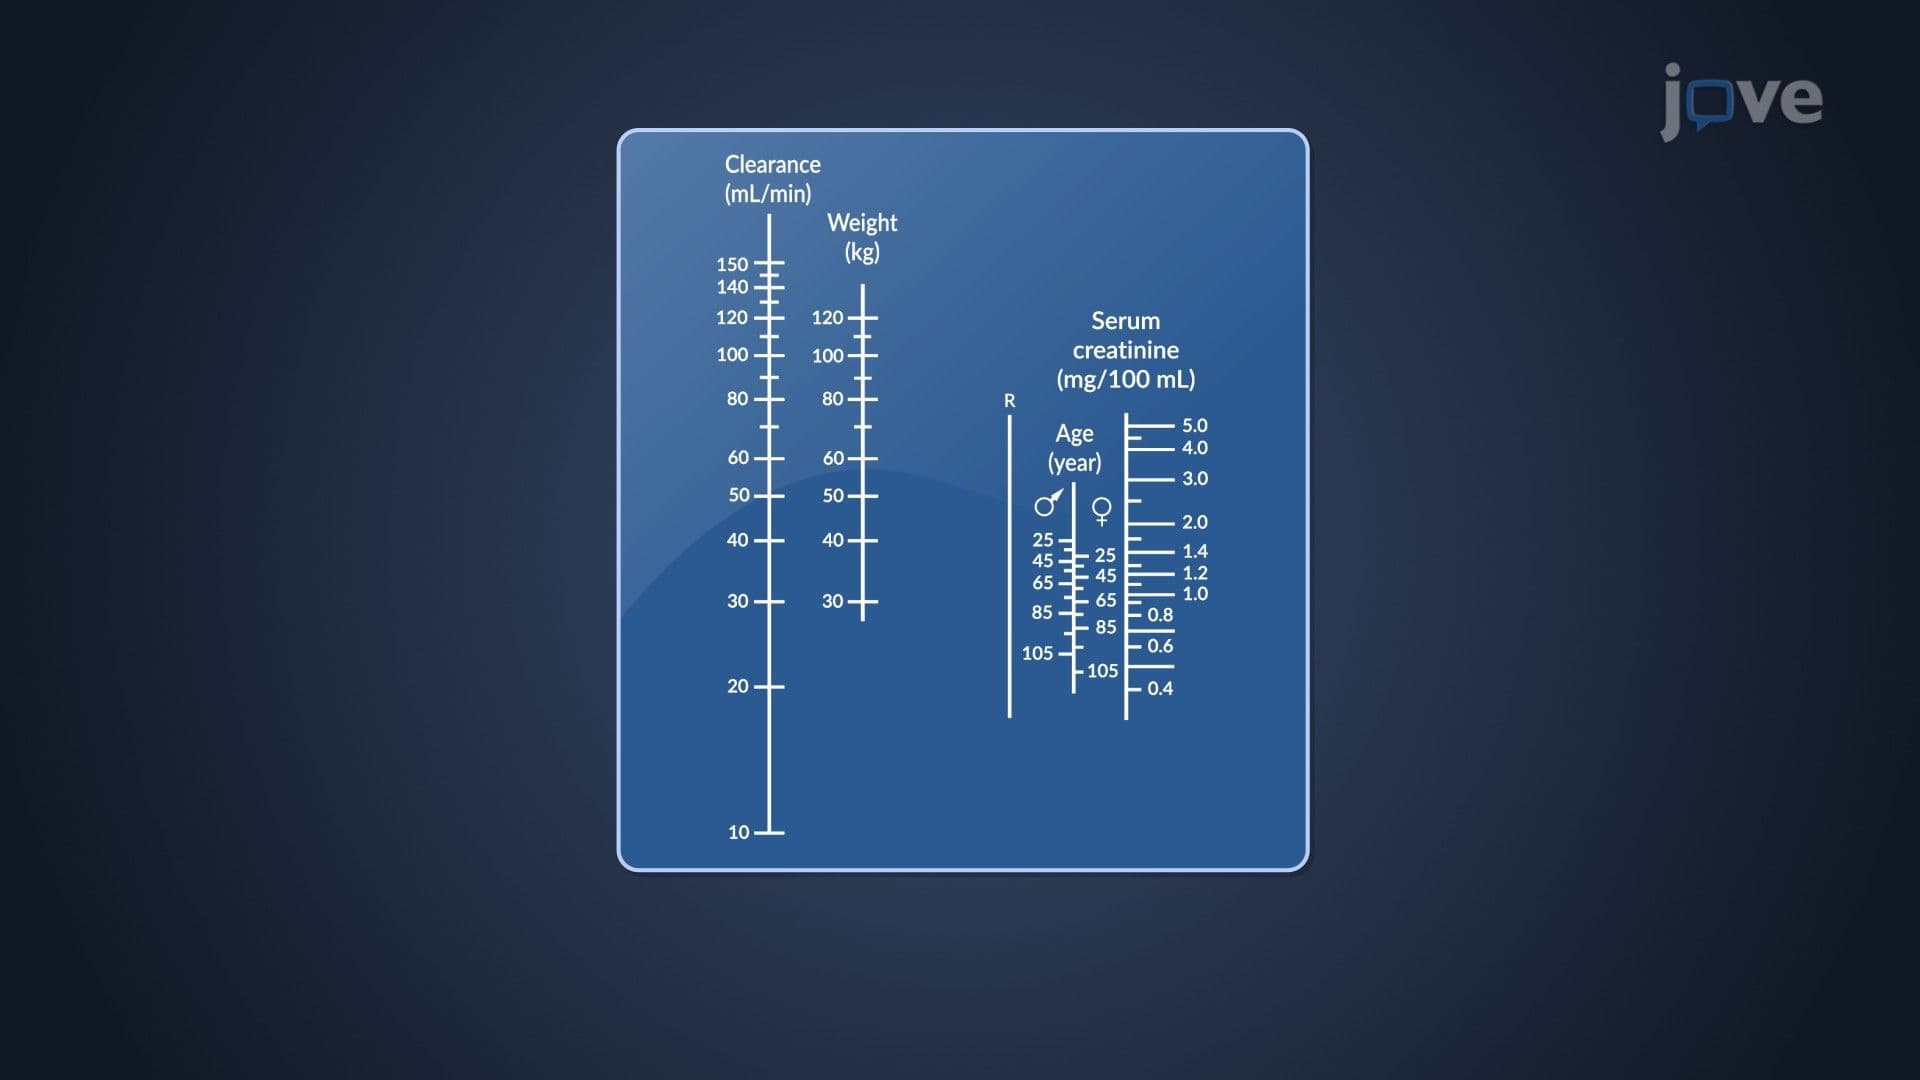 01:23
Dosage Regimen Designs: Nomograms and Tabulations
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant