Related Experiment Video
Updated: Sep 20, 2026
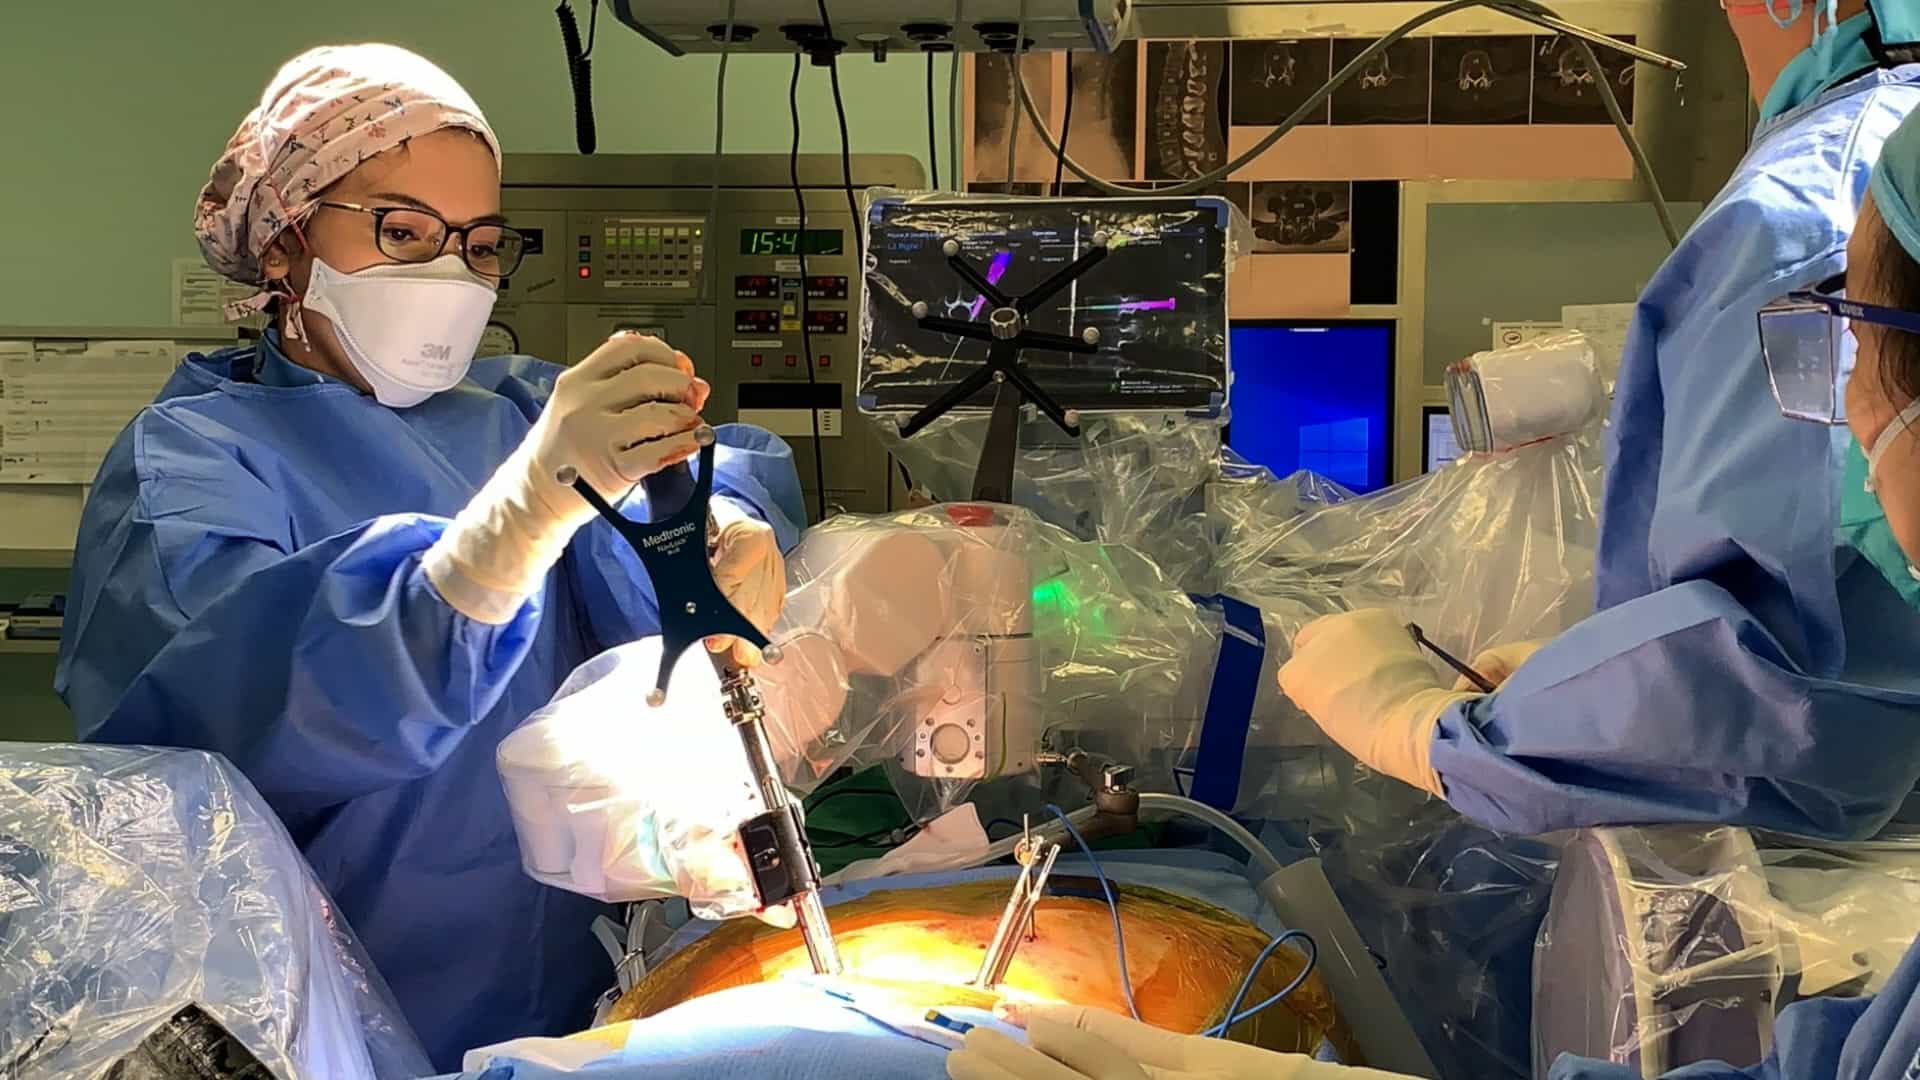
Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Association of diffuse idiopathic skeletal hyperostosis with postoperative outcomes following surgery for
Hao Chen1,2, Shanxi Wang1,2, Xuegang He1,2
1Department of spine surgery, Honghui Hospital, Xi'an Jiaotong University, Shaanxi, 710054, Xi'an, China.

Objective:
To determine whether diffuse idiopathic skeletal hyperostosis (DISH), particularly when extending into the lumbar spine (L-DISH), is associated with postoperative outcomes after surgery for degenerative lumbar disease.
Methods:
Multiple bibliographic, trial, and Japanese literature databases were searched from inception through June 30, 2026. Comparative DISH or L-DISH studies and within-DISH prognostic or surgical-strategy studies were eligible. Decompression and short-segment interbody fusion evidence were analyzed separately, and overlapping cohorts were resolved for each outcome. Study-specific adjusted estimates were prioritized for inference. Crude risk ratios (RRs) from unadjusted event counts were retained only as secondary, illustrative k = 2 syntheses. Risk of bias was assessed at the result level, and certainty was graded by outcome.
Results:
Fifteen reports representing 12 independent studies, all retrospective and from Japan, were included. Adjusted study-specific associations for reoperation pointed toward higher risk with DISH/L-DISH after short-segment fusion (hazard ratio [HR], 5.46; 95% confidence interval [CI], 2.25-13.30), mixed lumbar procedures (HR, 2.049; 95% CI, 1.199-3.503), and decompression (HR, 3.37; 95% CI, 1.31-8.69), but effect measures, adjustment sets, and time horizons differed and were not pooled. Secondary crude syntheses contained only 2 cohorts each: decompression RR, 2.50 (95% CI, 1.53-4.08), and fusion RR, 3.93 (95% CI, 2.00-7.70). Modified Hartung-Knapp intervals were 0.10-60.12 and 0.05-310.05, respectively. Radiographic nonunion or pseudarthrosis estimates differed markedly (RR, 12.44; 95% CI, 4.39-35.32; and RR, 1.75; 95% CI, 1.07-2.88) and were not pooled. Certainty was very low.
Conclusion:
Primary adjusted associations and supportive crude observational estimates were directionally consistent with greater reoperation risk, but sparse data, incomplete confounding control, time-dependent outcome handling, and an exclusively Japanese evidence base make the magnitude uncertain and limit transportability. DISH/L-DISH may be regarded as a possible risk marker, not a causal determinant or a basis for a universal operative strategy.
Prospero Number:
CRD420261454437.
