Related Experiment Video
Updated: Sep 20, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Concentration-to-Dose Ratio Differences Between Once-Daily Tacrolimus Formulations: A Five-Year Real-World
Adam Varga1, Kornelia Borbasne Farkas2, Karoly Kalmar Nagy3
1Department of Surgery, University of Pecs, Ifjusag Street 13, Pecs, 7624, Hungary. varga.adam@pte.hu.

Background And Objective:
Tacrolimus is a cornerstone of immunosuppression after kidney transplantation; however, its narrow therapeutic window and substantial inter- and intra-individual pharmacokinetic variability complicate dose optimization. Extended-release tacrolimus (ER-Tac) and MeltDose® prolonged-release tacrolimus (LCP-Tac) formulations have been developed to improve bioavailability and stabilize drug exposure. The concentration-to-dose (C/D) ratio has emerged as a clinically relevant surrogate marker of tacrolimus metabolism and apparent clearance. We aimed to evaluate long-term differences in C/D ratio dynamics between once-daily tacrolimus formulations.
Methods:
In this single-center retrospective study, 100 de novo kidney transplant recipients (2015-2018) received either ER-Tac (n = 50) or LCP-Tac (n = 50). Tacrolimus trough concentrations, daily doses, and laboratory parameters were collected up to 60 months post-transplantation. Longitudinal pharmacokinetic assessment was performed using repeated C/D ratio measurements. Linear mixed-effects models adjusted for recipient age and time post-transplantation were used for analysis. Clinical outcomes included delayed graft function (DGF), biopsy-proven acute rejection (BPAR), new-onset diabetes after transplantation (NODAT), and mortality.
Results:
LCP-Tac-treated patients required significantly lower daily doses from month 3 onward (p < 0.001) while maintaining comparable trough concentrations. The C/D ratio was consistently higher in the LCP-Tac group, reaching statistical significance from month 12 (p = 0.015) and increasing further over time (p < 0.001), suggesting lower apparent tacrolimus clearance and/or greater dose-normalized exposure. A higher proportion of LCP-Tac measurements remained within the predefined therapeutic range throughout follow-up. No significant differences were observed in DGF, BPAR, NODAT, or mortality between groups.
Conclusion:
LCP-Tac was associated with lower dose requirements and higher, more stable C/D ratios compared with ER-Tac, suggesting formulation-dependent differences in tacrolimus pharmacokinetics. The C/D ratio may serve as a simple, clinically applicable surrogate marker for long-term pharmacokinetic monitoring in kidney transplant recipients.
Related Concept Videos
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
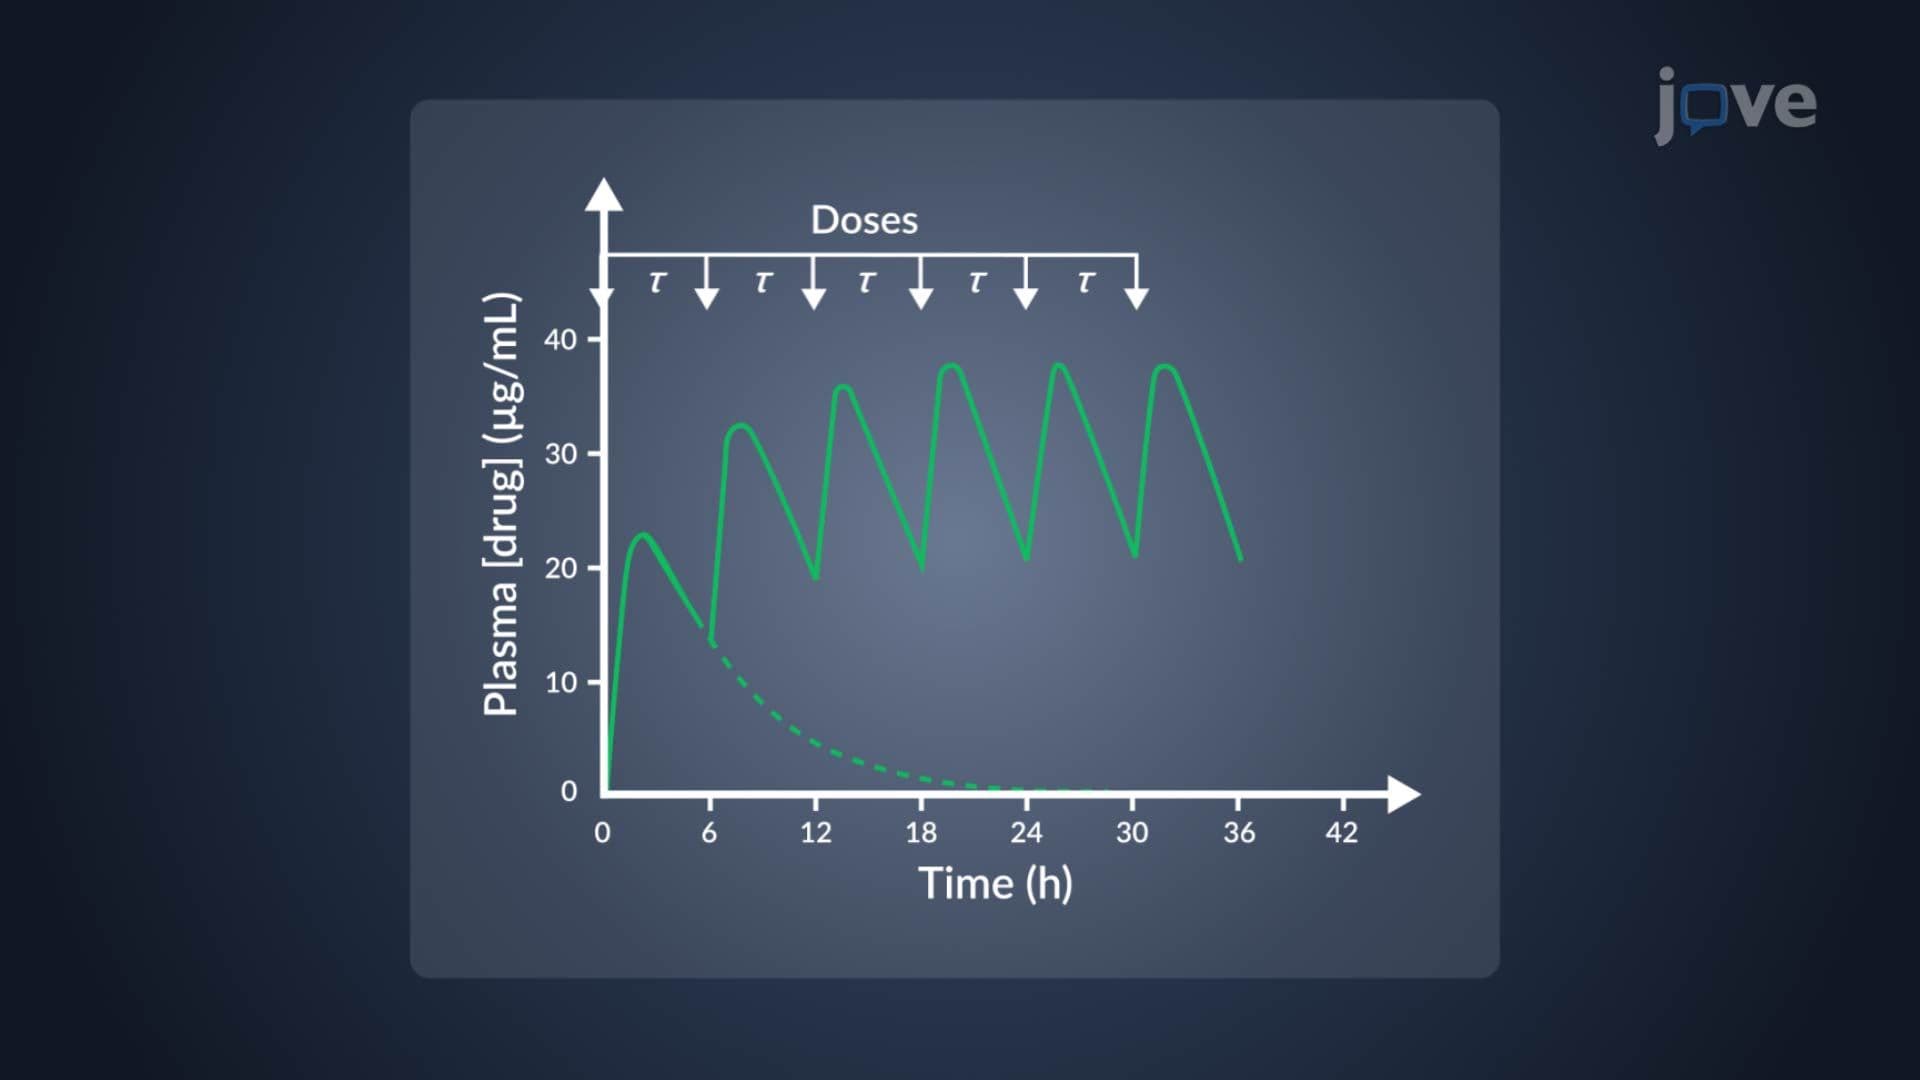 01:25
Dosage Regimen: Multiple Oral Dosage
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:15
Drug Concentration Versus Time Correlation
Two pivotal parameters are the minimum effective concentration (MEC) and the minimum toxic concentration (MTC). The MEC is the lowest drug...
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters