Related Experiment Video
Updated: Sep 20, 2026


Complementary Approaches to Interrogate Mitophagy Flux in Pancreatic β-Cells
Published on: September 15, 2023
Interplay between mitophagy, ferroptosis, and pyroptosis in acute pancreatitis: Regulatory mechanisms and therapeutic
Jialei Li1, Shanqing Gao2, Li Gao1
1Department of Surgery, Shanghai Fengxian District Traditional Chinese Medicine Hospital,Shanghai, China.

Background:
With a very high death rate, acute pancreatitis (AP) is a frequent acute abdominal illness of the digestive system. It is challenging for the conventional notion of "trypsin self digestion" to adequately explain the molecular underpinnings of local inflammation that spreads across the body and the heterogeneity of acinar cell death. The science of programmed cell death has advanced significantly in recent years, and it has been demonstrated that oxidative stress, mitophagy, ferroptosis, and pyroptosis are important factors in AP tissue damage and inflammation amplification. Nevertheless, there hasn't been a methodical integration of the spatiotemporal dynamic interaction and cross-regulatory network among the four.
Methods:
In order to find material on AP and reactive oxygen species (ROS) formation, PINK1/Parkin mediated mitophagy, GPX4 dependent lipid peroxidation defense, and NLRP3/caspase-1/GSDMD mediated pyroptosis, the system searched the Web of Science, PubMed, and Google Scholar databases. The cross-talk linkages between various cell death pathways were compiled and examined, with an emphasis on mechanistic studies and evidence of in vitro and in vivo treatments.
Results:
Ca2 + excess, mitochondrial respiratory chain malfunction, and NOX2 activation work together to cause an explosive build-up of ROS in the early stages of AP, creating a shared ignition event for downstream programmed death. In this network, mitophagy exhibits a typical "double-edged sword" effect: moderate autophagy with intact flux can remove damaged mitochondria and prevent ROS and mitochondrial DNA release, thereby suppressing ferroptosis and pyroptosis at the same time; insufficient autophagy, impaired lysosomal clearance, or abnormally enhanced autophagy can result in mitochondrial accumulation, which exacerbates oxidative stress. Excessive ROS depletes glutathione and suppresses GPX4 activity at the level of cell death execution process, causing membrane lipid peroxidation and ferroptosis; conversely, activation of the NLRP3 inflammasome via TXNIP dissociation causes pro-inflammatory pyroptosis mediated by caspase-1/GSDMD. It is noteworthy that GPX4 may act as a shared molecular interface that limits both forms of death; its deactivation not only promotes ferroptosis directly but may also facilitate GSDMD pore formation through lipid peroxidation, suggesting a potential functional connection between ferroptosis and pyroptosis. More importantly, available evidence suggests that a positive feedback loop involving mitochondrial injury, antioxidant depletion, ferroptotic and pyroptotic signaling, and inflammatory amplification may contribute to the progression of AP from local pancreatic injury to SAP and distant organ damage. DAMPs such as HMGB1 and ATP released during ferroptotic injury, together with IL-1β, IL-18, and other inflammatory mediators released during pyroptosis, may further amplify oxidative stress and impair GPX4-dependent antioxidant defense.
Conclusion:
Current evidence suggests that ferroptosis and pyroptosis may be functionally interconnected in AP through shared mediators such as ROS, DAMPs, and alterations in membrane lipid oxidation. Such interactions may contribute to the progression of AP from localized pancreatic injury to systemic inflammation and severe disease. However, the causal relationships among these pathways have not yet been fully established within a unified AP-specific experimental system. These findings suggest that a multi-level cooperative strategy integrating mitochondrial homeostasis restoration, GPX4 preservation, and NLRP3/GSDMD suppression may offer advantages over isolated blockade of a single death pathway. The optimal timing of intervention may vary across different stages of AP, although this stage-dependent therapeutic concept remains hypothesis-generating and requires direct experimental validation. This integrated perspective may provide new insights into therapeutic strategies for SAP.

Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:24
Chronic Pancreatitis I: Introduction
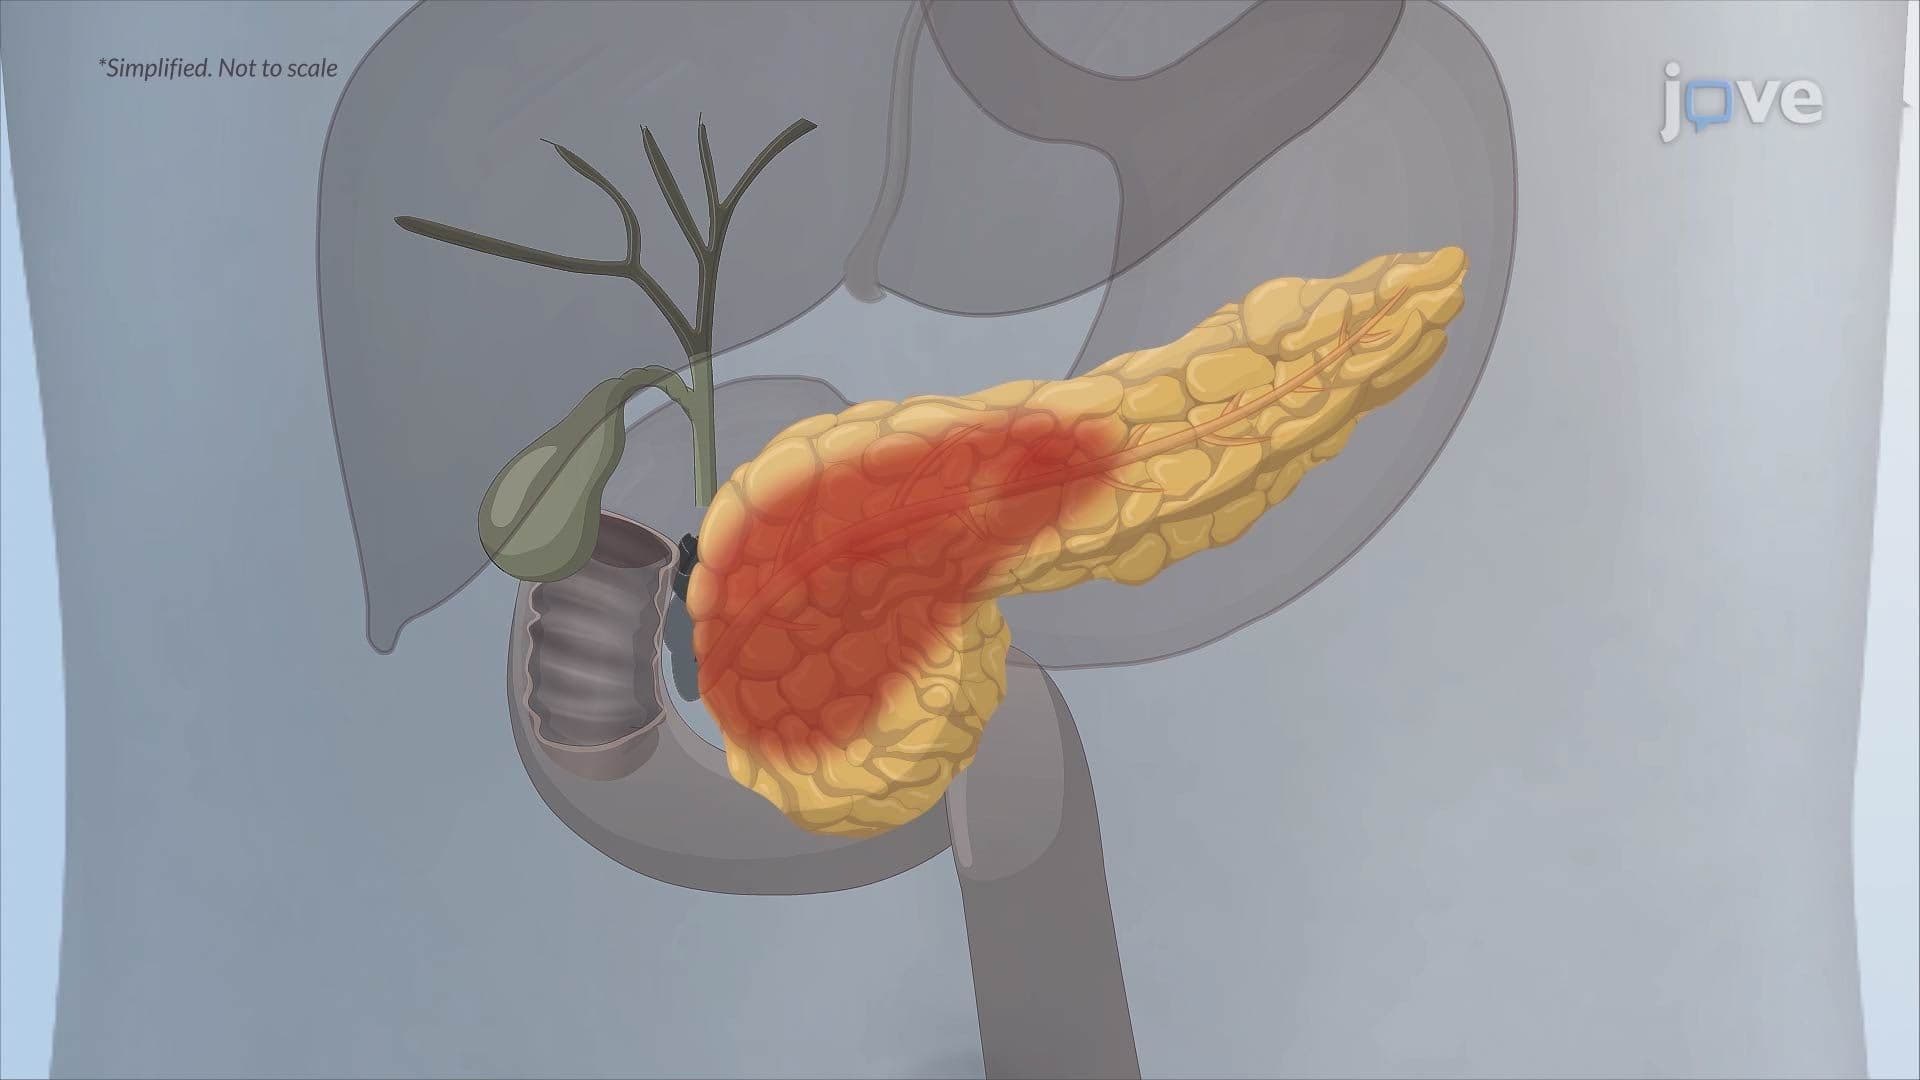
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction