Related Experiment Video
Updated: Sep 20, 2026


Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Rotator cuff arthropathy impairs shoulder mobility and drives compensatory spine and pelvic motion during overhead
Nicholas Morriss1, Patrick Castle1, Dylan N Greif1
1Department of Orthopedics, University of Rochester Medical Center, Rochester, NY, United States.

Background:
Rotator cuff arthropathy is associated with progressive shoulder dysfunction and pain, leading to impaired performance of activities of daily living. While loss of glenohumeral motion is well recognized, the extent to which patients adopt whole-body compensatory strategies during functional overhead tasks remains incompletely defined. Quantifying these compensatory strategies may improve functional assessment and identify secondary biomechanical adaptations that contribute to disability.
Methods:
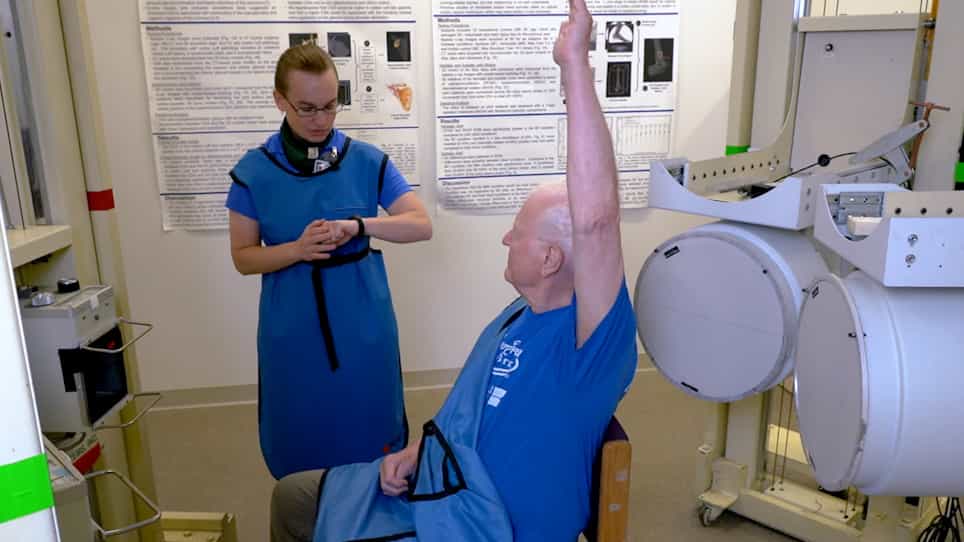
Sixty-two patients with unilateral rotator cuff arthropathy performed a standardized overhead reach task using both the symptomatic and contralateral asymptomatic shoulders. Three-dimensional motion capture was used to quantify shoulder kinematics as well as cervical spine, lumbar spine, and pelvic motion throughout task execution. Peak joint angles were compared between sides to characterize motion deficits and compensatory strategies.
Findings:
Compared with the asymptomatic shoulder, rotator cuff arthropathy shoulders demonstrated significant reductions in flexion (57.4° vs 120.4°), abduction (28.7° vs 44.9°), and internal rotation (33.5° vs 61.7°) (all p < 0.001). Use of the symptomatic shoulder was associated with increased cervical spine extension, reflected by reduced flexion (19.1° vs 32.5°, p < 0.001), and decreased lateral bending (9.2° vs 14.6°, p < 0.001). Lumbar spine kinematics demonstrated greater axial rotation (24.0° vs 18.6°, p < 0.001) and increased extension (-4.0° vs -5.2°, p < 0.001). Pelvic motion also increased, with greater contralateral rotation observed during symptomatic shoulder use (-7.7° vs -3.3°, p < 0.001).
Interpretation:
Rotator cuff arthropathy results in profound reductions in shoulder mobility during functional overhead reaching, accompanied by systematic compensatory increases in cervical spine, lumbar spine, and pelvic motion. These altered whole-body kinematic strategies likely redistribute mechanical demands to the axial skeleton and may predispose patients to secondary spine or pelvic pathology. Recognition of these compensations has important implications for surgical decision-making, postoperative expectations, and the design of targeted rehabilitation strategies aimed at restoring function while minimizing compensatory loading.
Related Concept Videos
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:24
Muscle Coordination and Action
Agonists
Agonist muscles, often called prime movers, are the primary muscles responsible for producing a specific movement.