Related Experiment Video
Updated: Sep 20, 2026
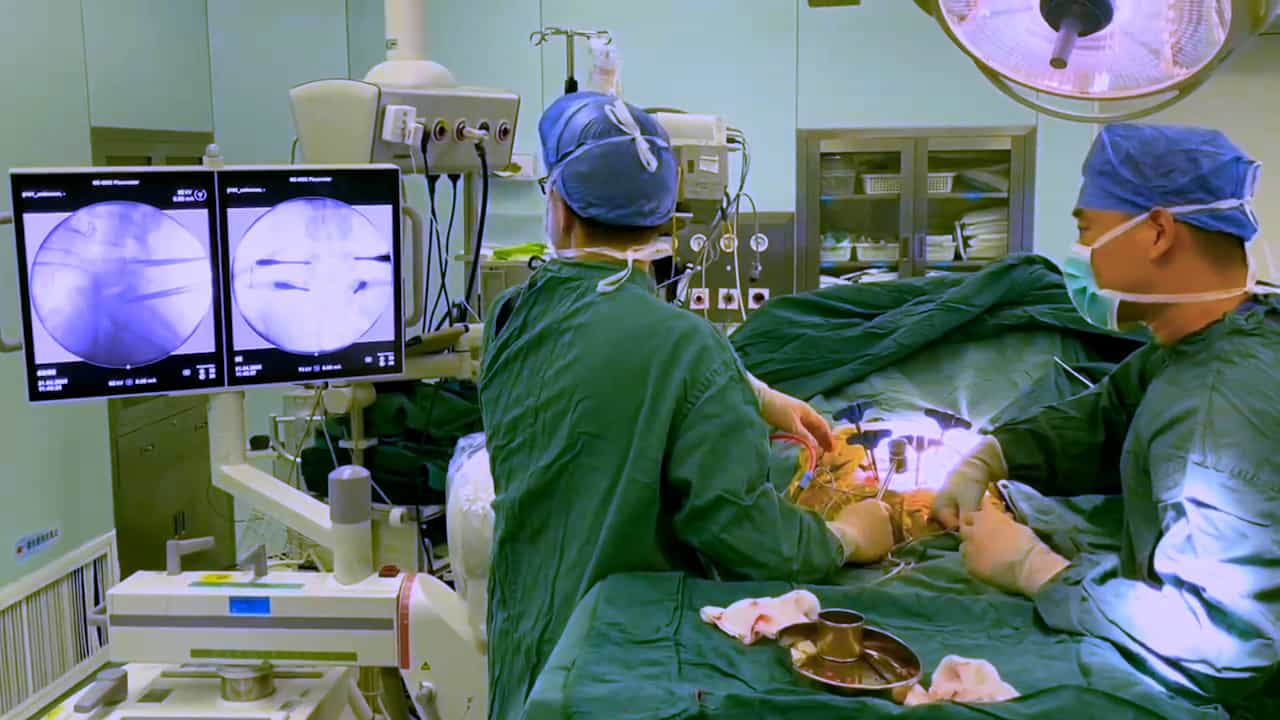

Novel Mini-open Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Primary Hyperparathyroidism and Lumbar Spinal Fusion Outcomes: A Propensity-Matched Cohort Study
Bryce Michael1, Jonathan Sayegh1, Diego Garcia1
1Department of Orthopaedic Surgery, University of Arizona, Tucson, Arizona.

Introduction:
Hyperparathyroidism (HPT) is associated with deterioration of bone microarchitecture, but its impact on lumbar fusion outcomes is poorly characterized, and existing spine data largely reflect dialysis-driven secondary HPT. We evaluated whether preoperative primary HPT is associated with complications after lumbar fusion, and whether preoperative parathyroidectomy modifies these outcomes.
Methods:
Using the TriNetX Research Network, we identified adults undergoing lumbar fusion with and without preoperative primary HPT; propensity score matching (1:1) yielded 775 patients per group. A prespecified subgroup compared primary HPT patients with and without preoperative parathyroidectomy (208 per group). Outcomes were pseudoarthrosis, instrumentation failure, revision at 2 and 5 y, and 90-d medical complications, including emergency department (ED) utilization.
Results:
No mechanical outcome differed significantly between groups. At 5 y, instrumentation failure was 3.29% versus 2.48% (risk ratio [RR] 1.33, 95% confidence interval 0.74-2.39; P = 0.34), revision 2.51% versus 2.92% (RR 0.86, 0.47-1.58; P = 0.63), and pseudoarthrosis 7.79% versus 6.73% (RR 1.16, 0.80-1.67; P = 0.43). Ninety-d ED utilization was higher with primary HPT (15.7% versus 11.1%; RR 1.42, 1.10-1.84; P = 0.007); other complications did not differ. The parathyroidectomy subgroup was underpowered, with mechanical events below reporting thresholds.
Conclusions:
Preoperative primary HPT was not associated with increased instrumentation failure, revision, or pseudoarthrosis through 5 y, though confidence intervals do not exclude smaller effects. The principal difference was higher early ED utilization. The underpowered subgroup permitted no conclusion regarding the effect of preoperative parathyroidectomy.