Related Experiment Video
Updated: Sep 20, 2026

The Role of Indocyanine Green Fluorescence in Complex Laparoscopic Cholecystectomy Navigation
Published on: January 31, 2025
Intraoperative Indocyanine Green Fluorescence Angiography for Assessing Intestinal Perfusion in Infants with
Hongyang Li1, Hongxi Liang1, Wei Feng1
1Department of Neonatal Surgery, Children's Hospital of Chongqing Medical University, National Clinical Research Center for Children and Adolescents' Health and Diseases, Ministry of Education Key Laboratory of Child Development and Disorders, Chongqing Municipal Health Commission Key Laboratory of Children's Vital Organ Development and Diseases, Chongqing, People's Republic of China.

Objective:
To evaluate the clinical utility and safety of indocyanine green fluorescence angiography (ICG-FA) during surgery for necrotizing enterocolitis (NEC)-associated colonic strictures in infants, with particular attention to intraoperative decision-making and anastomotic leakage (AL).
Methods:
This retrospective comparative cohort study, conducted in accordance with the STROBE guidelines, included 108 infants who underwent intestinal resection and primary anastomosis for NEC-associated colonic strictures between 2022 and 2024. Patients were classified into an ICG-FA group (n = 45) and a non-ICG group (n = 63) according to whether intraoperative fluorescence angiography was used. Baseline characteristics, operative variables, and postoperative outcomes were compared. The primary endpoint was AL; secondary endpoints included ICG-guided surgical plan modification, perioperative recovery, and overall morbidity. Statistical significance was defined as P < .05.
Results:
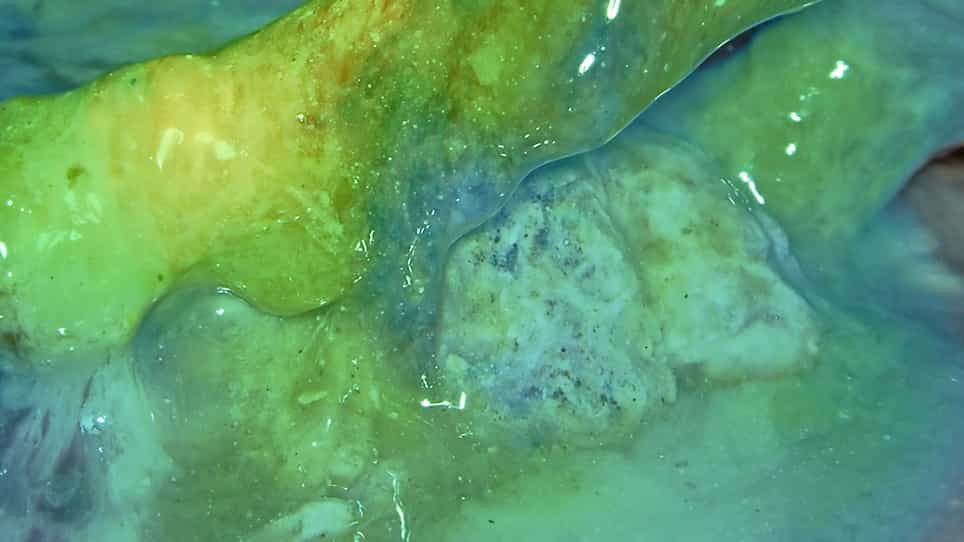
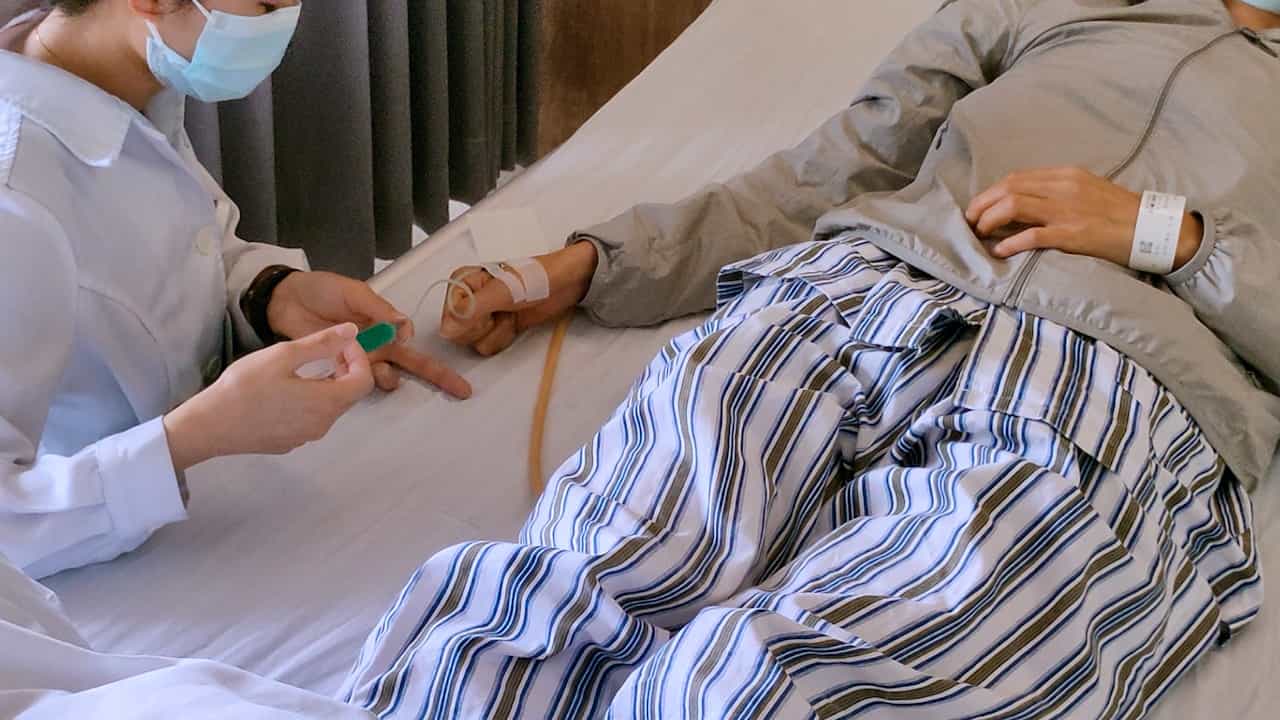
Baseline characteristics were comparable between the two groups. ICG-FA prompted modification of the planned resection margin in 5 of 45 patients (11.11%), whereas no comparable modification was documented in the non-ICG group (P = .035). The median time to adequate fluorescence visualization was 20 seconds, and no ICG-related adverse events occurred. AL was observed in one patient in the non-ICG group (1.59%) and in no patients in the ICG-FA group; however, this difference was not statistically significant (P = .395). Other postoperative complications and overall morbidity were similar between groups. During a median follow-up of 15 months, all complications resolved with conservative treatment or secondary intervention.
Conclusion:
ICG-FA is a safe and feasible adjunct for real-time assessment of intestinal perfusion in infants with NEC-associated colonic strictures. Although this study was not powered to demonstrate a statistically significant reduction in AL, ICG-FA helped identify potentially underperfused margins and supported individualized resection planning. Larger prospective studies with standardized fluorescence assessment are required to confirm its effect on anastomotic outcomes.