Related Experiment Video
Updated: Sep 20, 2026


Endoscopic Septoplasty with Limited Two-line Resection: Minimally Invasive Surgery for Septal Deviation
Published on: June 20, 2018
Floor-reaching middle turbinate variants: Dual pathophysiology and descriptive terminology
Ibrahem H Erwe1, Mohammed A Alzahrani2, Abdulbari A Alzahrani2
1Department of Otorhinolaryngology - Head and Neck Surgery, Aseer Central Hospital, Abha, Saudi Arabia. ierwe.ent@gmail.com.

Purpose:
The Bolger classification defines three concha bullosa types but does not account for extreme middle turbinate variants extending to the nasal floor. Only one prior report provided quantitative measurements (45mm). We present four patients (32-52mm vertical height) and distinguish primary pneumatization from secondary disease-filled expansion as the underlying mechanisms.
Methods:
We retrospectively reviewed patients undergoing endoscopic surgery from January 2021 to December 2024 at a tertiary rhinology center. Four patients with middle turbinate extension to within ≤3mm of the nasal floor underwent systematic evaluation including high-resolution CT with standardized measurements (vertical height, width, floor distance), endoscopic examination, histopathological analysis, and surgical management with one-year follow-up.
Results:
Four patients demonstrated massive middle turbinate extension with floor contact (32-52mm vertical height); three patients (48-52mm) exceeded the only previously quantified measurement (45mm) by 3-7mm (6.7-15.6%), while Patient 4 (32mm) qualified by floor distance criterion (≤3mm). Patients 1 and 4 represented extreme pneumatization (air-filled concha bullosa, 48mm and 32mm) without sinusitis. Patients 2 and 3 demonstrated secondary pathological expansion (allergic fungal rhinosinusitis 50mm, mucocele 52mm) with sinus involvement. Both mechanisms converged on a similar anatomical endpoint. All patients underwent endoscopic decompression using a systematic anterior-to-posterior technique, with disease-specific adjuncts (sinus clearance, mucocele drainage, frontal sinusotomy) added for Patients 2 and 3, achieving excellent outcomes in all four.
Conclusion:
Floor-Reaching Middle Turbinate Variants represent a clinically significant pattern requiring recognition in radiological reporting and surgical planning. Because both mechanisms carry similar surgical implications, descriptive rather than classificatory terminology is warranted. Multicenter validation with standardized measurements is needed before formal classification.

Related Concept Videos
 01:29
Anatomy of Respiratory System I: Upper Respiratory Tract
Nose and nasal cavity
The nose and nasal cavity represent the main external openings of the respiratory tract.
 01:23
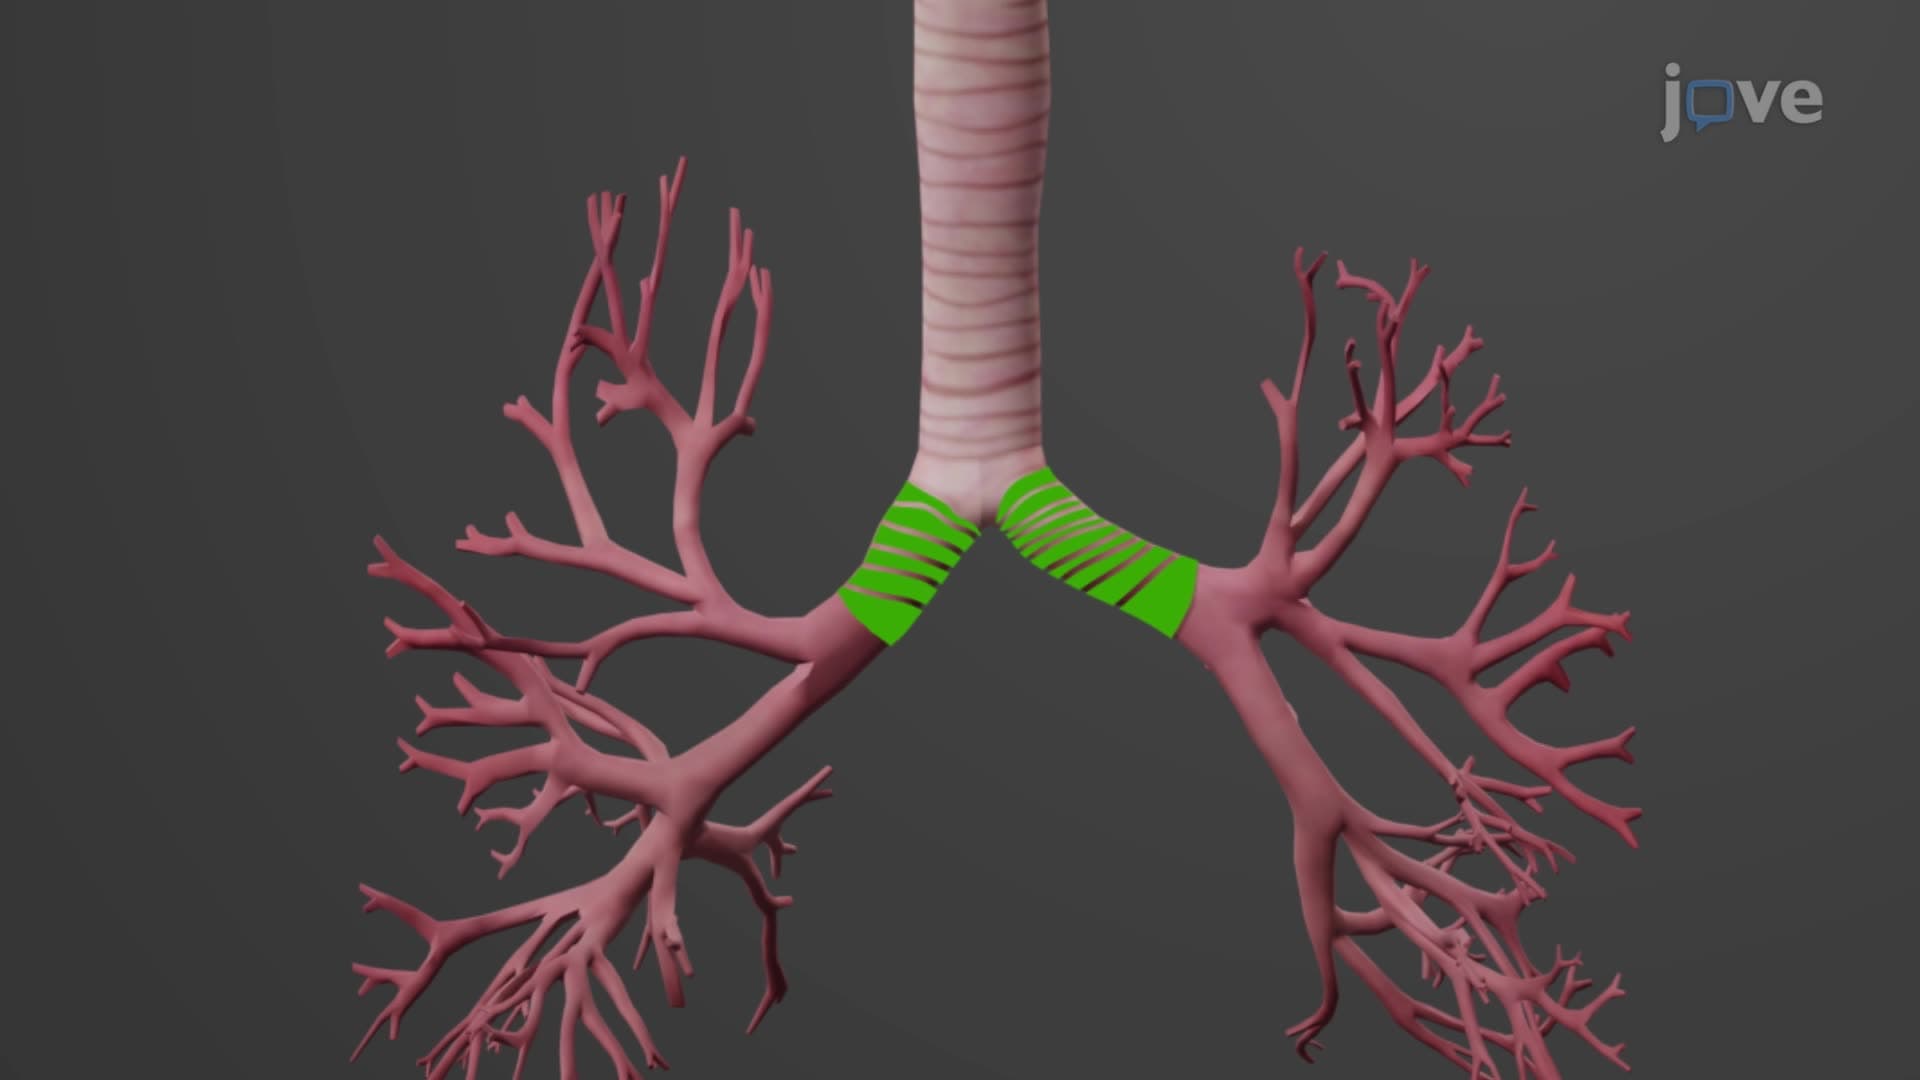
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:31
Anatomy of Respiratory System II: Lower Respiratory Tract
The Larynx
It is located between the pharynx and the trachea, acts as a passageway for air, and hosts several critical structures, such as the epiglottis, vocal cords, and glottis. The epiglottis acts as a gateway, guiding food to the...
 01:24
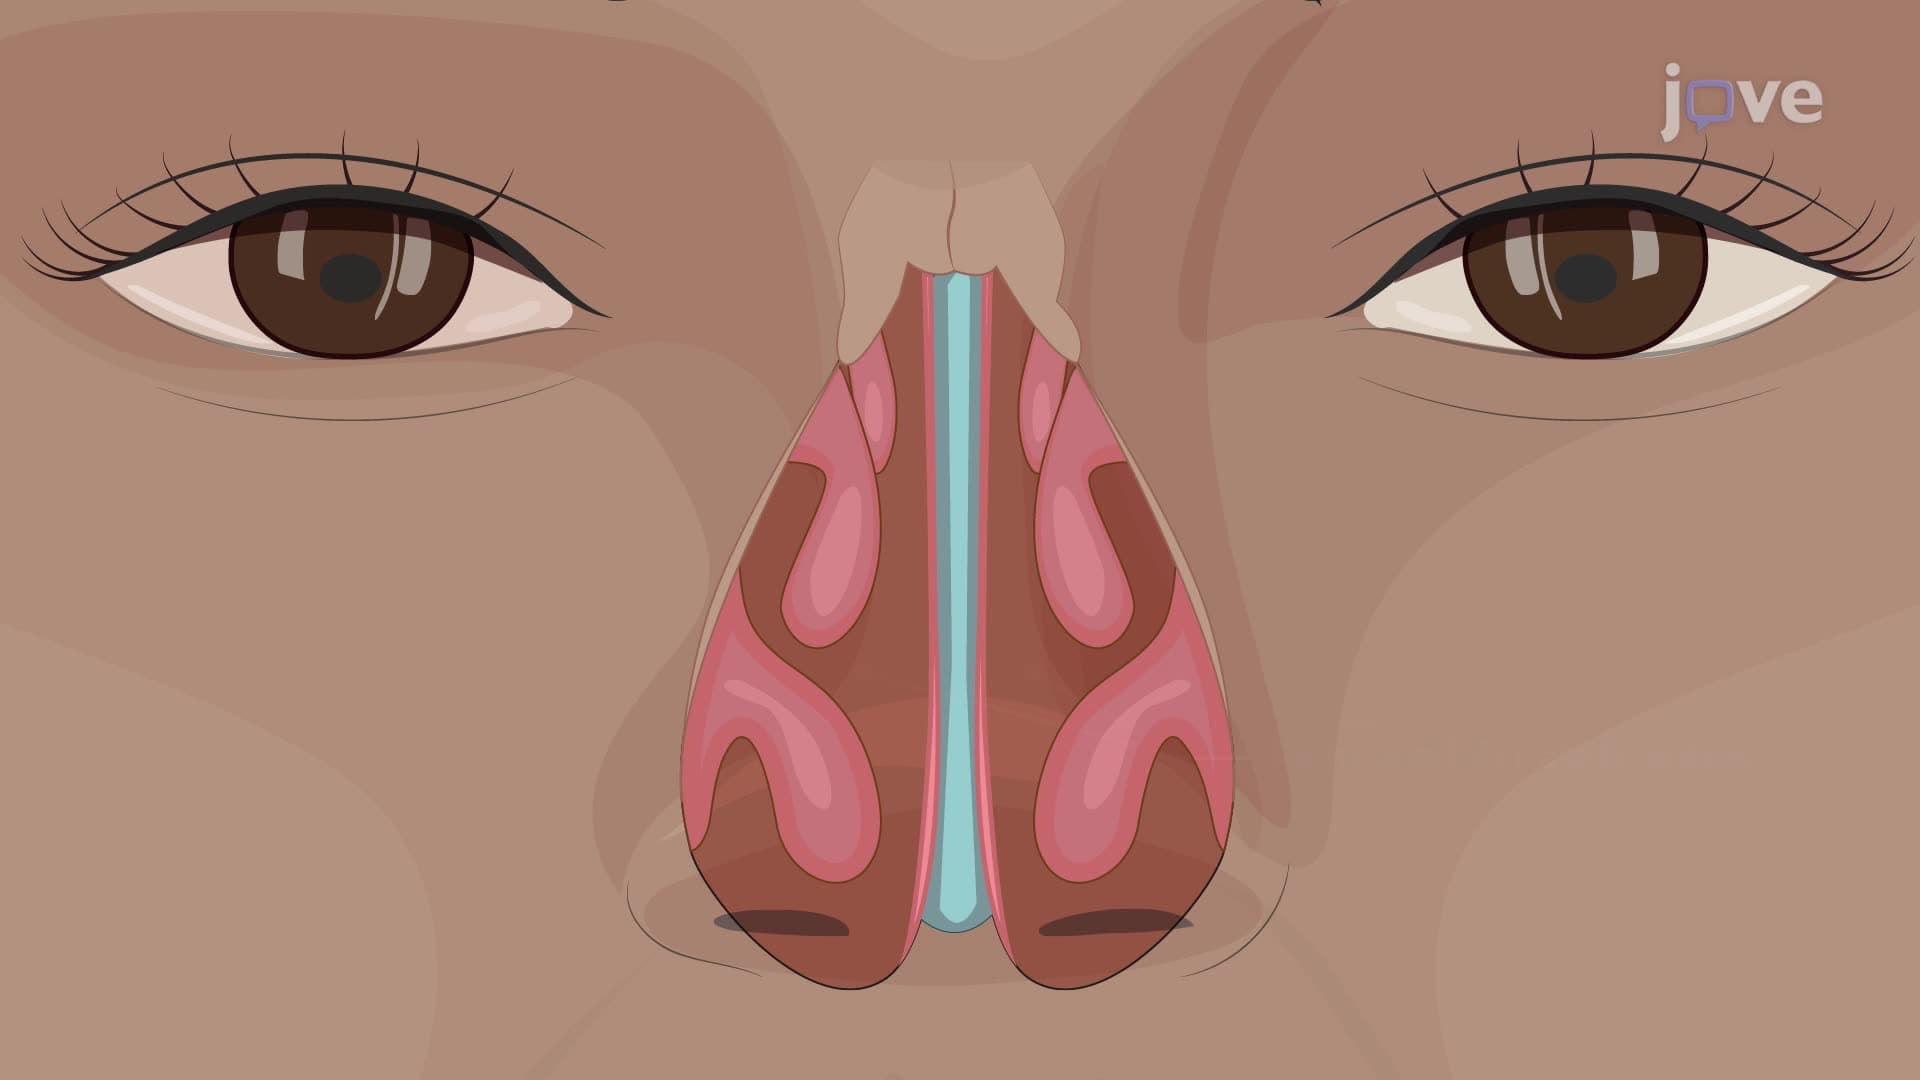
Nose and Nasal Cavity
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...