Related Experiment Video
Updated: Sep 20, 2026
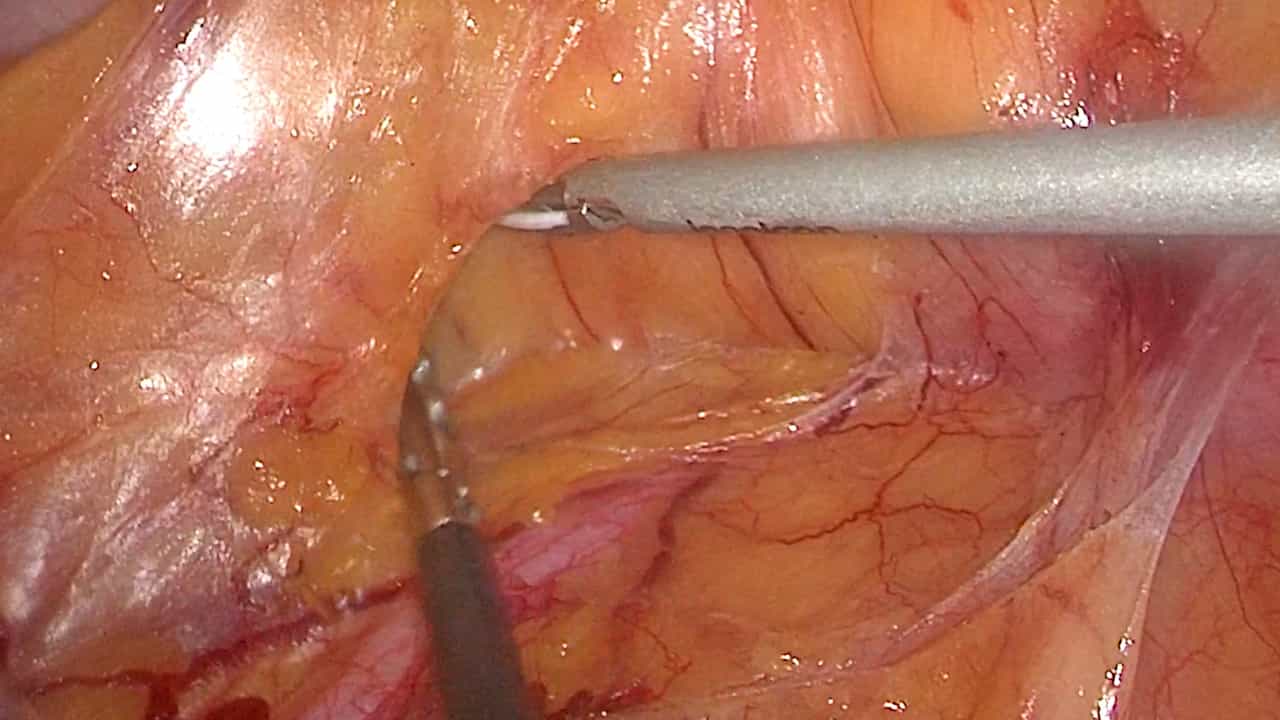

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Laparoscopic versus open emergency colonic resection for obstruction: a multicentre retrospective cohort study
Joline de Groof1, Silvia Marchesi2,3, Ellie Pearce1
1Department of Colorectal Surgery, Royal Surrey County Hospital, Guildford, UK.

Background:
Despite its established benefits in elective colorectal surgery, the adoption of laparoscopy in the emergency setting remains limited. This retrospective international multicentre study assesses laparoscopic and open colonic resection in patients with acute benign or malignant colonic obstruction.
Methods:
Patients were included between 2022 and 2023. Intraperitoneal free air on imaging was an exclusion criterion. Primary outcomes were the Comprehensive Complication Index (CCI) and length of stay (LOS). Secondary outcomes included postoperative pain management, re-operation, 30- and 90-day mortality, R0-resection and lymph node yield when applicable, intraoperative bleeding, anastomosis and operative time.
Results:
Out of 144 patients, 73 were eligible. Forty-three (58.9%) patients underwent open and 30 (41.1%) laparoscopic resections. Obstructions were equally distributed between the right and left colon. Patients in the open group were older (77.1 vs. 61.7 years, p < 0.001). Clavien-Dindo II-V complications were more common (69.8% vs. 33.3%, p = 0.002) and the CCI was higher (27.1 vs. 7.9, p < 0.001) after open surgery. LOS was significantly longer after open surgery (14 (IQR 8-19) vs. 6 (IQR 5-9) days (p < 0.001)). Postoperative pain was managed with patient-controlled opioids and/or oral analgesics in 86.7% after laparoscopic surgery while an epidural was used in 76.7% after open surgery (p < 0.001). Other secondary outcomes were comparable between the groups.
Conclusion:
Laparoscopic emergency resection in patients with acute benign or malignant colonic obstruction was associated with lower postoperative morbidity, shorter LOS and less intensive postoperative analgesic requirements in a selected cohort. However, these findings should be interpreted cautiously given substantial differences in baseline characteristics and surgeon specialization between groups.

