Related Experiment Video
Updated: Sep 20, 2026

Clinical Anthropometrics and Body Composition from 3-Dimensional Optical Imaging
Published on: June 7, 2024
Agreement and repeatability between manual anthropometry and mobile 3D digital anthropometry in young adults
Beatriz Nácher-Fernández1, Raquel Vaquero-Cristóbal2, Mario Albaladejo-Saura3
1Instituto de Biomecánica de Valencia, Universitat Politècnica de Valéncia, Valéncia, Spain.

Background:
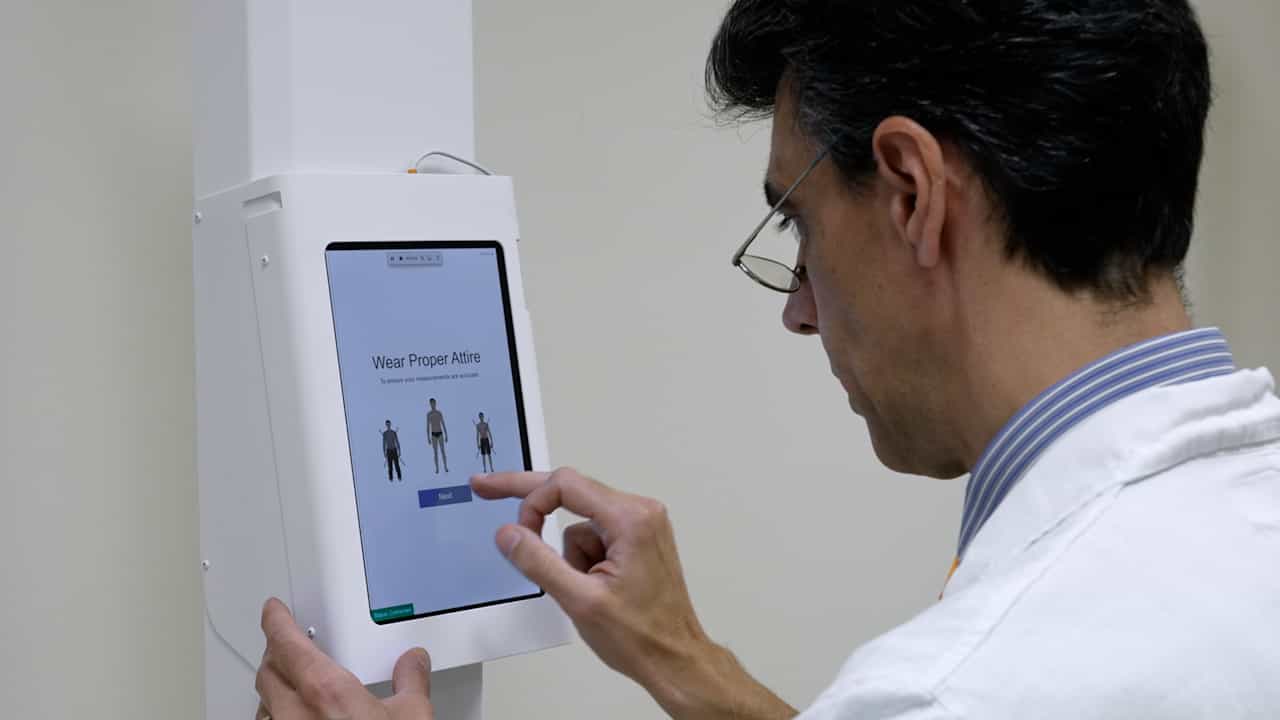
Mobile 3D digital anthropometry has emerged as a rapid and accessible alternative to manual anthropometry. However, evidence regarding its agreement with manual methods and its suitability for interchangeable use remains limited, particularly when raw anthropometric variables are considered. This study aimed (a) to assess differences between manual anthropometry -following ISAK protocol- and digital anthropometry -using 3Davatar/Body mobile phone application- and (b) to evaluate the agreement between both methods.
Methods:
A cross-sectional study was conducted in 264 young adults (160 males and 104 females). Participants underwent manual anthropometric assessment performed by ISAK level 3 accredited anthropometrists, and digitized in 3D using the phone-based digital anthropometry application by non-certified users. Test-retest repeatability was evaluated using the standard error of measurement (SEM) and coefficient of variation (CV), while agreement between methods was evaluated using mean bias, Lin's concordance correlation coefficient (CCC), and Bland-Altman analysis.
Results:
Intra-rater manual anthropometry showed good repeatability, with CV values generally below 2% for most girths and lengths. Digital anthropometry demonstrated good repeatability for girths and selected heights, particularly waist, hip, and lower-limb girths (CV = 0.8-1.5%), but lower repeatability for lengths of the arms and some breadths (CV > 2%). Trunk depths showed the lowest repeatability for both techniques, (CV > 2%). Significant systematic differences were observed between methods for most variables (p ≤ 0.05), with digital measurements tending to overestimate girths and breadths and underestimate heights and lengths compared to manual values. CCC values exceeded 0.80 only for waist girth (0.94), hip girth (0.91) and iliospinale height (0.93-0.94).
Conclusions:
Phone-based application 3D digital anthropometry demonstrates good repeatability for selected variables but shows systematic bias and limited agreement compared with manual anthropometry. Furthermore, the level of training and expertise of the technicians performing anthropometric data collection or operating the phone-based application is crucial for ensuring data reliability. Nonetheless, 3D digital anthropometry offers a simpler and faster assessment process and enables remote data collection, making it particularly useful in time-constrained or non-critical settings. Digital measurements can be readily integrated with health-related metrics and easily repeated when necessary. Although these methods should not currently be considered interchangeable for precise anthropometric assessment in young adults, the application of digital anthropometry in clinical practice may still be feasible, provided that method-specific reference values and classification criteria are developed through further research, similarly to the standards developed for manual anthropometry. In addition, incorporating a certification for the use of the application and an adaptive repeatability approach -such as that proposed by ISAK protocols- into digital acquisition procedures may further enhance measurement reliability.