
Exercise hemodynamics in adults with Fontan circulation assessed by noninvasive impedance cardiography
Agnieszka Bartczak-Rutkowska1, Ewa Straburzyńska-Migaj1, Sonia Nartowicz1
1Department of Cardiology, Poznan University of Medical Sciences, Poznan, Poland.

Background:
Exercise intolerance is a hallmark of Fontan physiology despite preserved resting hemodynamics. The relative roles of stroke volume, chronotropic response, and vascular adaptation during exercise remain incompletely defined in adults with Fontan circulation.
Methods:
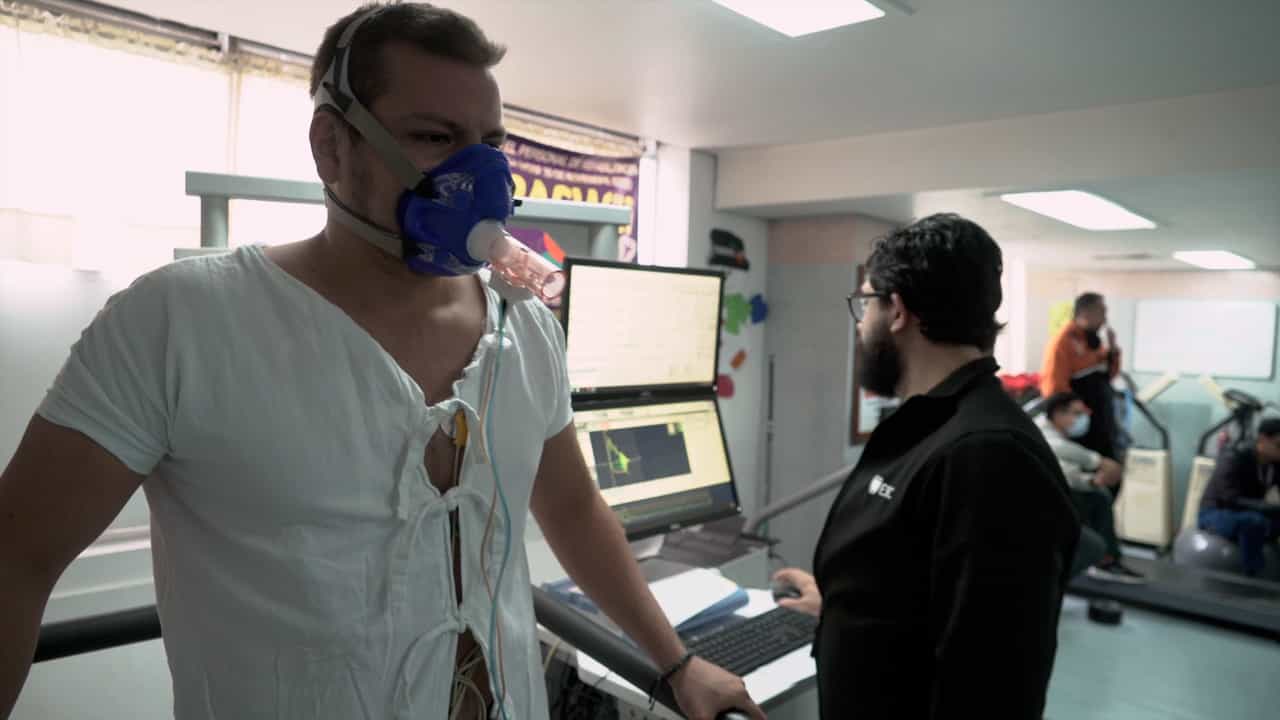
In this prospective observational study, 27 adults with Fontan circulation were enrolled, of whom 22 with complete cardiopulmonary exercise testing (CPET) and impedance cardiography data were included in the final analysis. Twenty-five healthy controls underwent the same protocol. Stroke volume (SV), heart rate (HR), cardiac output (CO), cardiac index (CI), and systemic vascular resistance (SVR) were assessed at rest, at the ventilatory threshold (VT), and at peak exercise. Between-group differences and within-Fontan exploratory correlations between hemodynamic parameters and CPET-derived indices were analyzed.
Results:
Resting hemodynamics were comparable between groups. During exercise, Fontan patients exhibited a markedly attenuated cardiovascular response, with lower peak HR (p < 0.001), CO (p < 0.001), and CI (p < 0.001), and higher SVR (p = 0.01). Stroke volume was reduced at peak exercise (p = 0.045) but did not correlate with exercise capacity. In contrast, peak HR correlated with VO2% predicted (r = 0.52, p = 0.01), and chronotropic incompetence was associated with reduced cardiac index (r = -0.44, p = 0.043). SVR correlated inversely with VO2 (r = -0.47, p = 0.03).
Conclusions:
Adults with Fontan circulation demonstrate preserved resting hemodynamics but impaired cardiovascular reserve during exercise. Our findings suggest that impaired chronotropic response was closely associated with reduced exercise reserve, but should be interpreted as part of preload-limited Fontan physiology rather than as an isolated causal mechanism. Altered vascular response may contribute, although SVR estimates are relative because CVP was not directly measured. Noninvasive exercise hemodynamic monitoring provides complementary mechanistic insight beyond CPET alone.