Related Experiment Video
Updated: Sep 21, 2026
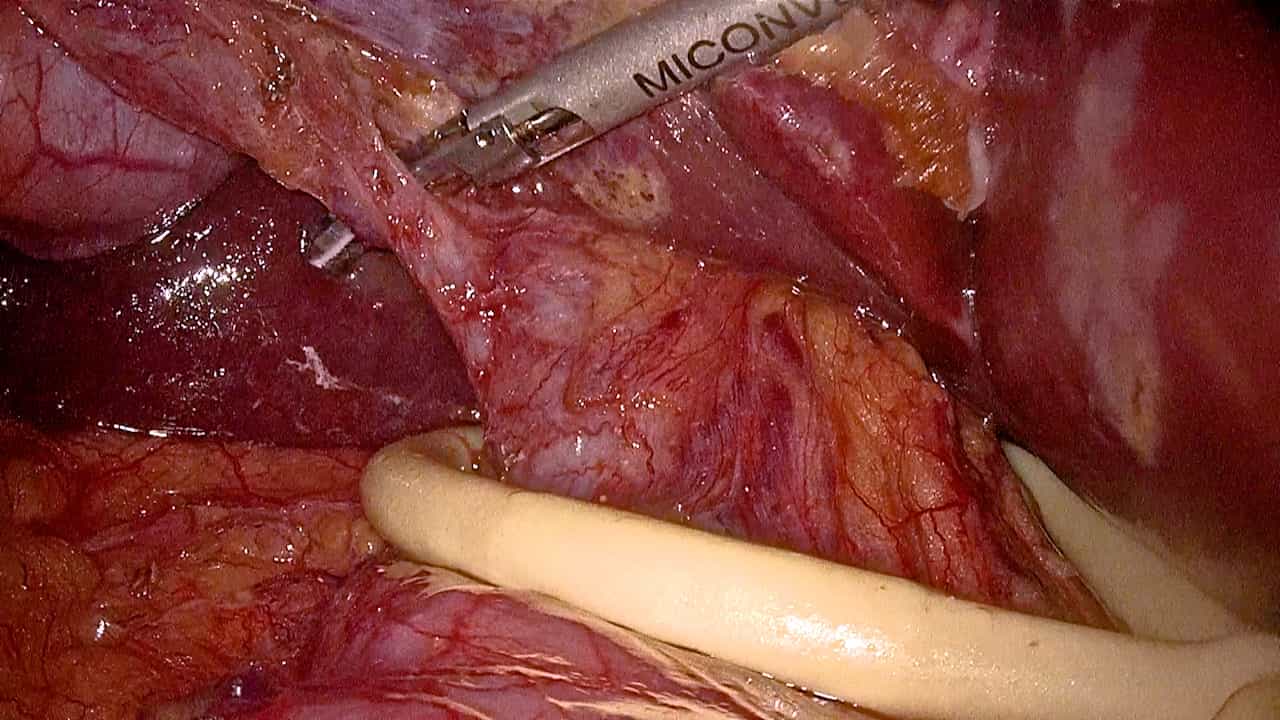
Laparoscopic Anatomic S7+S8d Resection Preserving Inferior Right Hepatic Vein and S6 with Right Hepatic Vein Transection
Published on: December 30, 2025
Right-Lateralized Side-to-side Cavo-caval Anastomosis With Right Hepatic Vein-Extended Cavotomy in Deceased-donor
Sanket Solanki1, Vachan Hukkeri2, Rommel Sandhyav1
1Integrated Liver Care, Aster RV Hospital, Bengaluru, Karnataka, India.

Background/Aims:
Hepatic venous outflow obstruction (HVOO) remains a persistent complication of deceased-donor liver transplantation (DDLT). Established anastomotic approaches modify orifice calibre or clamping strategy but do not address the lateral orientation of the outflow reconstruction relative to the graft's natural position within the right subphrenic space.
Methods:
We describe the right-lateralized side-to-side cavo-caval anastomosis with right hepatic vein-extended cavotomy (STSCCA-RHV). A partial side-biting clamp is applied at the right hepatic vein orifice and a 4-cm cavotomy extended inferiorly along the right lateral inferior vena cava wall, aligning the anastomosis with the graft's natural lie and eliminating the anterior hinge point implicated in midline reconstructions. We report a retrospective cohort of 121 consecutive adults undergoing primary DDLT with STSCCA-RHV, performed by a single unified surgical team across five high-volume centres in India (August 2023-August 2025). The primary outcome was clinically significant, intervention-requiring HVOO within 90 days.
Results:
Clinically significant HVOO occurred in 2 of 121 recipients (1.6%; 95% confidence interval: 0.2-5.8%). Both cases were salvaged by single-stent endovascular intervention with no graft loss attributable to outflow failure. Veno-venous bypass was not required in any case. Median operative time was 380 min (interquartile range [IQR]; 320-440), and cold ischaemia time was 185 min (IQR: 160-210). Early allograft dysfunction occurred in 5.8%, primary non-function in 1.7% and acute kidney injury (any Kidney Disease: Improving Global Outcomes stage) in 33.9%, with only 3.3% reaching stage 3. None of the 18 unplanned reoperations (14.9%) involved outflow-related indications. Ninety-day patient and graft survival were 90.1% and 89.4%, respectively.
Conclusion:
The STSCCA-RHV achieved a low HVOO incidence, complete avoidance of veno-venous bypass, and 90-day survival outcomes consistent with contemporary DDLT benchmarks, without additional operative complexity. This anatomy-guided modification to caval reconstruction is technically simple and reproducible and warrants prospective comparative evaluation against standard piggyback and side-to-side techniques.