Related Experiment Video
Updated: Sep 21, 2026

A Suture Technique for Ruptured Annulus Fibrosus Following Decompression Under Percutaneous Transforaminal Endoscopic Discectomy
Published on: January 26, 2024
From Protrusion to Extrusion: Reassessing the Selective Role of Intradiscal Interventions
Babak Eslami1,2, Reza Atef Yekta2,3, Hossein Majedi4,1
1Department of Anesthesiology, Intensive Care and Pain Medicine, Imam Khomeini Hospital Complex, Tehran University of Medical Sciences, Tehran, Iran.

Context:
Extruded lumbar disc herniations are traditionally managed surgically, whereas contained protrusions are more commonly considered suitable for percutaneous intradiscal procedures. However, extrusion itself may not be a universal contraindication to all needle-based intradiscal interventions, particularly when the fragment is non-sequestered and remains continuous with the parent disc. This narrative review evaluates the evidence, safety considerations, and clinical positioning of intradiscal procedures in extruded, non-sequestered lumbar disc herniations.
Evidence Acquisition:
A structured narrative review was conducted using PubMed/MEDLINE, Embase, Scopus, the Cochrane Library, Google Scholar, reference-list screening, and selected technical or manufacturer documents. The review focused on intradiscal interventions used or debated for lumbar disc herniation with radicular symptoms, including percutaneous laser disc decompression and targeted PLDD (T-PLDD), radiofrequency nucleoplasty, oxygen-ozone (O2-O3) discolysis, gelified ethanol, and mechanical decompression devices. Epidural injections, endoscopic or open discectomy, and procedures primarily investigated for discogenic axial low back pain or the regenerative treatment of degenerative disc disease were excluded from the main synthesis. Evidence was interpreted according to study design, disc morphology, direct applicability to extruded non-sequestered herniation, clinical outcomes, and safety reporting.
Results:
The evidence base is limited and heterogeneous. T-PLDD and radiofrequency nucleoplasty provide the most direct, although still low-certainty, clinical evidence for extruded or uncontained herniations. Oxygen-ozone discolysis has biological plausibility, particularly through modulation of inflammation and potential facilitation of fragment resorption; however, most clinical data are derived from mixed-morphology cohorts. Gelified ethanol has encouraging observational data, including studies that permitted non-contained lesions, but extrusion-specific outcomes remain insufficient. Mechanical decompression devices differ from the other modalities because the reviewed evidence and device technical guidance primarily relate to contained herniations, free fragments are excluded in the manufacturer's technical guide, and extrapolation to extruded or sequestered lesions is not supported.
Conclusions:
Extrusion alone should not be considered a universal contraindication to all intradiscal interventions. Nevertheless, current evidence remains insufficient to support these procedures as alternatives to guideline-supported conservative care or surgical discectomy. Intradiscal interventions may be considered only as selective, non-first-line, intermediate options in carefully selected patients with extruded but non-sequestered lumbar disc herniations, preserved continuity with the parent disc, no progressive neurological deficit, and appropriate counseling regarding uncertain benefit and the possibility of surgical crossover. High-quality, extrusion-specific studies using standardized morphology definitions and rigorous safety reporting are needed.
Related Concept Videos
 01:23
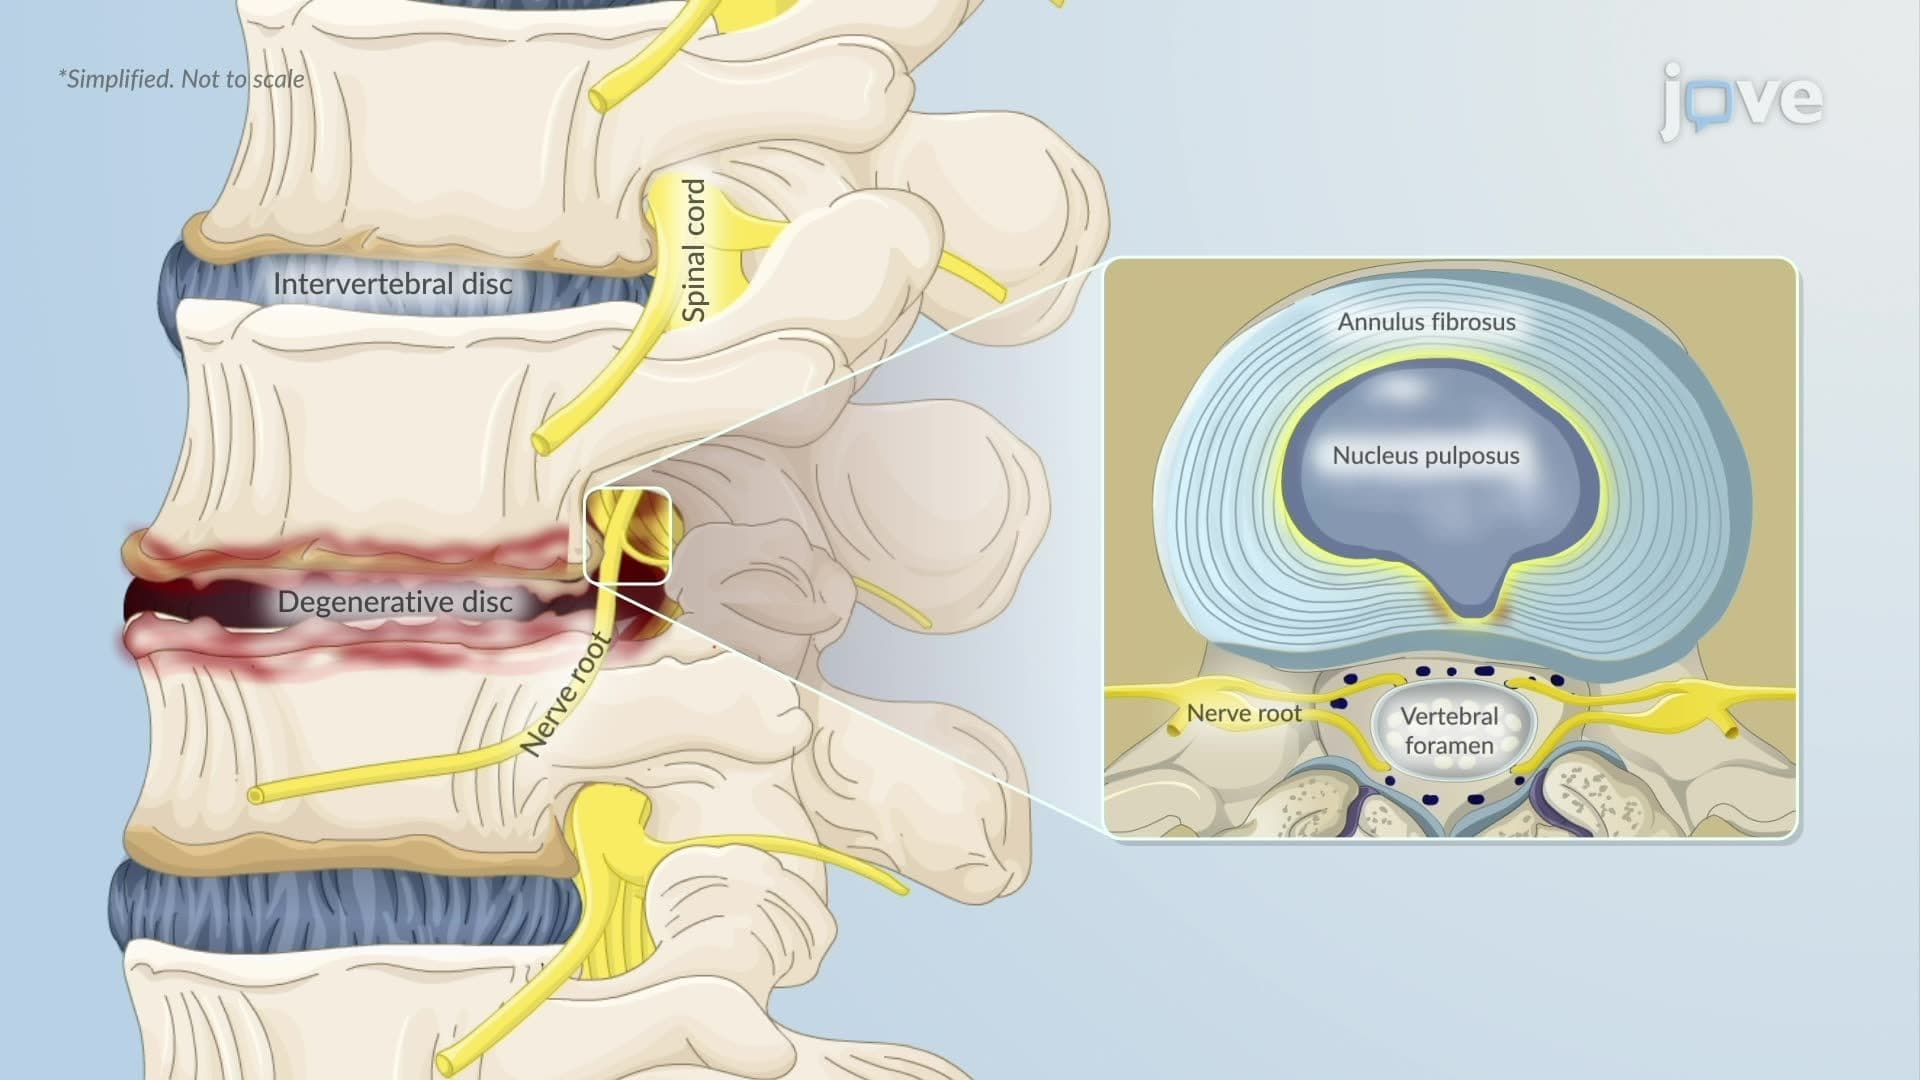
Degenerative Disc Disease ll: Pathophysiology
 01:27
Degenerative Disc Disease I: Introduction
 01:29
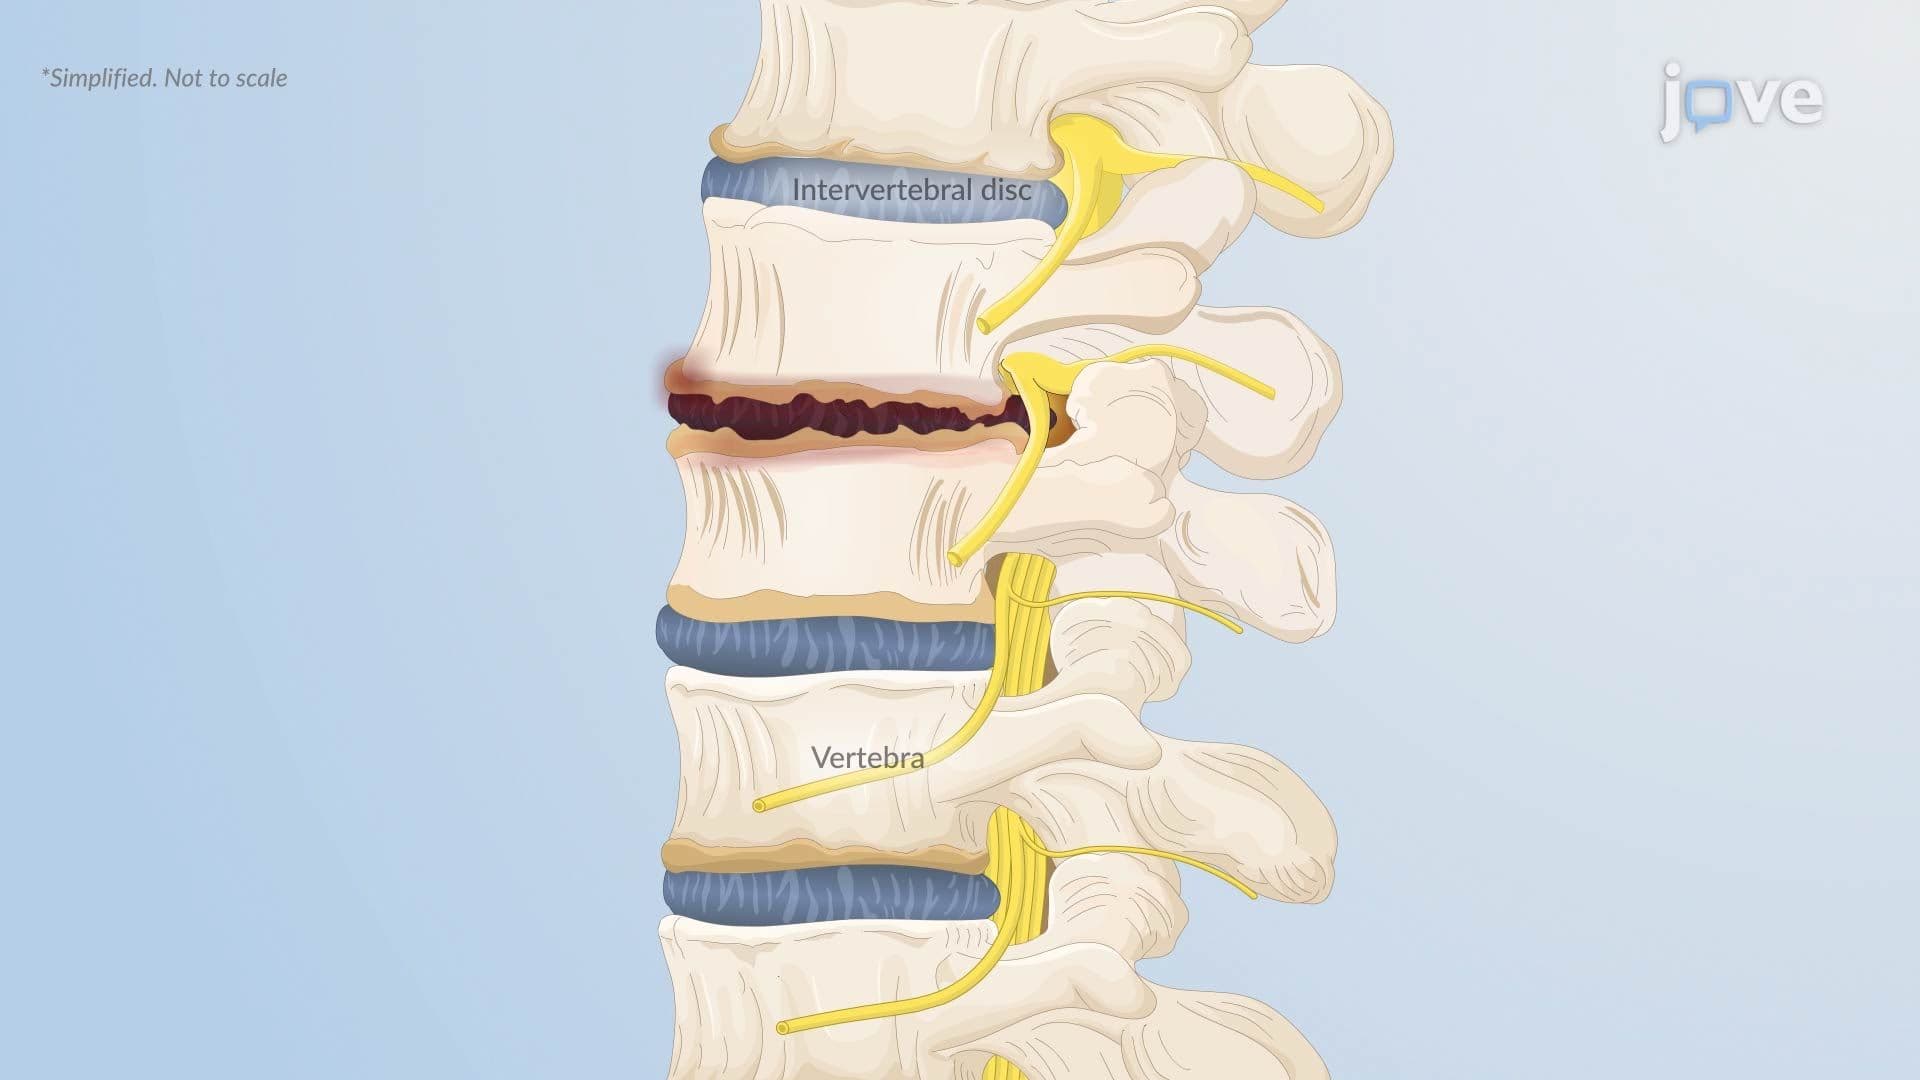
Herniated Intervertebral Disc l: Introduction