Quantitative CT lead localization reveals proximal left bundle targeting facilitates superior physiologic pacing
Related Experiment Video
Updated: Sep 22, 2026
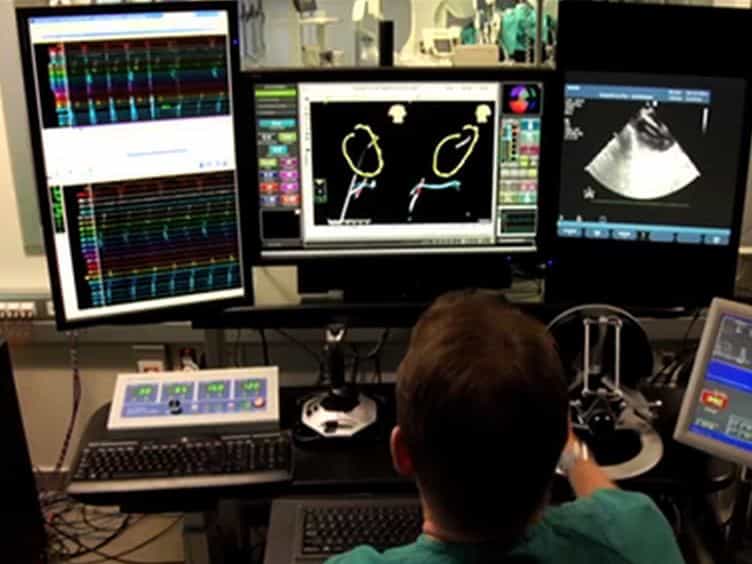
Remote Magnetic Navigation for Accurate, Real-time Catheter Positioning and Ablation in Cardiac Electrophysiology Procedures
Published on: April 21, 2013
Shunmuga Sundaram Ponnusamy1, Stefano Spaziani2, Habibulla Moghal1
1Department of Cardiology, Velammal Medical College Hospital and Research Institute, Madurai, Tamil Nadu, India.

Background:
Implantation electrical criteria for left bundle branch capture in conduction system pacing (CSP) cannot localize the lead along the conduction axis.
Objectives:
The goals of this study were to classify CSP lead position with an observer-independent computed tomography workflow using 2 anatomic measurements-lead-to-His distance (LH) and lead-to-endocardium offset (LE)-and to test whether a proximal position yields near-native paced activation.
Methods:
Of 186 consecutive patients undergoing CSP, 145 had interpretable computed tomography anatomy. Leads were classified by a prespecified rule: left ventricular septal pacing if LE ≤ -2.5 mm; otherwise, proximal (LH ≤ 25 mm) or distal (LH > 25 mm), with 25 mm referenced to left bundle histology. The primary analysis set included patients in sinus rhythm, native QRS duration < 115 ms, complete paired electrocardiograms (ECGs), and LE > -2.5 mm (n = 46). The primary end point was |Δ frontal axis| ≤ 15° and |Δ QRS duration| ≤ 15 ms.
Results:
Classification yielded 68 proximal, 70 distal, and 7 left ventricular septal pacing leads. The procedural label carried no positional information (48% of physician-labeled left bundle branch pacing leads were proximal vs 49% overall). The composite end point occurred in 15 of 24 proximal leads (62%) vs 6 of 22 distal leads (27%) (odds ratio 4.14; 95% confidence interval 1.23-13.96; P = .021; adjusted odds ratio 5.35; P = .013), a finding consistent across sensitivity analyses. The receiver operating characteristic-optimal LH cut point (24.9 mm) independently reproduced the prespecified 25-mm threshold. Position was not recoverable from the surface ECG (classification area under the curve 0.48).
Conclusion:
In this proof-of-concept anatomic study, a 2-measurement rule classified CSP lead position objectively. Near-native paced activation requires proximal targeting (LH ≤ 25 mm), which neither the procedural label nor the ECG can identify; quantitative imaging is required.