Treatment-resistant hypertension in the primary care setting
Related Experiment Video
Updated: Sep 23, 2026
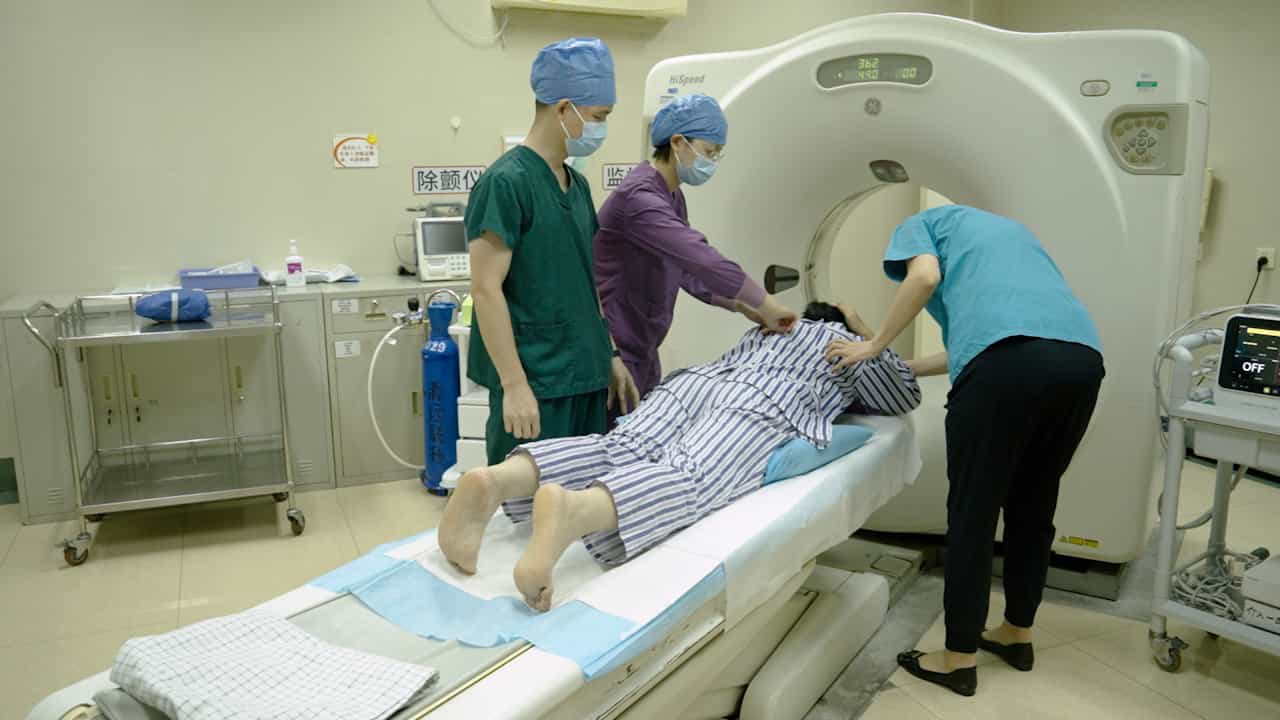
Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Vijay Joshi1, Shreepriya Mangalgi2, Kunal Chaudhary2,3
1The Karl D. Nolph Division of Nephrology and Hypertension, University of Missouri School of Medicine, CE 414, 1 Hospital Drive, Columbia, MO, USA.

Context:
Rates of treatment-resistant hypertension in the United States are increasing despite our better understanding of underlying mechanisms, lifestyle and pharmacologic approaches, and with refinement of treatment goals. Distinguishing treatment resistance from pseudo-resistance or even refractory hypertension is increasingly clinically difficult, and understanding the influences that dictate resistance in the primary care setting is needed to improve patient outcomes.
Objectives:
Herein, we will review current definitions of treatment resistance, pseudo-resistance, and refractory hypertension, and we will discuss patient- and provider-related factors that influence resistance, facilitating a more holistic approach to care.
Methods:
We conducted a comprehensive narrative review utilizing PubMed as the basis for our medical literature search. We employed a combination of Medical Subject Headings (MeSH) terms and free-text keywords, including "treatment resistant hypertension," "resistant hypertension," "refractory hypertension," and "pseudo-resistance." No language or date restrictions were applied for the initial search to help with wide capture of available literature that included a broad range of study designs, clinical guidelines, and consensus statements.
Results:
Resistance is classically defined as blood pressure (BP) >130/80 mm Hg despite the use of three or more antihypertensives including a diuretic at optimized doses and with appropriate combination of drugs having complementary mechanisms of action, or with controlled BP requiring four or more anti-hypertensive drugs. Improper BP measurement techniques, underdosing antihypertensives, therapeutic inertia, nonadherence, and even a white coat effect contribute to pseudo-resistance.
Conclusions:
Addressing factors that contribute to pseudo-resistance is of utmost significance in managing a patient with apparent treatment resistance or even refractory hypertension in the primary care setting. Recent strategies for managing true resistance include ambulatory BP monitoring or out-of-office home BP measurement, assessing underlying secondary causes, rational drug design to optimize the drug regimen, and a collaborative multidisciplinary approach with guidance from hypertension specialists. Addressing the factors that underlie pseudo-resistance and treatment resistance is consequential to improve not only major cardiovascular morbidity and mortality but also quality of life and tolerability of complex treatment regimens. Herein, we aim to address factors to improve care for hypertension in the primary care setting.
Related Concept Videos
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:23
Hypertension V: Nursing Management
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Hypertension I: Introduction
 01:18
Hypertension and Regulation of Blood Pressure
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...