Related Experiment Video
Updated: Sep 23, 2026
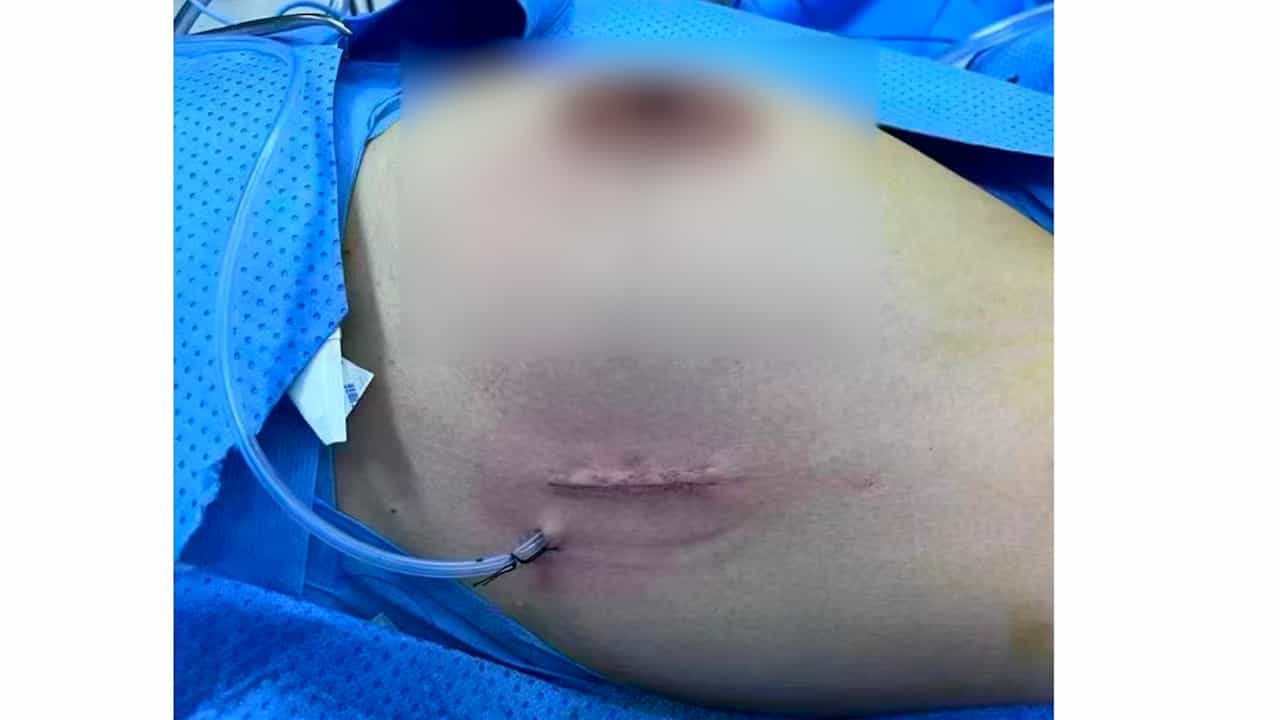

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Neoadjuvant Dual-Targeted HER2 Therapy and Neoadjuvant Chemo-Immunotherapy is Associated with Improved Nodal pCR and
Saranya Prathibha1, Tanya L Hoskin2, Matthew P Goetz3
1Division of Breast and Melanoma Surgical Oncology, Department of Surgery, Mayo Clinic, Rochester, MN, USA.

Background:
Systemic therapy advances such as dual-agent human epidermal growth factor receptor 2 (HER2)-targeted therapy (addition of pertuzumab in 2013) and immunotherapy (IO) for triple-negative breast cancer (TNBC) (introduction of pembrolizumab in 2021) improved pathologic complete response (pCR) and overall survival (OS). This study assessed impact on nodal pCR (npCR) rate and its association with axillary lymph node dissection (ALND) trends and OS.
Methods:
Using the National Cancer Database, this study identified patients from 2010 to 2023 who had cN+ stage II or III HER2+ or TNBC treated with neoadjuvant chemotherapy. The study evaluated patients who had TNBC treated without IO (2010-2020) and with IO (2021-2023) and patients who had HER2+ disease treated in 2010-2013 (single-agent HER2-targeting era) and 2014-2023 (dual-agent era), respectively. Chi-square tests and multivariable Cox proportional hazards regression compared percentages and analyzed OS.
Results:
The study identified 49,186 HER2+ and 36,612 TNBC patients. Rates of npCR improved in all subtypes. The npCR rates were higher among patients who had TNBC treated with IO (69%) than among those who had who had TNBC treated without IO (52%; p < 0.001). In HER2+ disease, npCR was higher in the dual-agent era than in the single-agent era (57% vs 48% for estrogen receptor-positive [ER+]/HER2+ and 77% vs 61% for estrogen receptor-negative [ER-]/HER2+ [each p < 0.001]). In TNBC with IO, ALND decreased from 67 to 50% overall, from 50 to 38% in ypN0, and from 83 to 77% in ypN+. In HER2+ disease, the ALND rate similarly decreased in the dual-agent era overall, in ypN0, and in ypN+. With respect to OS, TNBC with nodal pCR alone had better OS than with breast pCR alone (hazard ratio [HR], 0.77; p < 0.001).
Conclusions:
The dual-targeting era for HER2 disease and the use of IO for TNBC are associated with increased nodal pCR. Nodal pCR is associated with decreased ALND.
