Related Experiment Video
Updated: Sep 23, 2026
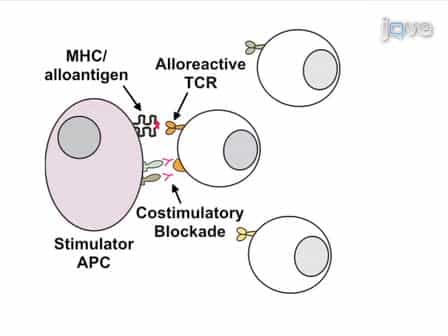

Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Early Broad-Spectrum Antibiotic Exposure Is Associated with Increased Relapse after Myeloablative TBI-Based
Isabella Gruber1, Matthias Edinger2, Hendrik Poeck3
1Department of Radiation Oncology, University Hospital Regensburg, Franz-Josef-Strauss Alle 11, Regensburg, Germany.

Background:
Broad-spectrum antibiotics are frequently administered during the peri-transplant period in patients undergoing allogeneic hematopoietic cell transplantation (allo-HCT). Antibiotic exposure can disrupt the intestinal microbiota and may influence immune recovery and post-transplant outcomes. However, the impact of antibiotic timing on relapse risk after myeloablative total body irradiation (TBI)-based conditioning remains poorly defined.
Objective:
To investigate whether the timing of therapeutic antibiotic exposure is associated with relapse and other transplantation outcomes in adults undergoing myeloablative TBI-based allo-HCT.
Study Design:
We retrospectively analyzed 160 adults with acute myeloid leukemia (n = 59) or acute lymphoblastic leukemia (n = 101) undergoing first allo-HCT following myeloablative TBI (8 or 12 Gy). Therapeutic antibiotic exposure was classified as early (initiation before stem cell infusion on Day 0; observed range, Day -20 to -1) or non-early (initiation on Day 0 or thereafter during the initial hospitalization for allo-HCT, or no systemic therapeutic antibiotic exposure during this hospitalization). Endpoints were cumulative incidence of relapse (CIR) and non-relapse mortality (NRM). Associations were evaluated using multivariable models adjusted for disease status, age, diagnosis, and TBI dose. Fine-Gray regression was used for relapse and NRM and Cox regression for OS and PFS. Sensitivity analyses included adjustment for calendar year, ATG use, gut decontamination strategy, and institutional antibiotic protocol era, landmark analyses at Days +30 and +60, and assessment of interactions between early antibiotic exposure and clinically relevant factors.
Results:
Median follow-up was 9.8 years. Forty-five patients (28.1%) received early and 115 (71.9%) non-early therapeutic antibiotics. Baseline characteristics were broadly comparable between groups. Early antibiotic exposure was associated with a higher unadjusted CIR than non-early exposure (1-year: 40% vs. 17%; 2-year: 45% vs. 23%; Gray's test P = .006), whereas unadjusted NRM was similar (2-year: 16% vs. 15%; Gray's test P = .690). In multivariable Fine-Gray analyses, early antibiotic exposure was associated with a higher subdistribution hazard of relapse (SDHR 2.00, 95% CI, 1.16-3.43; P = .013), but not with NRM or GVHD. No statistically significant interactions between early antibiotic exposure and disease status, diagnosis, age, or TBI dose were observed. Cause-specific Cox regression confirmed the association between early antibiotic exposure and relapse (CSHR 2.06, 95% CI, 1.20-3.56; P = .009). The association remained consistent after adjustment for calendar year, gut decontamination strategy, ATG use, and the institutional antibiotic protocol era and in landmark analyses at Days +30 and +60. Early antibiotic exposure was associated with inferior OS (HR 1.66, 95% CI, 1.05-2.62; P = .030) and PFS (HR 1.75, 95% CI, 1.12-2.75; P = .014).
Conclusion:
In adults with acute leukemia undergoing myeloablative TBI-based allo-HCT, early therapeutic antibiotic exposure was associated with increased relapse incidence and inferior survival, without detectable associations with GVHD or NRM. These observational findings support an association between antibiotic timing and leukemia control but do not establish causality or justify withholding clinically indicated antibiotic therapy. Prospective studies integrating detailed antibiotic exposure data, immune reconstitution analyses, and microbiome profiling are needed to determine whether antibiotic timing contributes to post-transplant relapse risk.

Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...
 01:40
Cell-mediated Immune Responses
 01:27
Cryptococcal Meningitis