A computational framework for quantifying hemodynamic burden in pediatric pulmonary vein stenosis
Related Experiment Video
Updated: Sep 23, 2026
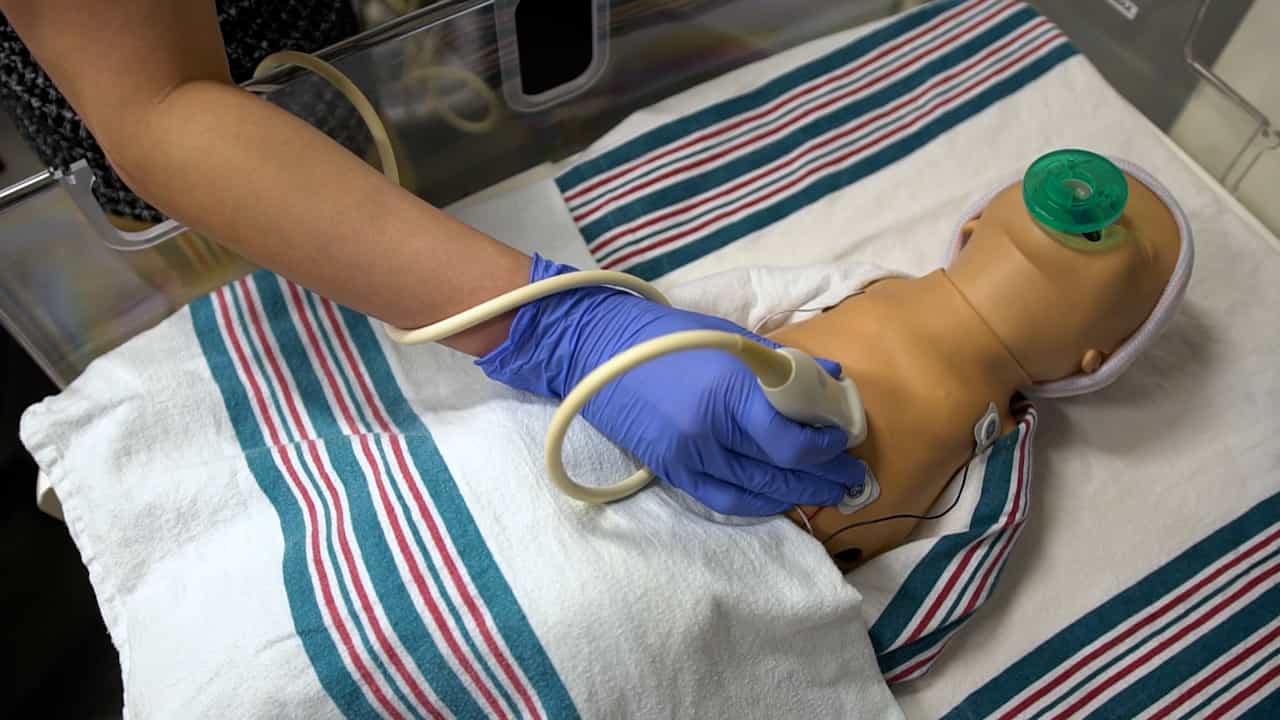
Hemodynamic Precision in the Neonatal Intensive Care Unit using Targeted Neonatal Echocardiography
Published on: January 27, 2023
Manish Bansal1, Dan Lior1, Avishek Mukherjee2
1Division of Pediatric Cardiology, Department of Pediatrics, Texas Children's Hospital Heart Center and Baylor College of Medicine, Houston, Tex.

Background:
Pulmonary vein stenosis (PVS) is a rare but devastating pediatric disorder characterized by progressive obstruction, pulmonary hypertension, and high rates of restenosis despite catheter-based and surgical interventions. Current clinical assessment relies largely on anatomical imaging and catheter-derived pressure gradients, which provide limited insight into the interplay between geometry and complex hemodynamic forces contributing to disease progression. In this study, we developed a patient-specific computational framework to quantify pulmonary venous hemodynamics and characterize hemodynamic burden at varying severities of PVS.
Methods:
Cardiac computed tomography angiograms from patients with mild, moderate, and severe PVS were used to reconstruct patient-specific pulmonary vein geometries. Classification of PVS severity was based on the degree of stenosis and the trans-stenotic pressure gradient, with mild, moderate, and severe cases corresponding to gradients of 5, 9, and 14 mm Hg, respectively. An unaffected pulmonary vein with a pressure gradient of 3 mm Hg was used as the control. We solved the incompressible Navier-Stokes equations with constant pressure boundary conditions applied to surfaces proximal and distal to the stenosis. Key hemodynamic metrics, including wall shear stress (WSS) and power loss, were quantified and a sensitivity analysis was conducted by varying the pressure gradient while keeping the anatomy of the pulmonary vein fixed, in the control and moderate cases. These parameters were integrated into a composite hemodynamic risk score (HRS) using an equal-weighted approach to provide a quantitative measure of hemodynamic burden.
Results:
Increasing PVS severity was associated with progressive elevations in WSS and power loss, reflecting increasing hemodynamic burden within stenotic pulmonary veins. The mean WSS was 16, 42, 45, and 73 dyne/cm2, and mean power loss was 0.012, 0.075, 0.21, and 0.47 dyne cm/s for control, mild, moderate, and severe cases, respectively. The HRS values were 9.63, 20.72, 27.98, and 44.44 for control, mild, moderate, and severe PVS, respectively.
Conclusions:
Our computational model enabled quantification of pulmonary venous hemodynamics and provided a framework for integrating multiple metrics into the HRS, which represents disease burden.