Related Experiment Video
Updated: Sep 23, 2026


Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
Precision Surgery for Colorectal Deep Endometriosis: Strategies for Complete Excision Without Segmental Resection
Sonia Eskandarion1, Jasmine Eliwa1, Diana Encalada Soto1
1Division of Gynecological Subspecialties, Department of Obstetrics and Gynecology, University of South Florida Morsani College of Medicine, Tampa, Florida, USA.

Objective:
To study the role of robotic surgery integrated with intraoperative ultrasound in achieving complete excision of colorectal deep endometriosis while avoiding segmental bowel resection.
Design:
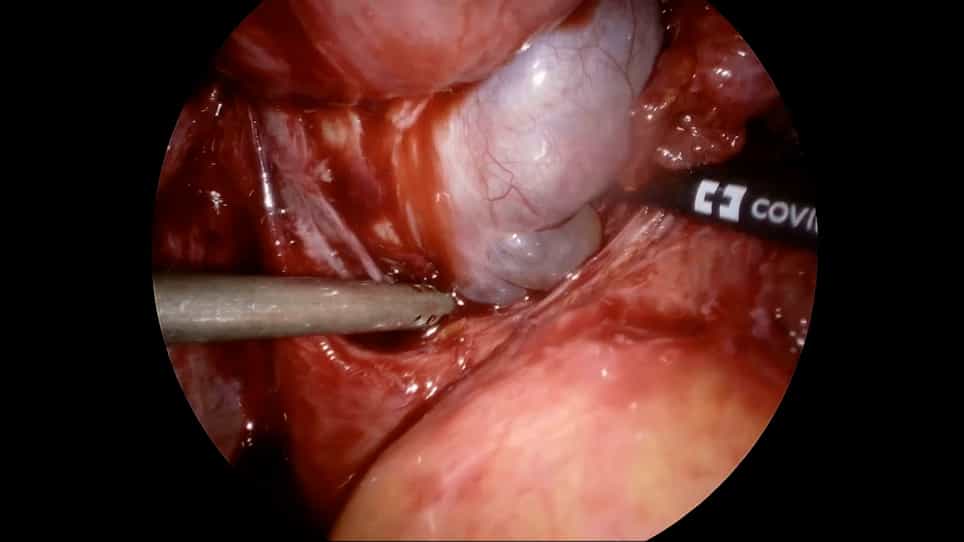
Educational surgical video demonstrating a stepwise robotic approach with integrated intraoperative ultrasound for lesion localization, excision, and real-time intraoperative decision-making.
Subject:
A 38-year-old G0 patient with recurrent colorectal deep endometriosis presented with chronic pelvic pain, dysmenorrhea, dyschezia, and infertility after a previous rectal shaving procedure. Preoperative transvaginal ultrasound demonstrated a hypoechoic posterior cul-de-sac nodule, and magnetic resonance imaging revealed rectosigmoid deep endometriosis with submucosal invasion (mushroom-cap sign).
Exposure:
Robotic excision of colorectal endometriosis guided by intraoperative ultrasound. Two bowel lesions were identified: a proximal sigmoid lesion (15 × 5 mm) and a distal rectal lesion (24 × 9 mm). The sigmoid lesion was excised using a linear stapler, whereas the rectal lesion underwent discoid excision with a circular stapler. Intraoperative ultrasound was used before and after excision to assess lesion extent and confirm completeness of resection.
Main Outcome Measures:
Complete excision of colorectal endometriosis confirmed by intraoperative ultrasound and histopathology, successful preservation of bowel continuity without segmental resection, and optimization of intraoperative surgical decision-making.
Results:
Post-excision ultrasound confirmed complete removal of the sigmoid lesion. Residual disease was identified at the rectal excision margin, prompting a second discoid excision. Repeat intraoperative ultrasound demonstrated complete removal of the residual lesion. Histopathologic examination confirmed endometriosis in both specimens. Complete excision was achieved without the need for segmental bowel resection.
Conclusion:
Robotic surgery combined with intraoperative ultrasound enables precise localization, tailored stapler selection, and real-time assessment of colorectal deep endometriosis, facilitating complete excision while preserving bowel integrity. Intraoperative ultrasound verification can detect residual disease requiring immediate re-excision, potentially reducing recurrence and avoiding unnecessary segmental bowel resection. Careful preoperative planning, meticulous robotic dissection, and integration of intraoperative ultrasound optimize surgical outcomes in selected patients with colorectal deep endometriosis.